Related Experiment Video
Updated: Jul 12, 2026


Intra-cardiac Side-Firing Light Catheter for Monitoring Cellular Metabolism using Transmural Absorbance Spectroscopy of Perfused Mammalian Hearts
Published on: May 12, 2019
Cyanide poisoning: pathophysiology and treatment recommendations
1University of Otago School of Medicine, Dunedin, New Zealand.

Abstract:
This paper aims to assess and compare currently available antidotes for cyanide poisoning. Such evaluation, however, is difficult. Thus, extrapolation from the results of animal studies has potential pitfalls, as significant inter-species differences in response may exist, and these experiments often involve administration of toxin and antidote almost simultaneously, rather than incorporating a more realistic time delay before initiation of treatment. Direct inference from human case reports is also problematic; either because of uncertainties over the exposure levels involved (and hence the likely outcome without treatment), or because of difficulties in identifying the specific contribution of a particular antidote within the overall treatment regimen. Certainly an effort to compare the relative efficacy of cyanide antidotes produces equivocal findings, with no single regimen clearly standing out. Indeed, factors such as the risks of antidote toxicity to various individuals and other practical issues, may be more important considerations. There is therefore no single treatment regimen which is best for all situations. Besides individual risk factors for antidote toxicity, the nature of the exposure and hence its likely severity, the evolving clinical features and the number of persons involved and their proximity to hospital facilities, all need to be considered. Clinically mild poisoning may be treated by rest, oxygen and amyl nitrite. Intravenous antidotes are indicated for moderate poisoning. Where the diagnosis is uncertain, sodium thiosulphate may be the first choice. With severe poisoning, an additional agent is required. Given the various risks with methaemoglobin formers or with unselective use of kelocyanor, hydroxocobalamin may be preferred from a purely risk-benefit perspective. However the former alternatives will likely remain important.
More Related Videos


Related Concept Videos
 01:17
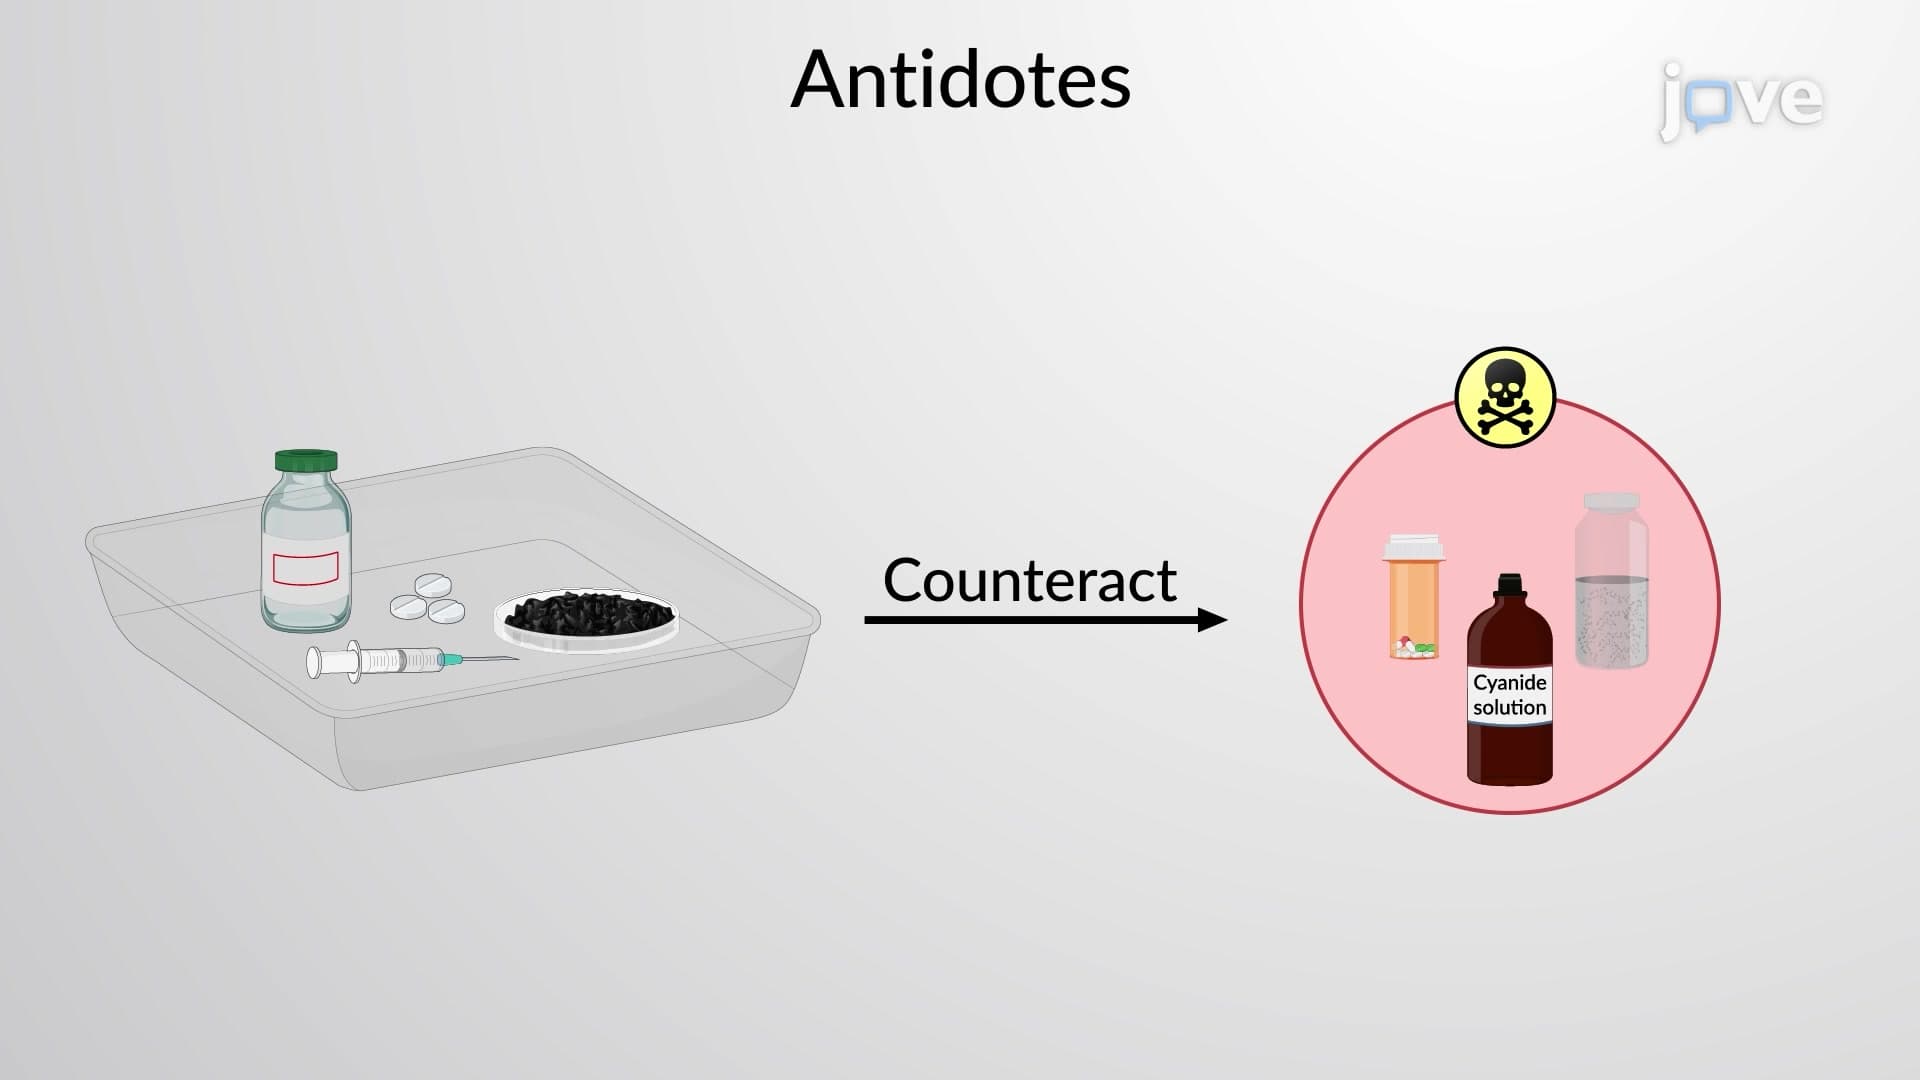
Antidotes
Specific antidotes operate by inhibiting the enzymes that control biochemical pathways, reducing the production of harmful metabolites.
An example of an antidote is atropine, which counteracts the detrimental effects of cholinesterase inhibitors. It achieves this by deactivating muscarinic receptors,...
 01:14
Prevention of Further Absorption of Poison
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...
 01:19
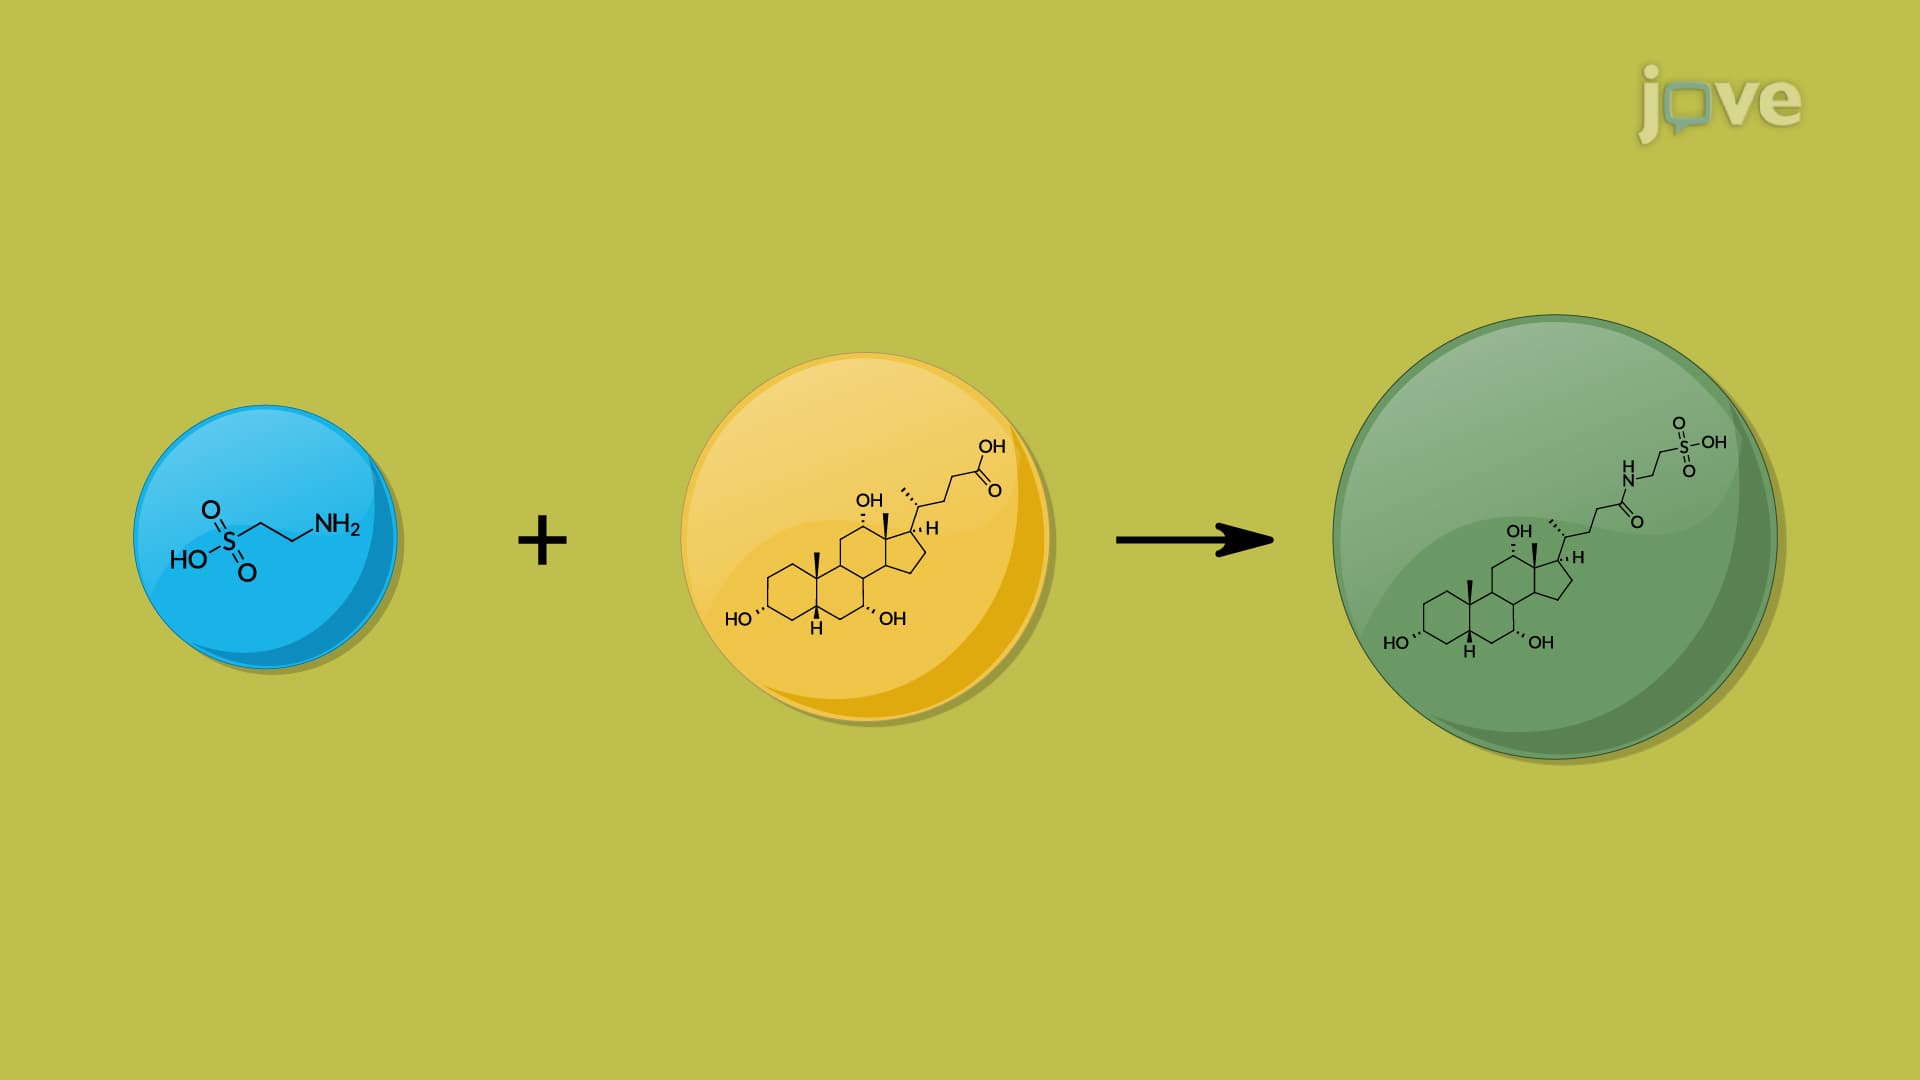
Phase II Reactions: Miscellaneous Conjugation Reactions
A key example involves the conjugation of cyanide ions, which impair cellular respiration and alter hemoglobin into non-oxygen-carrying cyanmethemoglobin. To neutralize this threat, a sulfur atom from thiosulphate is transferred to the cyanide ion, catalyzed by the enzyme rhodanese, resulting in an inactive compound called thiocyanate. The production of...
 01:26
Pharmaceutical Poisoning: Treatment Strategies