Related Experiment Video
Updated: Aug 19, 2026
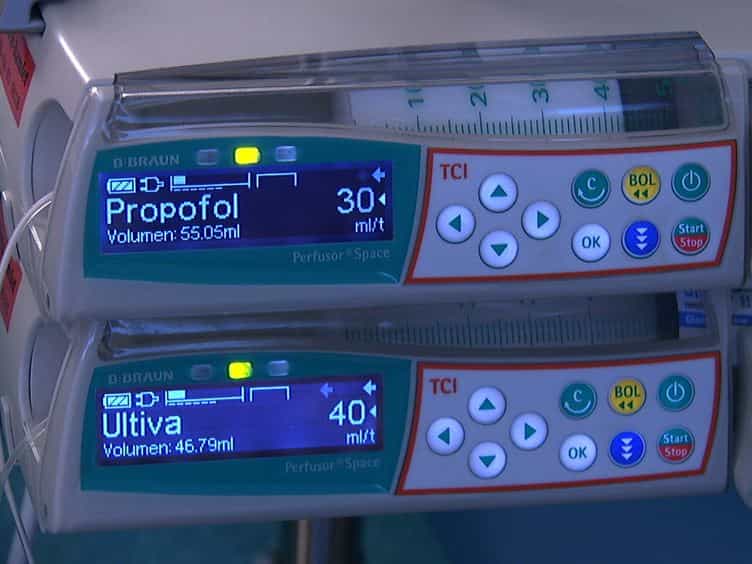

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
The nature of spontaneous recovery from mivacurium-induced neuromuscular block
C A Lien1, M R Belmont, A Abalos
1Department of Anesthesiology, The New York Hospital-Cornell Medical Center, New York 10021, USA.

Unlabelled:
The hypothesis of this study was that, in a given patient, recovery from a tracheal intubating dose of mivacurium would indicate the time course of spontaneous recovery after discontinuation of an infusion of mivacurium. Thirty-eight male patients consented to participate in the study. After induction of anesthesia and endotracheal intubation, the ulnar nerve was stimulated with train-of-four (TOF) stimuli at 12-s intervals. Patients received 0.3 mg/kg mivacurium in two evenly divided doses of 0.15 mg/kg each, separated by 30 s. Complete ablation of TOF responses occurred in most patients. Once the first twitch in the TOF (T ) had recovered to 25% of its baseline height, a mivacurium infusion was begun to maintain 95% suppression of T1. As surgery was nearing completion, the infusion was discontinued, and neuromuscular function was allowed to recover spontaneously. Data were analyzed for recovery intervals after the administration of the initial doses of mivacurium and after discontinuation of the infusion. Analysis of variance was used to determine the strength of correlation between the time from administration of the initial 0.3 mg/kg dose to 5% recovery of T1 and the times to recovery of TOF ratios of 70% and 90%. The 25%-75% recovery interval after discontinuation of the infusion ranged from 2.8 to 11.3 min. The time interval after administration of mivacurium 0.3 mg/kg to 5% recovery of T1 correlated with both the time to recovery of a TOF ratio of 70% and 90%. Recovery to a TOF of 90% after discontinuation of the infusion required approximately the same amount of time as recovery to 5% T1 after the administration of 0.3 mg/kg mivacurium. Each patient's recovery of neuromuscular function after discontinuation of a mivacurium infusion was related to his recovery after the administration of 0.3 mg/kg mivacurium. Therefore, the need for pharmacologic antagonism of block can be anticipated well before the end of an anesthetic.
Implications:
Mivacurium (0.3 mg/kg) was administered to 38 patients. As they began to recover muscle strength, a mivacurium infusion was begun and later discontinued as surgery was nearing completion. Each patient's early recovery (administration to 5% recovery of T1) after the initial dose of mivacurium correlated well with more complete recovery of muscle strength after discontinuation of an infusion. This relationship enables early prediction of recovery speed after a mivacurium infusion.
Insights
Early recovery from mivacurium (0.3 mg/kg) predicts later recovery speed. This allows anesthesiologists to anticipate neuromuscular function recovery after mivacurium infusions, aiding in the decision for pharmacologic antagonism.
Area of Science:
- Anesthesiology
- Pharmacology
- Neuromuscular Physiology
Background:
- Mivacurium is a neuromuscular blocking agent used during anesthesia.
- Predicting the duration of neuromuscular blockade is crucial for patient safety and timely extubation.
- Spontaneous recovery from neuromuscular blocking agents can vary significantly between patients.
Purpose of the Study:
- To test the hypothesis that early recovery from an initial dose of mivacurium predicts the time course of spontaneous recovery after an infusion.
- To establish a correlation between early neuromuscular recovery and later recovery parameters.
Main Methods:
- Thirty-eight male patients undergoing anesthesia received an initial dose of mivacurium (0.3 mg/kg).
- Neuromuscular function was monitored using train-of-four (TOF) stimulation.
- A mivacurium infusion was initiated upon initial recovery and discontinued as surgery concluded.
- Recovery intervals were analyzed to correlate early recovery (5% T1) with later recovery (TOF ratios).
Main Results:
- The time to 5% recovery of the first twitch (T1) after the initial mivacurium dose correlated with the time to achieve TOF ratios of 70% and 90%.
- Recovery to a TOF of 90% after infusion discontinuation took approximately the same time as recovery to 5% T1 after the initial dose.
- A strong correlation was found between early and late recovery phases for each patient.
Conclusions:
- Early neuromuscular recovery after an initial dose of mivacurium is a reliable predictor of recovery speed following a mivacurium infusion.
- This predictive relationship allows for better anticipation of neuromuscular function recovery and informs decisions regarding pharmacologic antagonism.
- The findings support the ability to predict the need for antagonism well before the end of anesthesia.


Related Concept Videos
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
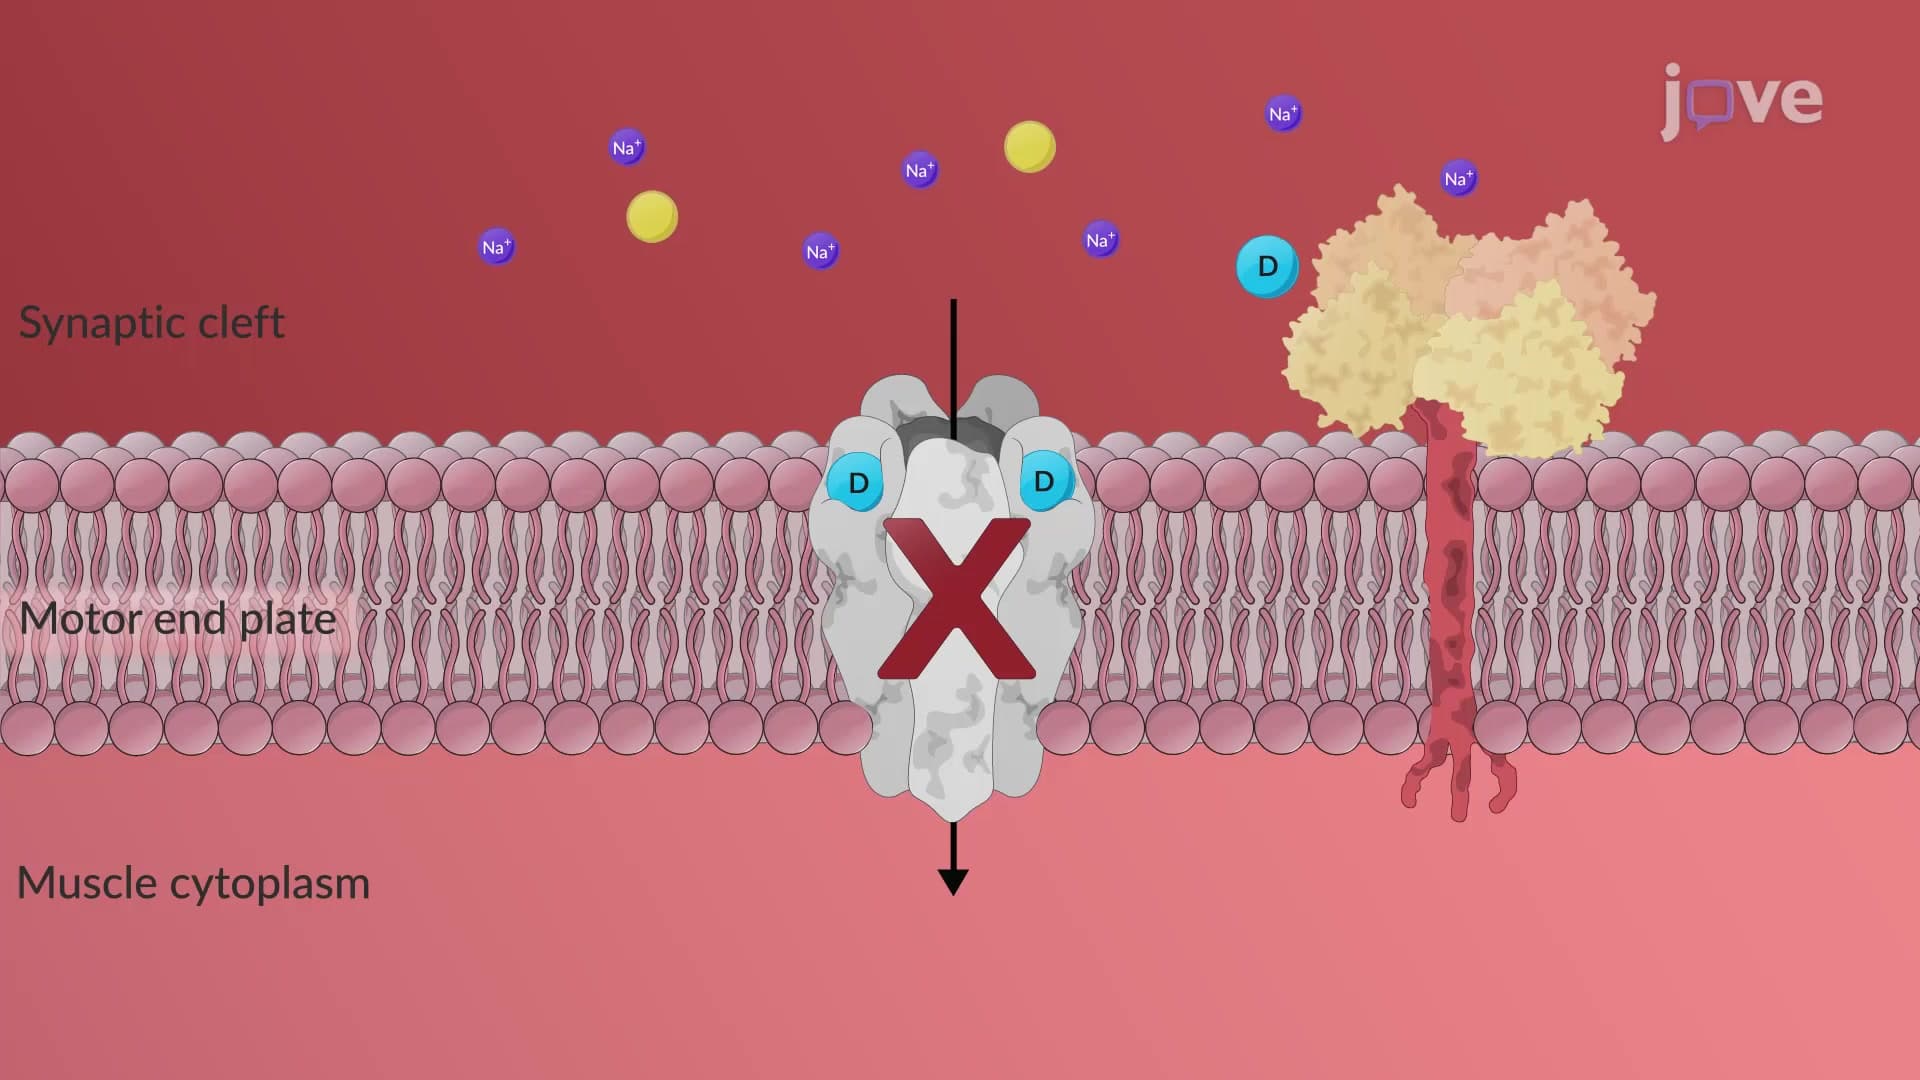 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
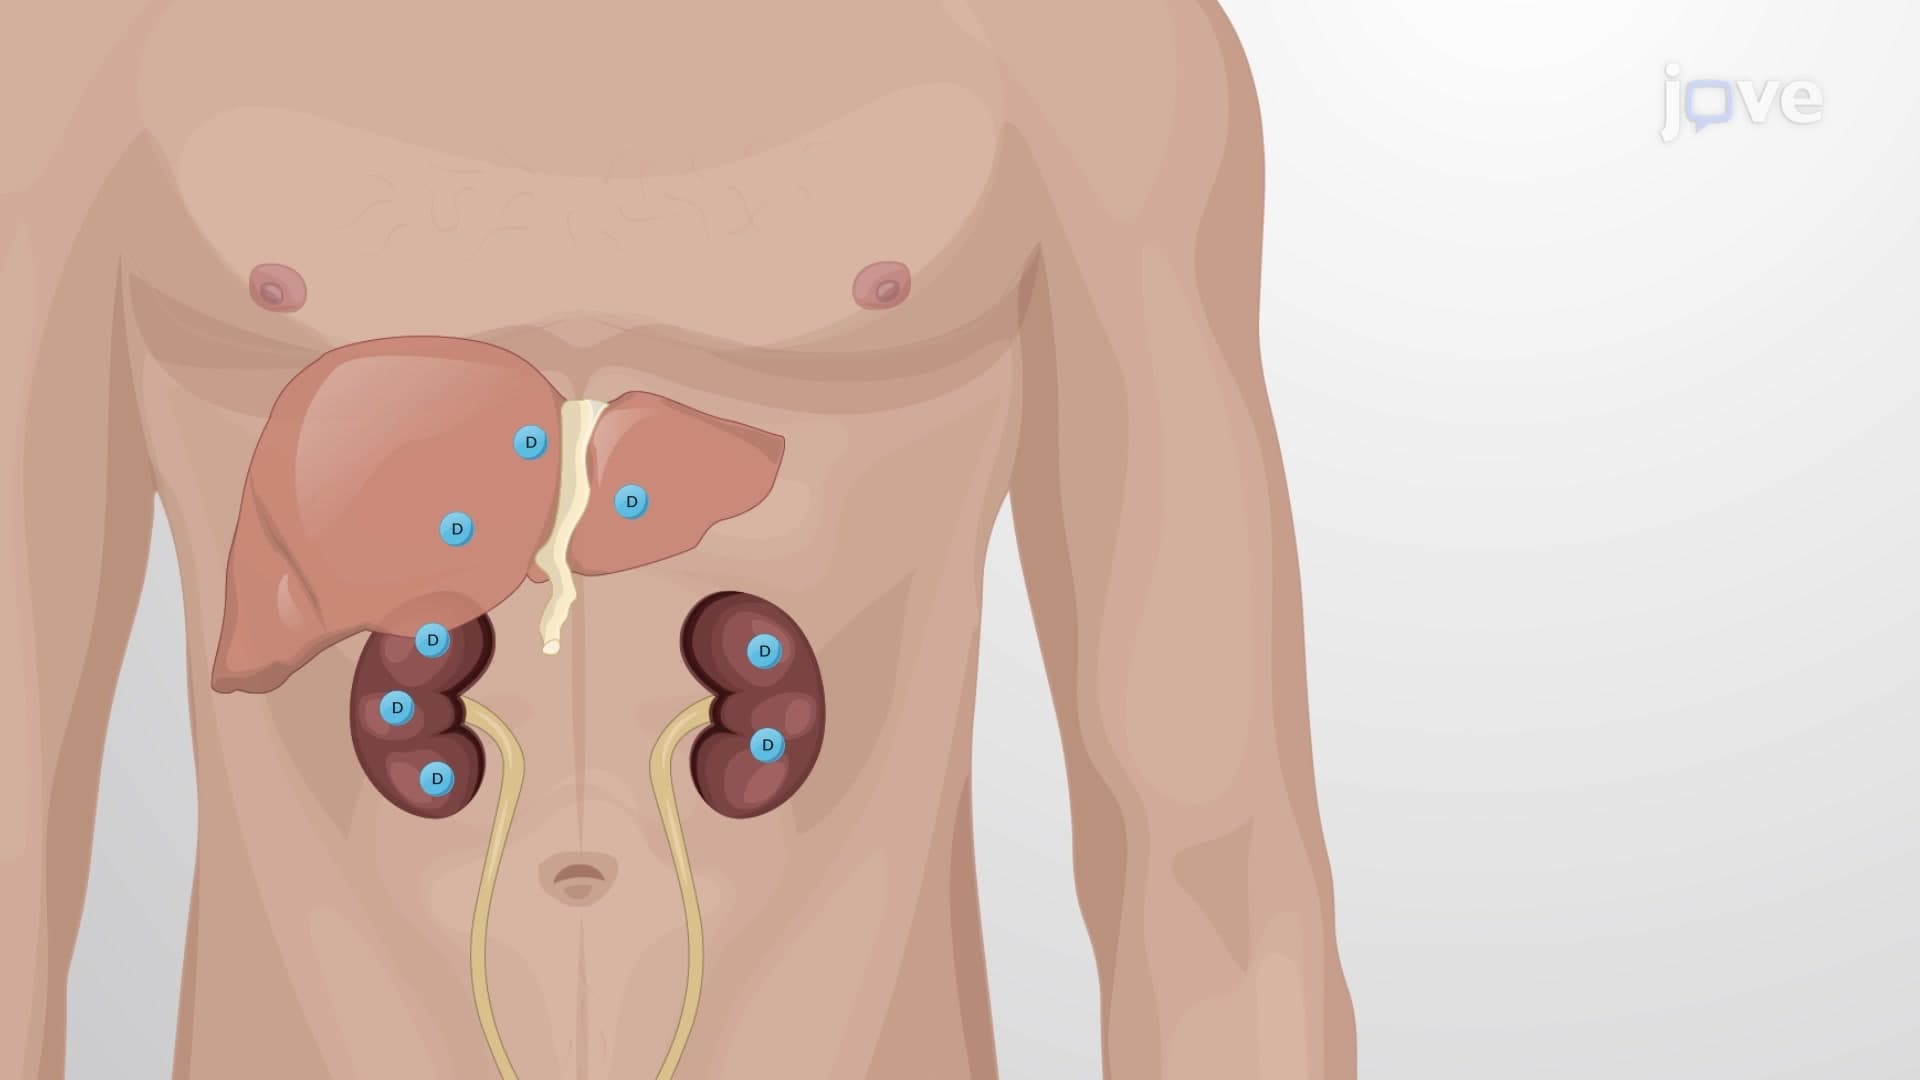 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:28
Depolarizing Blockers: Mechanism of Action
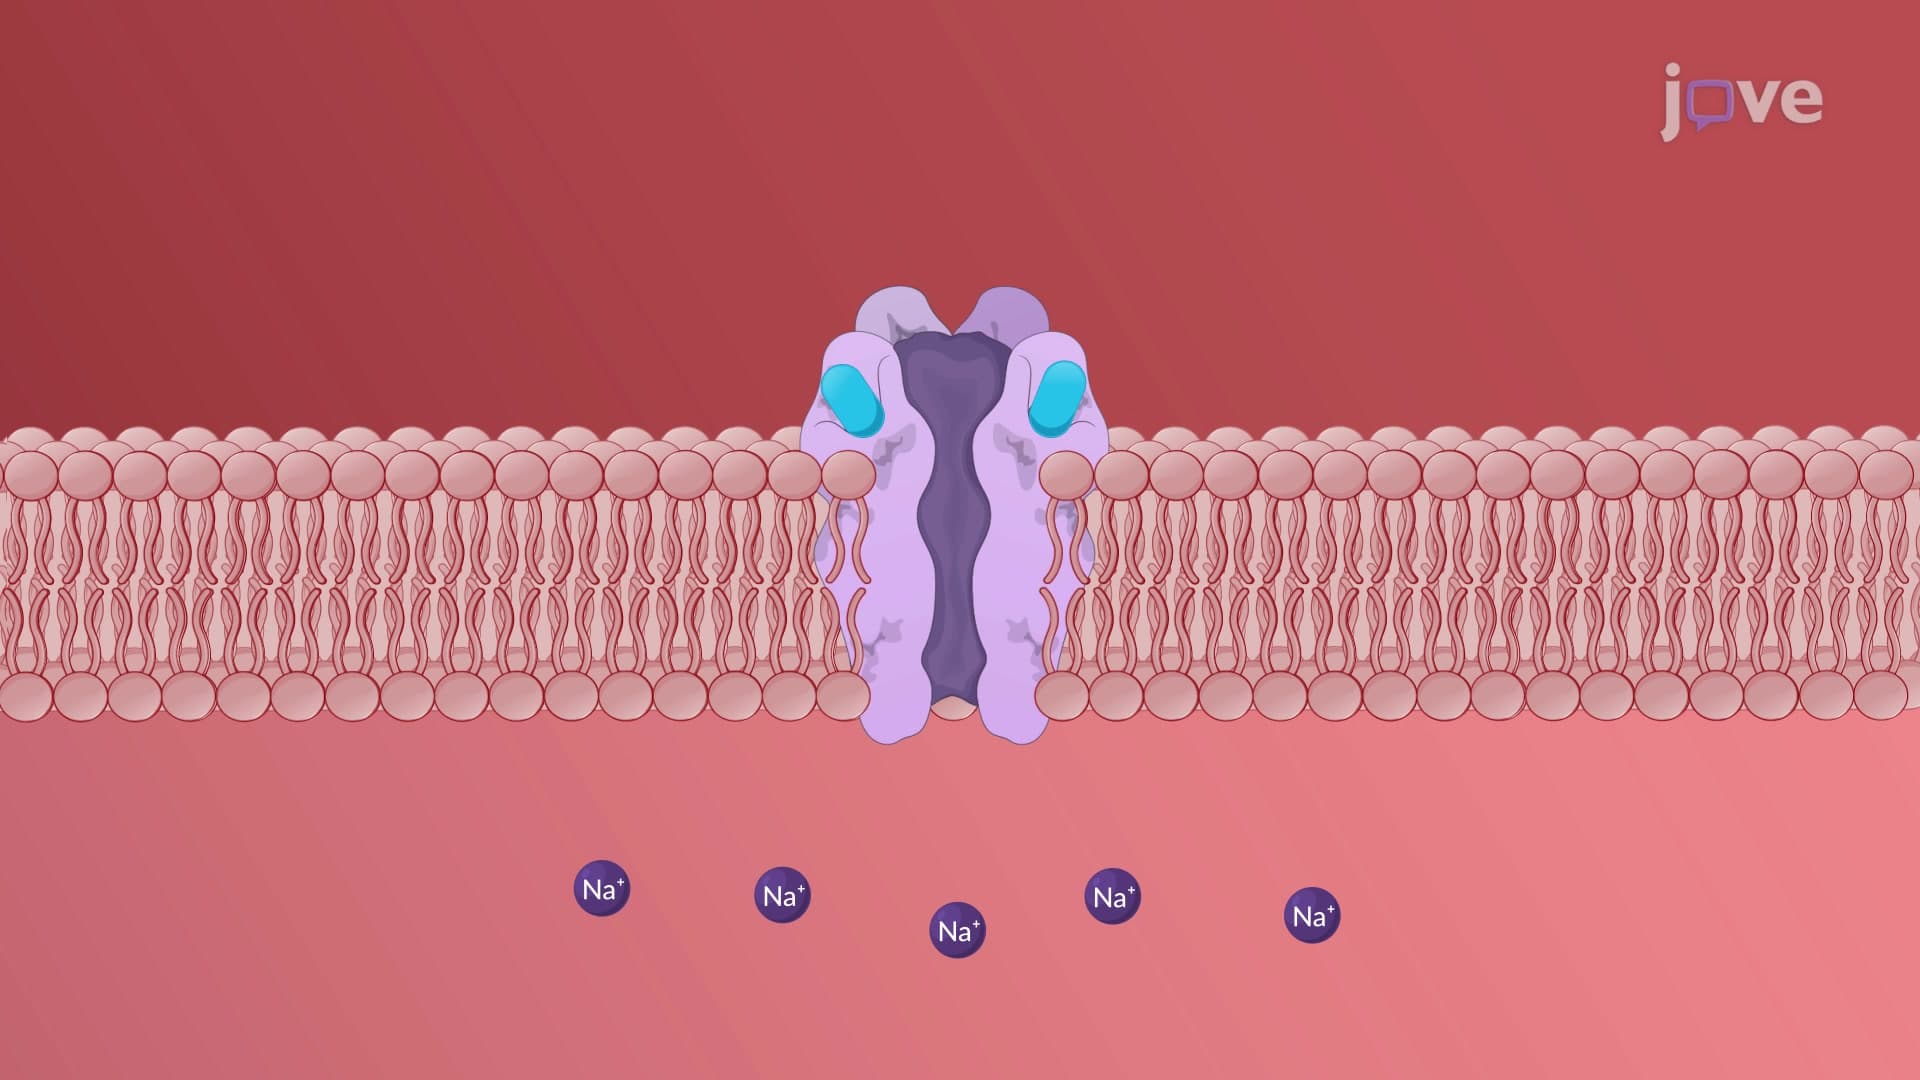
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses