Related Experiment Video
Updated: Sep 28, 2026
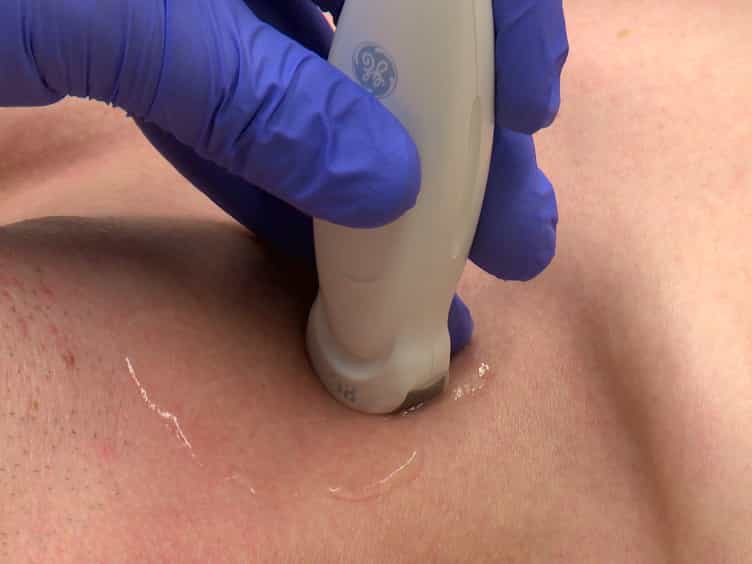

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Improved percutaneous insertion of long-term central venous catheters in children: the 'shrug' manoeuvre
1Department of Paediatric Surgery, Women's and Children's Hospital, Adelaide, South Australia, Australia.

Insights
This study presents a modified percutaneous technique for pediatric central venous access in children over 12 months, offering reduced infection risk and improved outcomes compared to open surgery.
Area of Science:
- Pediatric Surgery
- Vascular Access
- Interventional Radiology
Background:
- Traditional surgical central venous access in children involves open exposure of the internal jugular vein.
- Percutaneous routes offer potential benefits like reduced wound infection, better cosmetic results, and shorter operating times.
Purpose of the Study:
- To describe modifications to a percutaneous approach for central venous access in pediatric patients.
- To facilitate the application of this minimally invasive technique in children over 12 months of age.
Main Methods:
- Insertion of the dilator and peel-away sheath into the subclavian vein under fluoroscopic guidance.
- Utilizing ipsilateral shoulder elevation to aid sheath and catheter passage into the superior vena cava.
Main Results:
- Successful establishment of surgical central venous access using this modified technique in the majority of pediatric patients.
- Application of the technique over a 3-year period at a major children's hospital.
Conclusions:
- The described modifications allow for the safe application of the percutaneous technique in the pediatric age group.
- This approach enhances safety and efficacy for pediatric central venous access.
Background:
Surgical central venous access in children usually requires open exposure of the internal jugular vein or one of its tributaries. The percutaneous route has the potential advantages of a reduced rate of wound infection, superior cosmesis and reduced operating time. We report our modifications to the percutaneous approach that facilitate the application of this technique to children over the age of 12 months.
Methods:
The dilator and peel-away sheath of the introducer set should be inserted into the subclavian vein under fluoroscopic control. Elevation of the ipsilateral shoulder assists passage of the peel-away sheath and subsequently the catheter from the subclavian vein into the superior vena cava.
Results:
This technique has been used successfully to establish surgical central venous access in the majority of children at the Women's and Children's Hospital, Adelaide, South Australia, over a 3-year period.
Conclusions:
With the modifications described this technique may be safely applied to the paediatric age group.