Digital electronic communication between ICU ventilators and computers and printers
Related Experiment Video
Updated: Oct 13, 2026

A Detailed Protocol for Physiological Parameters Acquisition and Analysis in Neurosurgical Critical Patients
Published on: October 17, 2017
T D East1, W H Young, R M Gardner
1University of Utah.

Unlabelled:
Although many modern ICU ventilators offer the option of electronic communication, most of these systems are not used because there is a huge communication gap between the ventilator and the computer it might be connected to. When such systems are now used, a large part of what is communicated is artifactual and misleading. We need to overcome both legal and knowledge barriers in the effort to provide seamless communication between ventilators and computers. With regard to the specific issues raised in this paper, here are our answers. Issue #1: Is it essential to have a digital electronic communication port on an ICU ventilator?
Answer:
No, it is not essential. The purpose of the mechanical ventilator is to support pulmonary ventilation by supplying gas and pressure. There is no vital role for digital communication in the gas-delivery function of the ventilator; however, in the future it will be essential to have effective electronic communication in order to guarantee accurate and timely charting. Issue #2: What impact does electronic communication between a ventilator and a computer have on patient outcome?
Answer:
Our preliminary data show that electronic communication can reduce the number of charting errors and can improve the timeliness of data entry. However, there is little evidence, other than anecdotal, that this has any impact on patient outcome. Automated charting has been shown to reduce the time spent on charting. This time-savings could be used to increase time spent in direct patient care, but there is no conclusive evidence that this occurs. In fact, one report on computerized charting systems indicates that the result is less time spent in direct patient care. Issue #3: If electronic communication is to be effective in the future, how should these interfaces be configured for mechanical ventilation?
Answer:
We recommend an optimal algorithm for automated respiratory care charting that has been suggested. Sampling frequency: Sample data from the ventilator every 10 seconds. Ventilator-setting changes: Report every new setting if change lasts more than 3 minutes. Measured respiratory care data: Filter raw MIB-collected data with a 3-minute moving-median filter. Report one filtered value every hour for each variable. In addition, use a threshold table (Table 3) to define significant events. Report changes that remain above threshold more than 3 minutes. Report all measured respiratory-care data 1 minute following any ventilator-mode changes.


Related Concept Videos
 01:18
Guidelines and Strategies for Safe Computer Charting
Maintain Confidentiality and Security:
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
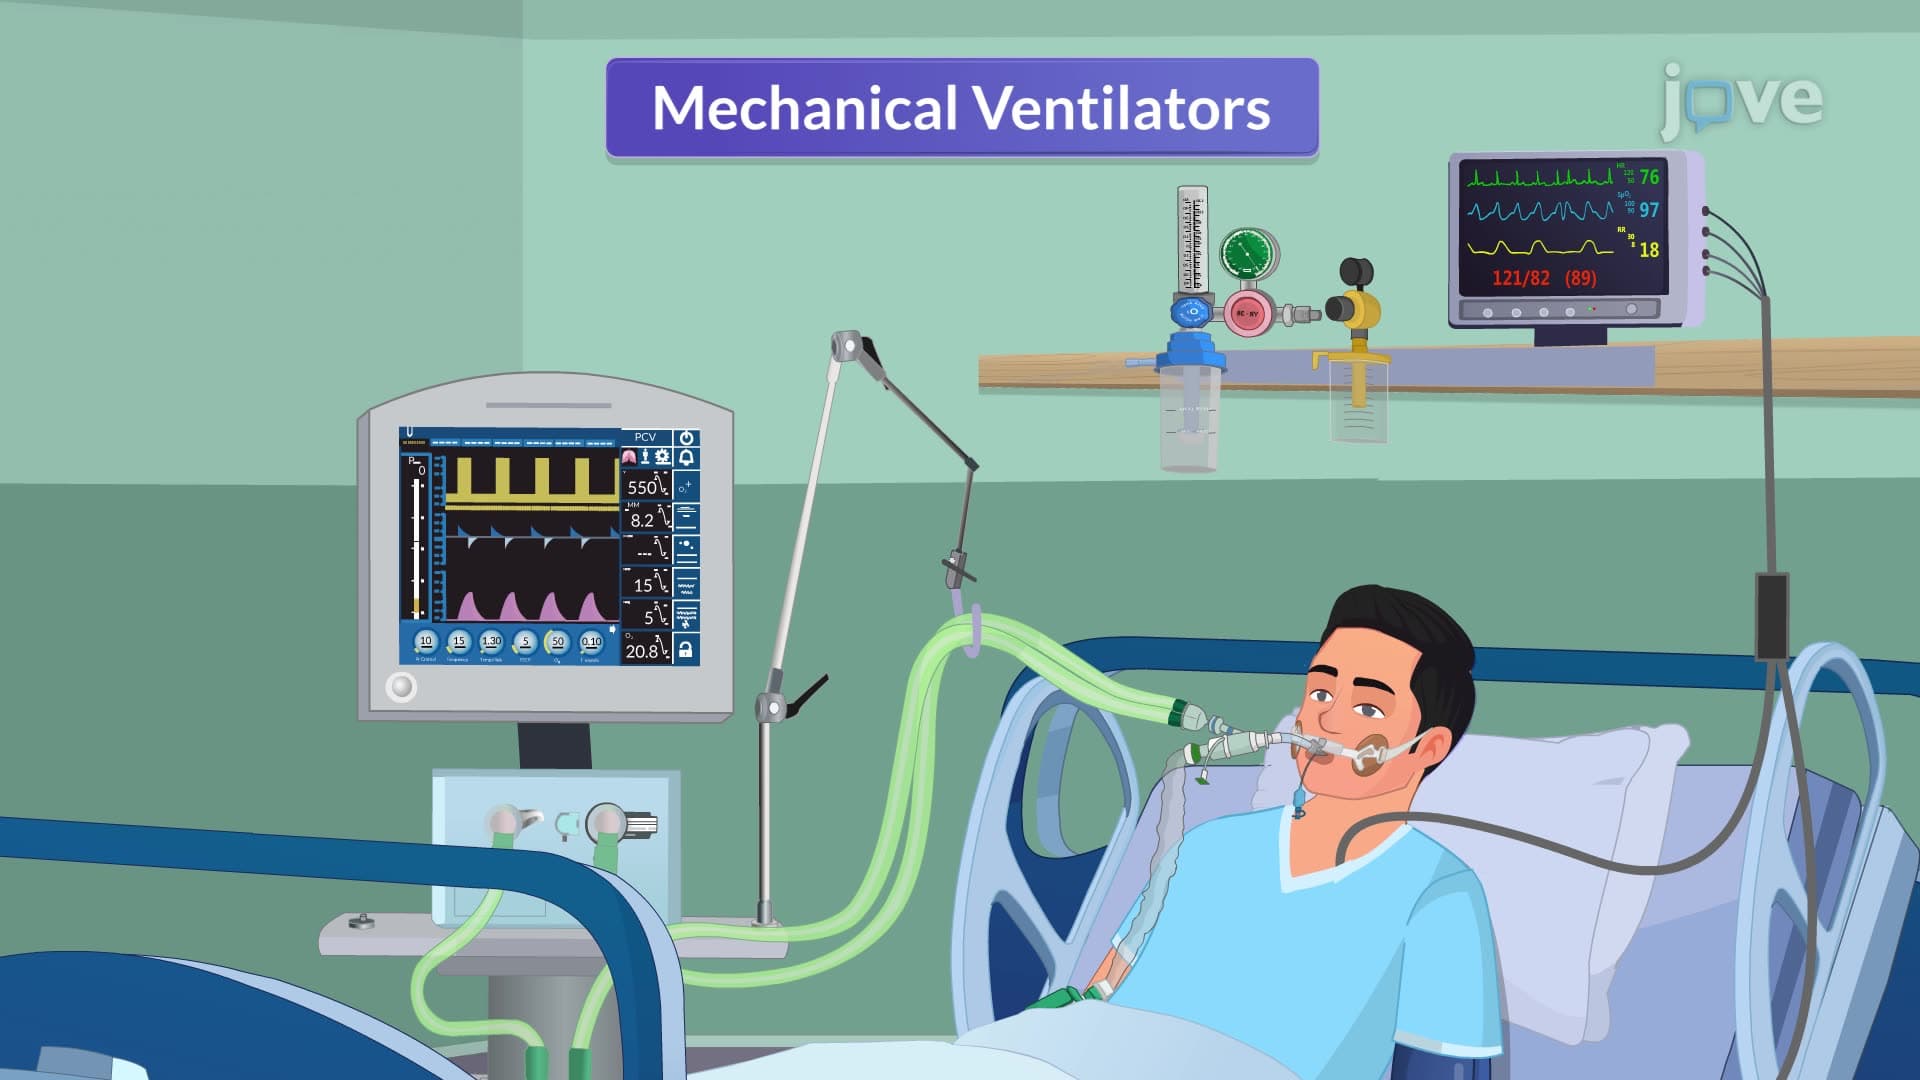 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...