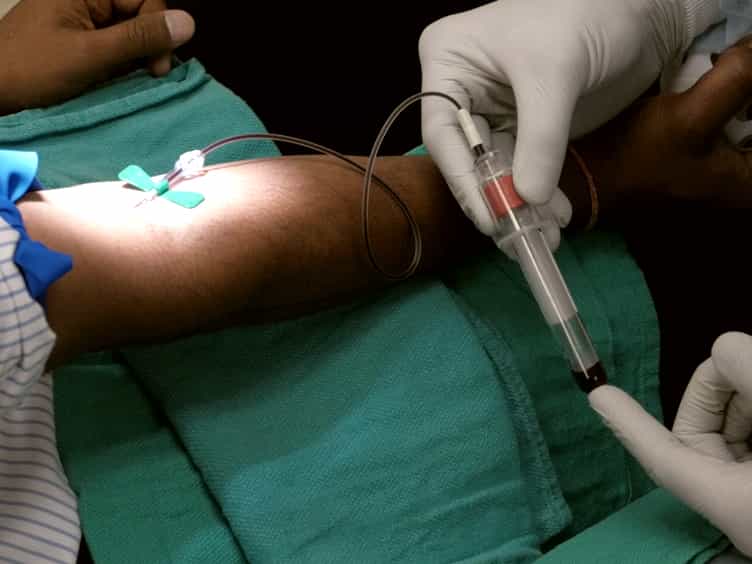
Related Experiment Video
Updated: Oct 23, 2026

Production of Autologous Platelet-Rich Plasma for Boosting In Vitro Human Fibroblast Expansion
Published on: February 24, 2021
Intraoperative hemodilution and autologous platelet rich plasma collection: two techniques for collecting fresh
1University of Pittsburgh Medical Center, Central Blood Bank, PA 15219, USA.

Intraoperative hemodilution (IH) and autologous platelet rich plasma (APRP) collection are two techniques used to obtain autologous blood in the operating room. They have been used to reduce allogeneic blood exposure in patients undergoing both cardiac and non-cardiac surgery. Both components have the advantage of providing fresh blood not subject to the storage lesion. Whole blood (IH) or platelet rich plasma is removed from the patient as anesthesia is induced and replaced with acellular fluid. The blood is transfused back after bypass or major bleeding has ceased. Although used commonly, the data supporting the use of either technique are controversial. Methodologic problems which have confounded studies evaluating their utility include: poorly defined transfusion criteria, concommitant use of other blood conservation techniques (i.e. cell salvage, pharmacologic agents, hypothermia, controlled hypotension) and changing transfusion practices with greater tolerance of normovolemic anemia. Randomized controlled studies with well defined up to date transfusion criteria are needed to identify patients likely to benefit from these techniques.
Intraoperative hemodilution (IH) and autologous platelet rich plasma (APRP) collection are two techniques used to obtain autologous blood in the operating room. They have been used to reduce allogeneic blood exposure in patients undergoing both cardiac and non-cardiac surgery. Both components have the advantage of providing fresh blood not subject to the storage lesion. Whole blood (IH) or platelet rich plasma is removed from the patient as anesthesia is induced and replaced with acellular fluid. The blood is transfused back after bypass or major bleeding has ceased. Although used commonly, the data supporting the use of either technique are controversial. Methodologic problems which have confounded studies evaluating their utility include: poorly defined transfusion criteria, concommitant use of other blood conservation techniques (i.e. cell salvage, pharmacologic agents, hypothermia, controlled hypotension) and changing transfusion practices with greater tolerance of normovolemic anemia. Randomized controlled studies with well defined up to date transfusion criteria are needed to identify patients likely to benefit from these techniques.