Related Experiment Video
Updated: Oct 23, 2026

A Preclinical Controlled Cortical Impact Model for Traumatic Hemorrhage Contusion and Neuroinflammation
Published on: June 10, 2020
Ontogenetic aspects of traumatic brain edema--facts and suggestions
1Institute of Pathophysiology, Friedrich Schiller University, Jena, Germany.

Insights
Diffuse brain swelling (DBS) in children after traumatic brain injury (TBI) is common and harmful. Immature brains show unique edema mechanisms, including impaired blood-brain barrier function and altered cellular responses, leading to secondary injury.
Area of Science:
- Neuroscience
- Pediatric Traumatology
- Brain Injury Research
Background:
- Diffuse brain swelling (DBS) is more prevalent and impactful in children following severe traumatic brain injury (TBI).
- Limited research exists on DBS pathophysiology in young animal models, despite clinical observations of worse outcomes in pediatric populations.
- Immature brains exhibit distinct edema formation mechanisms compared to adult brains after TBI.
Purpose of the Study:
- To investigate the pathogenetic mechanisms of diffuse brain swelling (DBS) in the immature brain following traumatic brain injury (TBI).
- To explore the differences in edema formation between pediatric and adult brains post-TBI.
- To understand the role of oxidative stress and cellular mechanisms in pediatric DBS.
Main Methods:
- Evaluation of edema components (vasogenic and cytotoxic) in immature brains post-TBI.
- Assessment of blood-brain barrier integrity and oxidative stress markers.
- Analysis of cerebral blood flow (CBF) and cellular ion accumulation mechanisms.
Main Results:
- Evidence suggests both vasogenic and cytotoxic edema contribute to DBS in immature brains.
- The blood-brain barrier is vulnerable to oxidative stress due to diminished antioxidative capacity post-TBI.
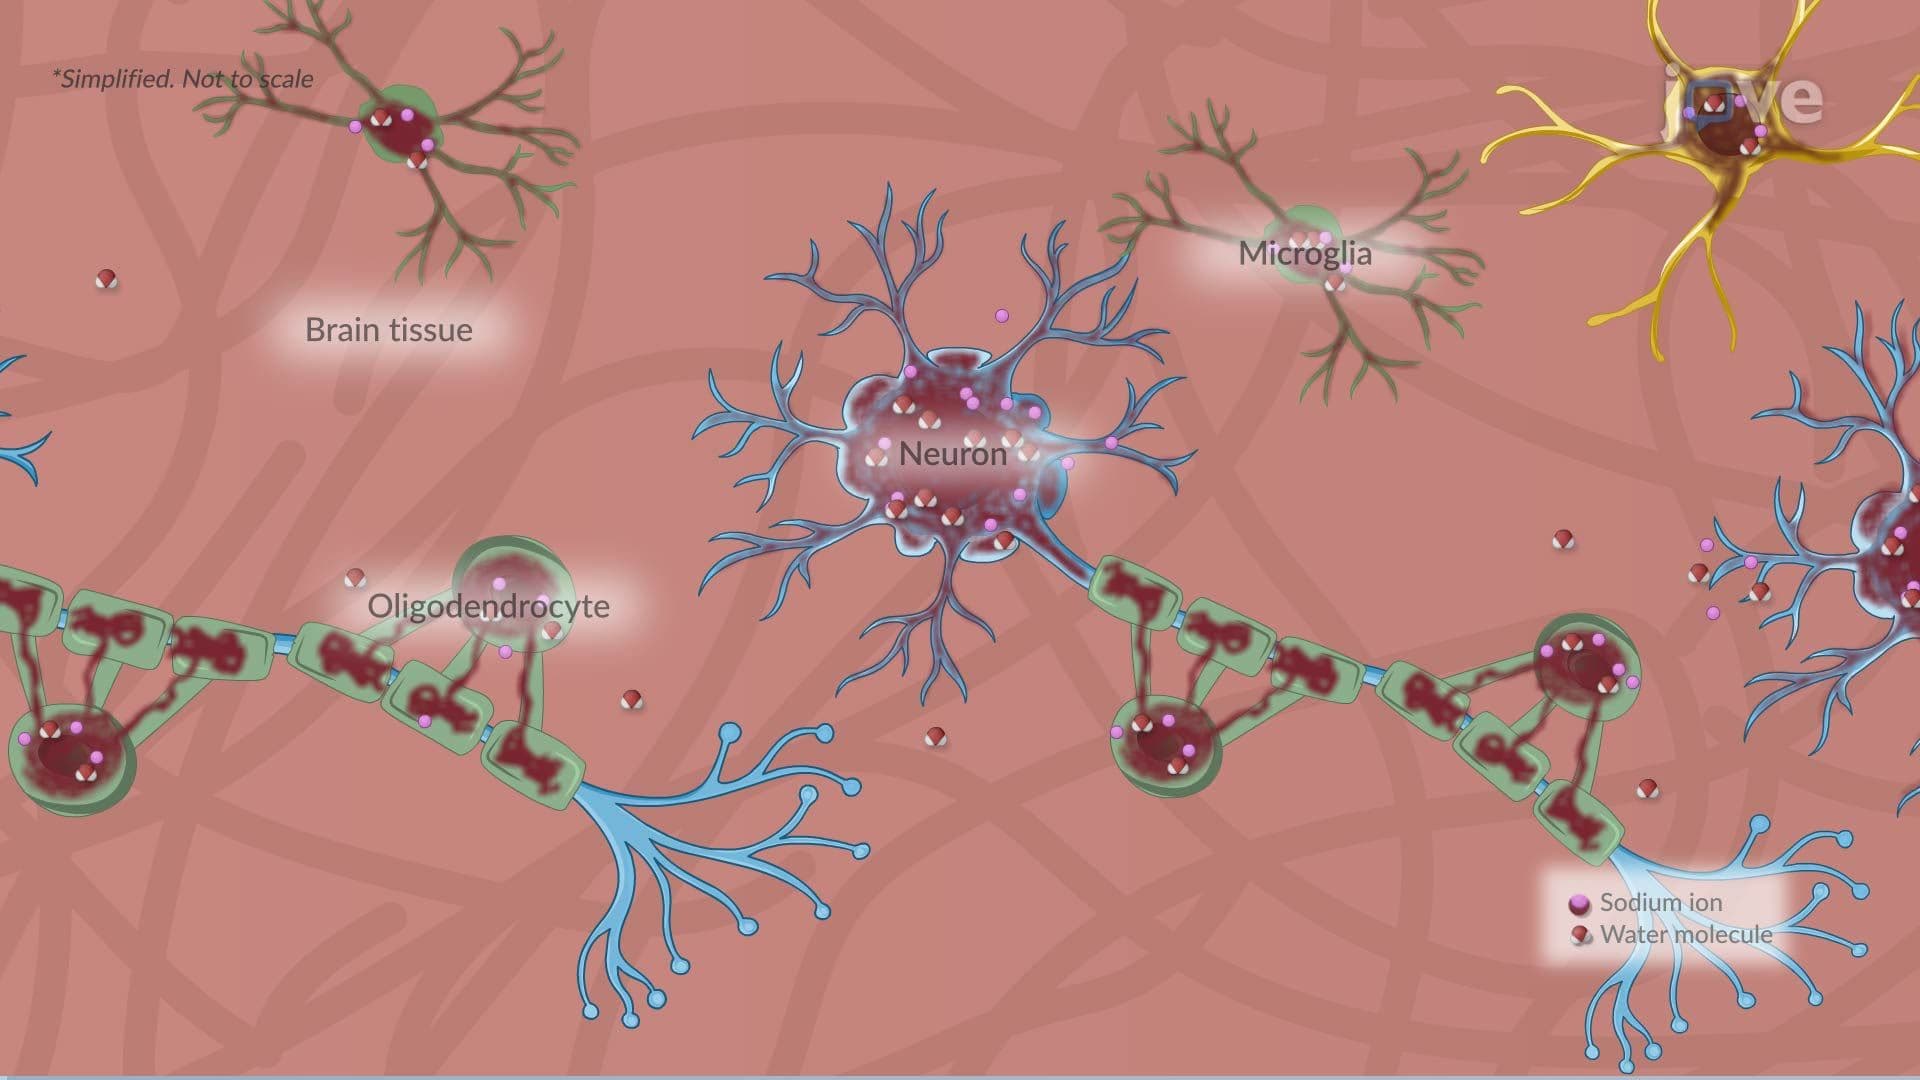
- Cytotoxic edema may result from sustained cerebral hypoperfusion and increased NMDA receptor expression, leading to intracellular sodium accumulation.
Conclusions:
- Diffuse brain swelling (DBS) in children after TBI involves unique pathophysiological pathways distinct from adults.
- Oxidative stress and cellular mechanisms, including hypoperfusion and excitotoxicity, play critical roles in pediatric DBS.
- Understanding these mechanisms is crucial for managing intracranial pressure and preventing secondary brain injury in pediatric TBI patients.
Abstract:
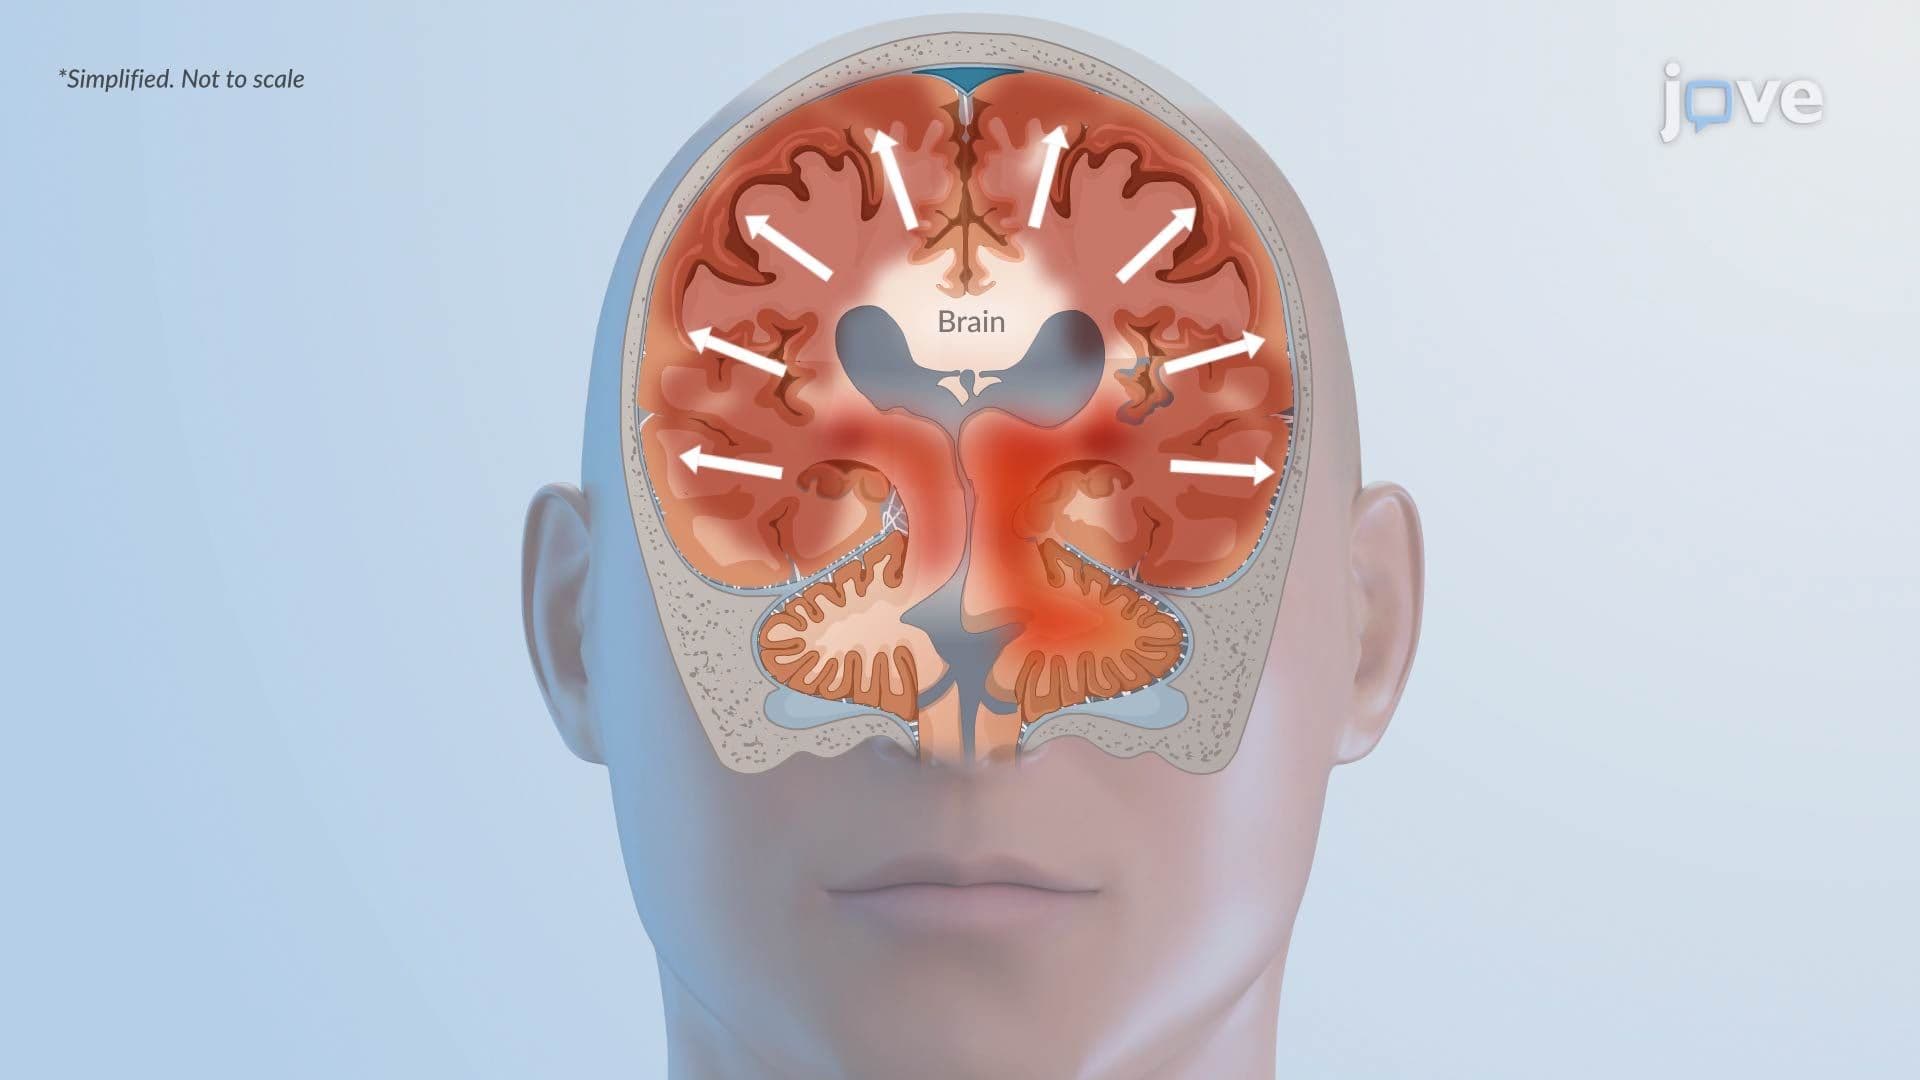
Diffuse brain swelling (DBS) after severe traumatic brain injury (TBI) occurs more commonly in children than adults. Most of the recent clinical studies suggest that young children are more negatively affected by DBS. Until now studies in young animals in which the pathophysiology of DBS was evaluated remained seldom. However, pathogenetic mechanisms of edema formation after TBI in the immature brain appeared to be different in comparison to adult brains. There are evidences that vasogenic as well as cytotoxic edema components may be responsible for the development of DBS. Besides mechanical disturbance, the blood-brain barrier seems to be strongly endangered by oxidative stress after TBI because regional antioxidative capacity is obviously diminished. In addition, cytotoxic components of DBS may be caused by at least two different mechanisms. First, it was shown that a sustained posttraumatic cerebral hypoperfusion occurs in the immature brain. Moreover, a transient increase of NMDA receptor expression at this period of life may be responsible for an increased threat of intracellular sodium ion accumulation in brain cells. Obviously, brain swelling can be detrimental because it can elevate intracranial pressure, impair CBF, and may represent ongoing secondary brain injury.


Related Concept Videos
 01:22
Cerebral Edema ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:21
Cytotoxic Edema: Pathophysiology
 01:28
Traumatic Brain Injury l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:26
Bacterial Meningitis II: Pathophysiology