Related Experiment Video
Updated: Oct 23, 2026
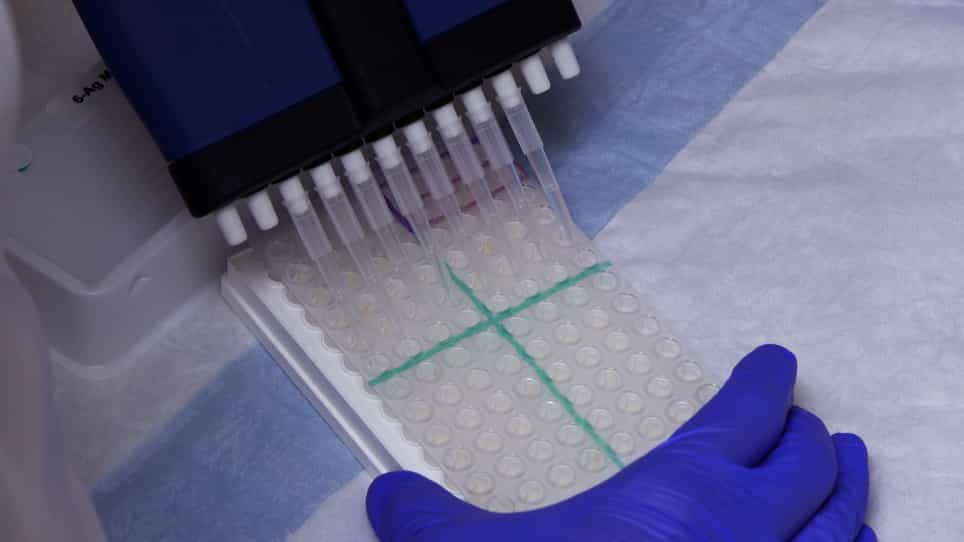
A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Anti-insulin antibodies and birth weight in pregnancies complicated by diabetes
P A Weiss1, F Kainer, P Pürstner
1Department of Obstetrics and Gynecology, University of Graz, Austria.

Free insulin cannot cross the placenta but insulin complexed to anti-insulin antibodies has been demonstrated in cord blood. We studied whether antibody-bound insulin in diabetic patients can evoke fetal macrosomia independently of maternal metabolic control. In 457 non insulin-treated controls and 173 insulin-treated diabetic patients we measured 1187 anti-insulin antibody levels and maternal blood glucose, maternal fructosamine, cord blood insulin, cord blood C-peptide, cord blood fructosamine and amniotic fluid insulin. Mean anti-insulin antibody levels in maternal blood and cord blood were significantly higher in insulin treated diabetic patients (4.6 and 5.4 U/ml) than in controls (1.8 and 1.7 U/ml) with maxima of 89.2 in maternal and 120.0 U/ml in cord blood, respectively. In insulin treated diabetic patients 16.6% (maternal blood) and 22% (cord blood) anti-insulin antibody levels were above the 97th percentile. There was a high significant correlation between maternal and cord blood anti-insulin antibodies (R = 0.987, P = < 0.0001), but no correlation of anti-insulin antibodies with maternal (glucose, fructosamine) or fetal (insulin, C-peptide, and fructosamine in cord blood, amniotic fluid insulin) metabolic parameters. While maternal and fetal metabolic parameters correlated with birth weight neither maternal nor cord blood anti-insulin antibody levels correlated with birth weight. These findings do not support the hypothesis that maternal anti-insulin antibodies independently influence fetal weight.
Free insulin cannot cross the placenta but insulin complexed to anti-insulin antibodies has been demonstrated in cord blood. We studied whether antibody-bound insulin in diabetic patients can evoke fetal macrosomia independently of maternal metabolic control. In 457 non insulin-treated controls and 173 insulin-treated diabetic patients we measured 1187 anti-insulin antibody levels and maternal blood glucose, maternal fructosamine, cord blood insulin, cord blood C-peptide, cord blood fructosamine and amniotic fluid insulin. Mean anti-insulin antibody levels in maternal blood and cord blood were significantly higher in insulin treated diabetic patients (4.6 and 5.4 U/ml) than in controls (1.8 and 1.7 U/ml) with maxima of 89.2 in maternal and 120.0 U/ml in cord blood, respectively. In insulin treated diabetic patients 16.6% (maternal blood) and 22% (cord blood) anti-insulin antibody levels were above the 97th percentile. There was a high significant correlation between maternal and cord blood anti-insulin antibodies (R = 0.987, P = < 0.0001), but no correlation of anti-insulin antibodies with maternal (glucose, fructosamine) or fetal (insulin, C-peptide, and fructosamine in cord blood, amniotic fluid insulin) metabolic parameters. While maternal and fetal metabolic parameters correlated with birth weight neither maternal nor cord blood anti-insulin antibody levels correlated with birth weight. These findings do not support the hypothesis that maternal anti-insulin antibodies independently influence fetal weight.

Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:26
Diabetes Mellitus: Introduction