Related Experiment Video
Updated: Oct 23, 2026

Instrumentation of Near-term Fetal Sheep for Multivariate Chronic Non-anesthetized Recordings
Published on: October 25, 2015
Human fetal and maternal noradrenaline responses to invasive procedures
X Giannakoulopoulos1, J Teixeira, N Fisk
1Division of Paediatrics, Obstetrics and Gynaecology, Imperial College School of Medicine, Queen Charlotte's & Chelsea Hospital, London, United Kingdom.

Fetal and maternal plasma noradrenaline responses to invasive procedures were determined in pregnancies of 18 to 37 wk gestation. Fetal umbilical venous blood sampling was performed either from the placental cord insertion, which is not innervated, or the intrahepatic vein, which is innervated, and thus may be more stressful for the fetus. Samples from diagnostic procedures, as well as from transfusion procedures, were compared between the two sites. Fetal plasma levels were significantly elevated in blood samples obtained from the intrahepatic vein compared with those from the placental cord insertion during diagnostic procedures [p < 0.05, geometric means and 95% confidence intervals (CI) were 0.67 nmol/L (0.43-1.04) and 0.36 nmol/L (0.25-0.54), respectively]. Plasma levels in samples taken before transfusion from the intrahepatic vein were also significantly higher than those from the placental cord insertion. After transfusion, there was a significant rise in fetal plasma noradrenaline levels at both sites; however, after transfusion through the intrahepatic vein, the rise was substantially greater than after transfusion through the placental cord insertion (p < 0.05, change, mean deltaNA, and 95% CI were 0.67 (0.37-1.22), and 0.20 (0.12-0.33), respectively). The deltaNA was significantly associated with the duration of the stimulus (the time the needle remained in situ) (p = 0.05, adjusted R2 = 0.48) and with gestational age. Maternal levels rose substantially and equally after transfusions at either site (mean deltaNA and 95% CI, 6.46 nmol/L, 1.74 to 11.18 and 9.49 nmol/L, 6.24 to 12.75 for the intrahepatic vein and placental cord insertion groups, respectively). There was no significant correlation between baseline fetal and maternal levels (r = 0.08, n = 41) or between deltaNA pre- and posttransfusion maternal and fetal values in either group. These results indicate that the fetus is capable of mounting an independent noradrenaline stress response to a needle transgressing its trunk from 18 wk gestation. The effect was observable in samples taken at a mean of 5.6 min after needling. The lack of correlation between maternal and fetal levels suggests that virtually no noradrenaline crosses the placenta directly, and that the observed fetal responses are not due to direct transport from the mother.
Fetal and maternal plasma noradrenaline responses to invasive procedures were determined in pregnancies of 18 to 37 wk gestation. Fetal umbilical venous blood sampling was performed either from the placental cord insertion, which is not innervated, or the intrahepatic vein, which is innervated, and thus may be more stressful for the fetus. Samples from diagnostic procedures, as well as from transfusion procedures, were compared between the two sites. Fetal plasma levels were significantly elevated in blood samples obtained from the intrahepatic vein compared with those from the placental cord insertion during diagnostic procedures [p < 0.05, geometric means and 95% confidence intervals (CI) were 0.67 nmol/L (0.43-1.04) and 0.36 nmol/L (0.25-0.54), respectively]. Plasma levels in samples taken before transfusion from the intrahepatic vein were also significantly higher than those from the placental cord insertion. After transfusion, there was a significant rise in fetal plasma noradrenaline levels at both sites; however, after transfusion through the intrahepatic vein, the rise was substantially greater than after transfusion through the placental cord insertion (p < 0.05, change, mean deltaNA, and 95% CI were 0.67 (0.37-1.22), and 0.20 (0.12-0.33), respectively). The deltaNA was significantly associated with the duration of the stimulus (the time the needle remained in situ) (p = 0.05, adjusted R2 = 0.48) and with gestational age. Maternal levels rose substantially and equally after transfusions at either site (mean deltaNA and 95% CI, 6.46 nmol/L, 1.74 to 11.18 and 9.49 nmol/L, 6.24 to 12.75 for the intrahepatic vein and placental cord insertion groups, respectively). There was no significant correlation between baseline fetal and maternal levels (r = 0.08, n = 41) or between deltaNA pre- and posttransfusion maternal and fetal values in either group. These results indicate that the fetus is capable of mounting an independent noradrenaline stress response to a needle transgressing its trunk from 18 wk gestation. The effect was observable in samples taken at a mean of 5.6 min after needling. The lack of correlation between maternal and fetal levels suggests that virtually no noradrenaline crosses the placenta directly, and that the observed fetal responses are not due to direct transport from the mother.

Related Concept Videos
 01:27
Adrenergic Neurons: Neurotransmission
Synthesis: Catecholamine synthesis requires tyrosine, which is taken...
 01:26
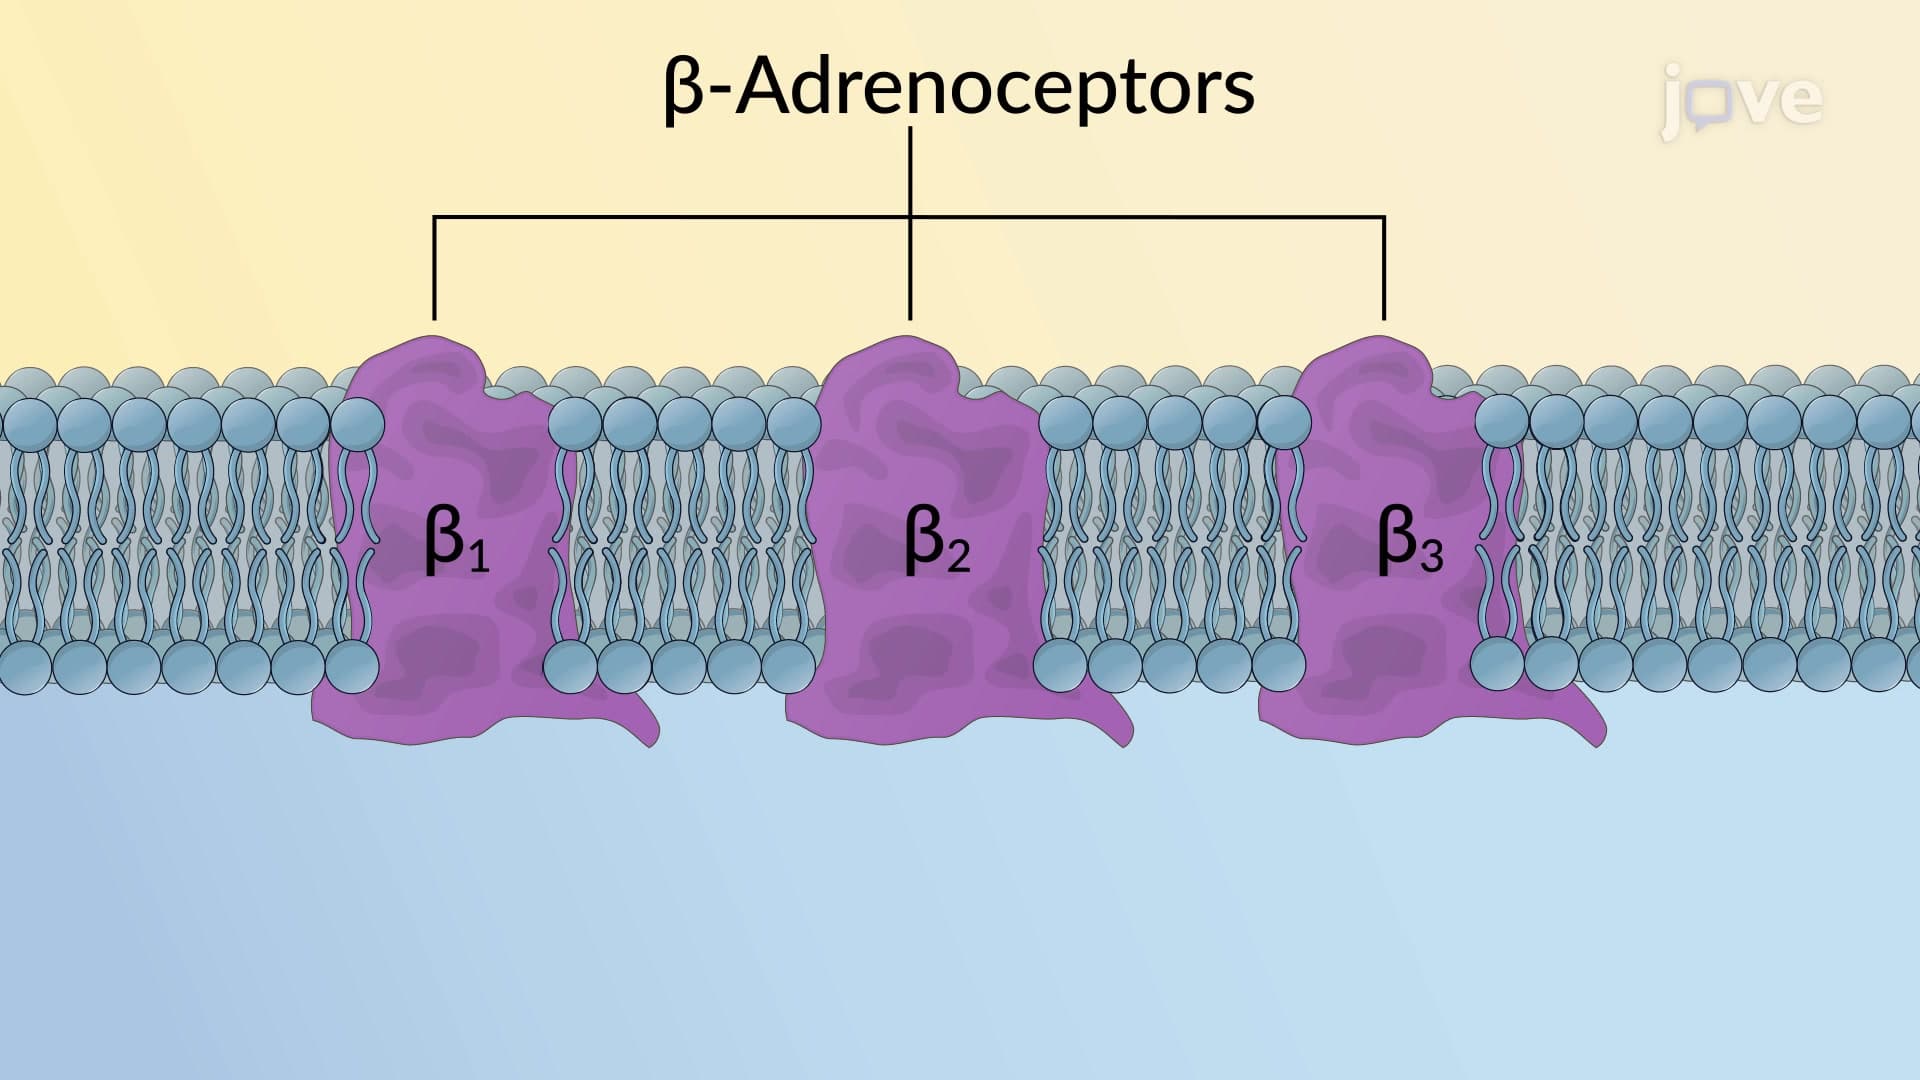
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
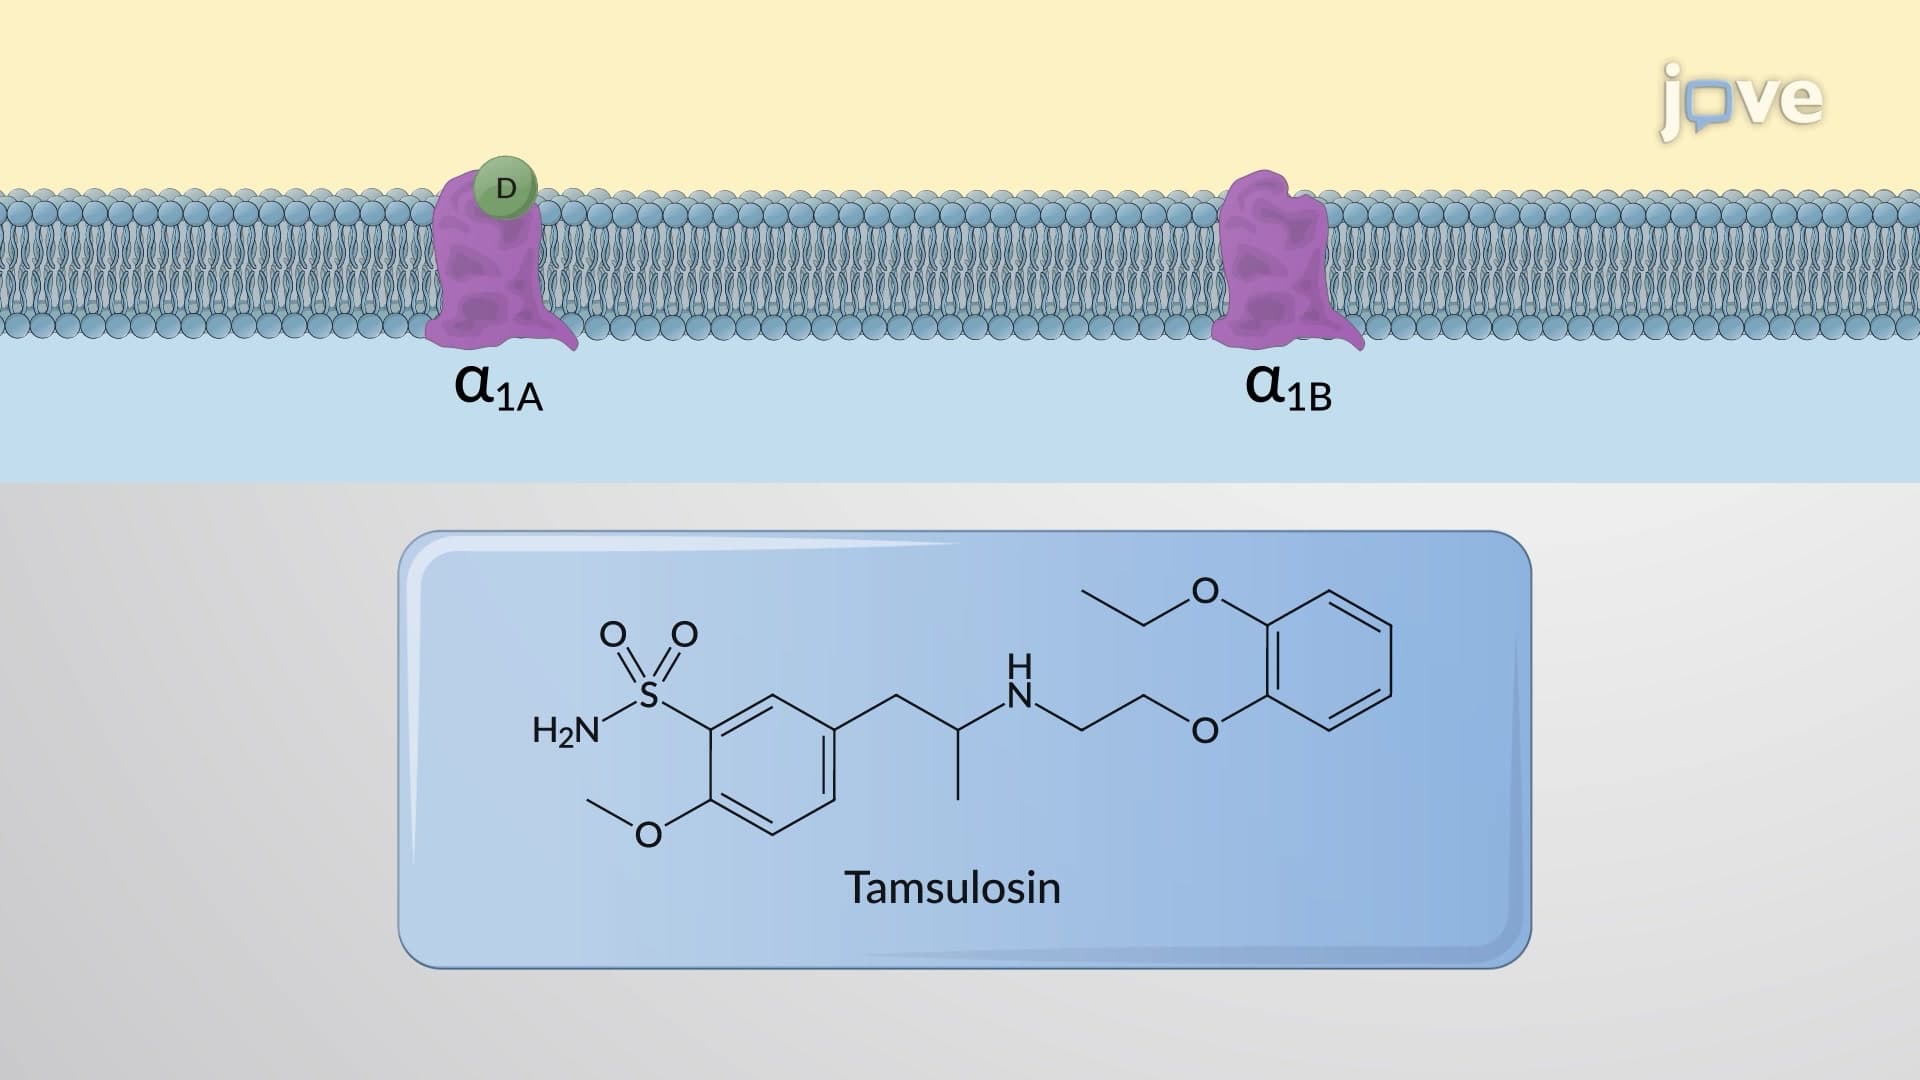
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:27
Sympathetic Pathways: Collateral Ganglia and Adrenal Medulla
Collateral Ganglia
Sympathetic preganglionic axons reach the collateral ganglia along the route of splanchnic nerves. These nerves bypass the sympathetic trunk and communicate with sympathetic postganglionic neurons housed in the prevertebral ganglia. These ganglia supply the organs of the abdominopelvic cavity.
The greater splanchnic nerve, formed by the...