Related Experiment Video
Updated: Aug 4, 2026
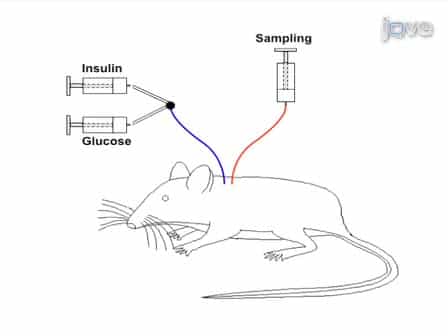

Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Exogenous hyperinsulinemia causes insulin resistance, hyperendothelinemia, and subsequent hypertension in rats
1Department of Physiology, National Yang-Ming University, Taipei, Taiwan, Republic of China.

In many clinical and animal studies, hypertension and insulin resistance coexist, but their mechanistic relationship is unclear. We explored the causal link between these two parameters in a rat model with chronic hyperinsulinemia induced with human insulin (1 U/d) released from subcutaneously implanted minipumps. Rats with saline minipumps served as a control. During the first experiment, plasma levels of insulin and glucose and the systolic blood pressure of the two groups were continuously monitored for 17 days. In the subsequent four experiments, rats were killed on days 10 and 13 to measure plasma endothelin-1 (ET-1) levels and the glucose transport into and insulin and ET-1 binding of isolated adipocytes. In one experiment, rats were tested for oral glucose tolerance on days 10 and 13. In another experiment, ET-1 binding to the aortic plasma membrane was also determined. The results showed that rats became hyperinsulinemic throughout the experimental period by the instillation of exogenous insulin. Hyperinsulinemic rats were consistently hypoglycemic during the first day, but they became euglycemic thereafter, indicating an insulin-resistant state. Glucose intolerance was obvious by day 10, but significant hypertension was not detected until the 11th day on insulin infusion. Compared with the saline controls, insulin-infused rats had an increase of plasma ET-1 levels but a decrease of both basal and insulin-stimulated glucose transport into adipocytes. ET-1 binding to adipocytes of the insulin-infused group was elevated significantly from day 10 through day 13. ET-1 binding to the aortic membranes, supposedly downregulated by the increased plasma ET-1 and hypertension, was similar to that found in the controls on day 13. These results imply that hyperinsulinemia in rats could lead to hypertension via the elevation of plasma ET-1 levels together with an unaltered vascular binding of ET-1, which was probably unrelated to the insulin resistance.
In many clinical and animal studies, hypertension and insulin resistance coexist, but their mechanistic relationship is unclear. We explored the causal link between these two parameters in a rat model with chronic hyperinsulinemia induced with human insulin (1 U/d) released from subcutaneously implanted minipumps. Rats with saline minipumps served as a control. During the first experiment, plasma levels of insulin and glucose and the systolic blood pressure of the two groups were continuously monitored for 17 days. In the subsequent four experiments, rats were killed on days 10 and 13 to measure plasma endothelin-1 (ET-1) levels and the glucose transport into and insulin and ET-1 binding of isolated adipocytes. In one experiment, rats were tested for oral glucose tolerance on days 10 and 13. In another experiment, ET-1 binding to the aortic plasma membrane was also determined. The results showed that rats became hyperinsulinemic throughout the experimental period by the instillation of exogenous insulin. Hyperinsulinemic rats were consistently hypoglycemic during the first day, but they became euglycemic thereafter, indicating an insulin-resistant state. Glucose intolerance was obvious by day 10, but significant hypertension was not detected until the 11th day on insulin infusion. Compared with the saline controls, insulin-infused rats had an increase of plasma ET-1 levels but a decrease of both basal and insulin-stimulated glucose transport into adipocytes. ET-1 binding to adipocytes of the insulin-infused group was elevated significantly from day 10 through day 13. ET-1 binding to the aortic membranes, supposedly downregulated by the increased plasma ET-1 and hypertension, was similar to that found in the controls on day 13. These results imply that hyperinsulinemia in rats could lead to hypertension via the elevation of plasma ET-1 levels together with an unaltered vascular binding of ET-1, which was probably unrelated to the insulin resistance.


Related Concept Videos
 01:28
Insulin: The Receptor and Signaling Pathways
 01:26
Diabetes Mellitus: Introduction
 01:26
Type II Diabetes I: Introduction
 01:24
Type II Diabetes II: Pathophysiology
 01:29
Hyperglycemia
 01:28
Diabetic Nephropathy