Conservative intestinal surgery to avoid short-bowel syndrome in multiple intestinal atresias and necrotizing enterocolitis: 6 cases treated by multiple anastomoses and Santulli-type enterostomy
Related Experiment Video
Updated: Oct 23, 2026
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
E Sapin1, E Carricaburu, D De Boissieu
1Department of Pediatric Surgery, Hôpital St Vincent de Paul, CHU Cochin Port-Royal, University School of Medicine René Descartes, Paris, France.

Insights
Multiple intestinal atresia (MIA) in neonates can lead to short-gut syndrome. Surgical intervention with enterostomy and multiple anastomoses effectively increases intestinal length, improving outcomes for affected infants.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Neonatal Medicine
Background:
- Neonates with multiple intestinal atresia (MIA) face a high risk of developing short-gut syndrome.
- Surgical management aims to preserve intestinal length and function.
Purpose of the Study:
- To evaluate the efficacy of a surgical technique involving proximal enterostomy and multiple anastomoses in neonates with MIA.
- To assess the impact of this technique on intestinal length, feeding, and long-term outcomes.
Main Methods:
- Five neonates with MIA and one infant with necrotizing enterocolitis (NEC) underwent surgery.
- The procedure included a proximal enterostomy, side-to-end anastomosis, and multiple end-to-end anastomoses between intervening intestinal segments.
- Enterostomies were reversed after a mean of 7 weeks.
Main Results:
- The surgical technique significantly increased achieved intestinal length compared to estimated lengths without intervention.
- Infants were weaned from parenteral nutrition (PN) after a mean of 90 days.
- Follow-up at a mean of 31 months showed good growth, development, and adaptation to enteral feeding.
Conclusions:
- This surgical approach, combining enterostomy with multiple intestinal anastomoses, is effective in managing MIA.
- The technique facilitates jejunal decompression, promotes distal bowel enlargement, and prevents short-gut syndrome.
- It offers a superior alternative to extensive resection of hypertrophied proximal bowel in MIA cases.
Abstract:
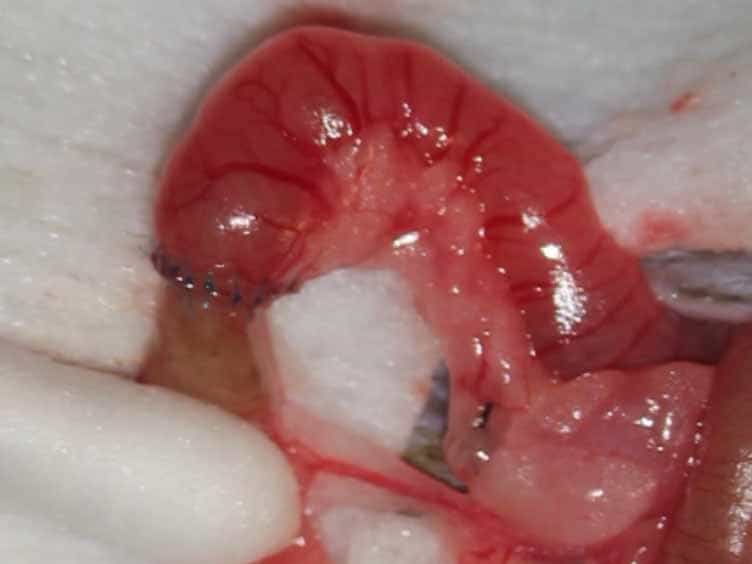
Neonates with multiple sites of intestinal atresia (MIA) may be predisposed to short-gut syndrome. Anastomoses of the intervening segments may prevent this complication. 5 neonates with MIA, one of them with a gastroschisis, were operated on: a proximal enterostomy was constructed, a side-to-end anastomosis as described by Santulli and several end-to-end anastomoses between the intervening intestinal segments (n = 3 to 7) were performed. An additional infant, initially operated on for a necrotizing enterocolitis (NEC) was managed with the same surgical procedure. Without use of this technique, the remaining length of small intestine would have been 28, 27, 40, 58, 70 and 7 cm. This technique enabled an intestinal length of 49, 54, 96, 107, 92 and 93 cm respectively to be achieved. Ileocecal valve was present in all 5 cases with MIA, but resected in the case with NEC. The enterostomy was reversed 7 weeks later. The initial outcome (delay of enteral feeding, duration of parenteral nutrition) was good: the babies were weaned from parenteral nutrition (PN) after a mean time of 90 days (48 to 163 days). The prognosis (mean follow-up: 31 months, range 14 to 57) was good with regards to growth and development and length of time required before adaptation to normal enteral feedings and stools. This surgical method allows complete decompression of the proximal jejunum so that nutriment can pass into the distal bowel allowing it to enlarge. In cases of MIA, a long tapering proximal enteroplasty is a better procedure than resecting more than 5-10 cm of the proximal distended and hypertrophied bowel. We prefer to perform an enterostomy in association with multiple anastomoses between intervening intestinal segments. The enterostomy is preserved for long enough waiting period to enable the reversion of the histochemical and morphological changes that may have taken place in the bowel.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...