Current role of venography in the diagnosis of deep-vein thrombosis
Related Experiment Video
Updated: Oct 23, 2026
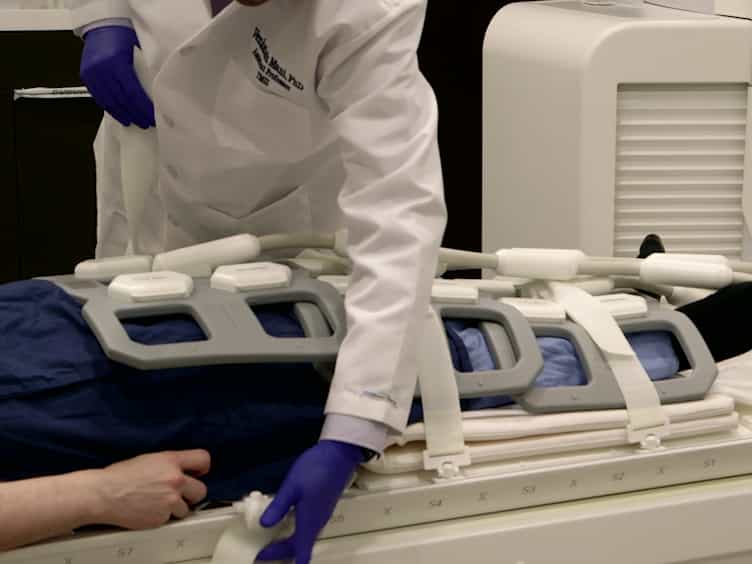
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015

Abstract:
The clinical diagnosis of deep vein thrombosis (DVT) is barely sensitive and specific. Thus, the clinical suspicion of DVT needs to be confirmed by objective testing. Venography has been for a long time the only reliable technique to confirm or rule-out the clinical suspicion of DVT. Furthermore, venography served as "gold standard" for the validation of non-invasive diagnostic methods for DVT. Among these methods, compressive real-time B-mode ultrasonography (CUS) has substantially reduced the need of performing venography, mainly in outpatients with clinical suspicion of DVT. However, indications for venography still remain in the three DVT patient categories. CUS is highly specific in patients with a first episode of clinically suspected DVT, so that positive patients can be treated with anticoagulants without any further testing. In CUS negative patients three options are available in order to rule-out clinically significant DVT: a) to repeat CUS at day 2 and 8; b) to associate D-dimer to CUS to rule-out DVT (negative D-dimer) or to reinforce surveillance (positive D-dimer); c) to perform venography on the same day. This last approach has been proposed in patients with negative CUS and high pretest clinical probability. CUS is highly specific in high risk patients with asymptomatic DVT and thus it could be used to make treatment decision in positive patients. However, CUS is less sensitive in asymptomatic than in symptomatic patients. Thus, venography remains the only available diagnostic technique to rule-out DVT in asymptomatic patients. In clinical practice, venography should be used on individual basis. In clinical research on DVT prophylaxis, venography should be used in the assessment of the end-point. However, three recent clinical trials on the prevention of post-discharge DVT has generated some uncertainty on the clinical relevance of asymptomatic venography detected DVT. Four to six weeks after discharge a high prevalence of venography detected DVT was observed, a finding disagreeing with the low incidence of clinically overt thromboembolic events at long-term follow-up. Two strategies are available in patients with recurrent symptomatic DVT: to follow-up patients with serial impedance plethysmograph and CUS after the first episode in order to pick-up a positive test in patients previously turned negative or to perform venography, a new intraluminal filling defect suggesting DVT recurrence.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system as it...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care