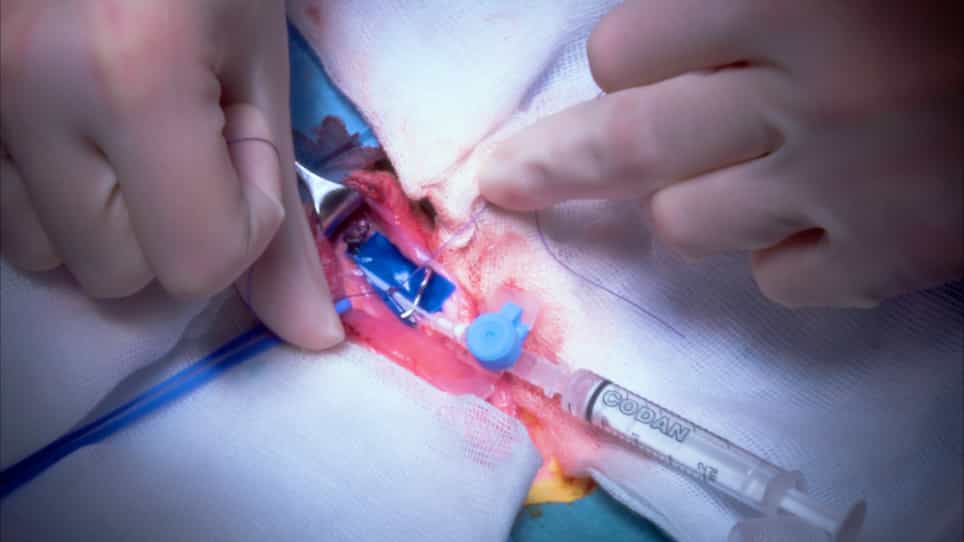
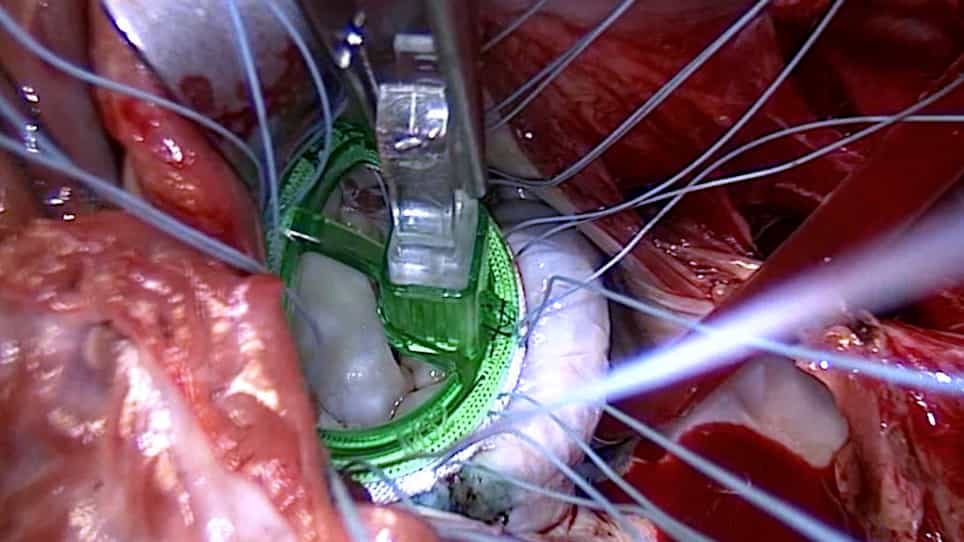
Three ventriculoplasty techniques applied to three left-ventricular pseudoaneurysms in the same patient
Related Experiment Video
Updated: Oct 23, 2026
Use of Two Intracorporeal Ventricular Assist Devices As a Total Artificial Heart
Published on: May 11, 2018
1The Department of Cardiovascular Surgery, Koşuyolu Heart and Research Hospital, Istanbul, Turkey.

Insights
This case study details a patient with recurrent left-ventricular pseudoaneurysms after surgery for coronary artery disease. Pectoral muscle flaps are proposed as a viable option for complex pseudoaneurysm re-repairs.
Area of Science:
- Cardiovascular Surgery
- Medical Case Reports
Background:
- A 59-year-old male with triple-vessel coronary artery disease underwent coronary artery bypass grafting and left-ventricular aneurysmectomy.
- Post-operative infection led to the development of a left-ventricular pseudoaneurysm four months after the initial surgery.
Observation:
- The patient experienced recurrent left-ventricular pseudoaneurysm formation and rupture, necessitating multiple surgical interventions.
- Three distinct surgical techniques were employed, including autologous pericardium patch with omental graft, diaphragmatic pericardial pedicle graft, and pectoralis major muscle flap implantation.
Findings:
- The final repair utilizing a pectoralis major muscle flap successfully prevented pseudoaneurysm reformation.
- The patient ultimately succumbed to cerebral malignancy six months after the last cardiac surgery.
Implications:
- This case highlights the challenges of managing complex, recurrent left-ventricular pseudoaneurysms secondary to post-aneurysmectomy infection.
- Pectoral muscle flaps represent a promising reconstructive option for intractable left-ventricular pseudoaneurysms, warranting further consideration in surgical practice.
Abstract:
A 59-year-old male patient underwent surgery for triple-vessel coronary artery disease and left-ventricular aneurysm in 1994. Four months after coronary artery bypass grafting and classical left-ventricular aneurysmectomy (with Teflon felt strips), a left-ventricular pseudoaneurysm developed due to infection, and this was treated surgically with an autologous glutaraldehyde-treated pericardium patch over which an omental pedicle graft was placed. Two months later, under emergent conditions, re-repair was performed with a diaphragmatic pericardial pedicle graft due to pseudoaneurysm reformation and rupture. A 3rd repair was required in a 3rd episode 8 months later. Sternocostal resection enabled implantation of the left pectoralis major muscle into the ventricular defect. Six months after the last surgical intervention, the patient died of cerebral malignancy. Pseudoaneurysm reformation, however, had not been observed. To our knowledge, our case is the 1st reported in the literature in which there have been 3 or more different operative techniques applied to 3 or more distinct episodes of pseudoaneurysm formation secondary to post-aneurysmectomy infection. We propose that pectoral muscle flaps be strongly considered as a material for re-repair of left-ventricular aneurysms.