Identification of thyroid hormone residues on serum thyroglobulin: a clue to the source of circulating thyroglobulin in thyroid diseases
Related Experiment Video
Updated: Oct 23, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
L Druetta1, H Bornet, G Sassolas
1Institut National de la Santë et de la Recherche Médicale, Unité 369, Faculté de Mëdecine Lyon-RTH Laénnec, 69372 Lyon, France.

Thyroglobulin (Tg) present in the serum of normal individuals and patients with thyroid disorders could be partly newly synthesized non-iodinated Tg and partly Tg containing iodine and hormone residues originating from the lumen of thyroid follicles. With the aim of examining the contribution of the latter source of Tg to the elevation of serum Tg concentration in thyroid pathophysiological situations, we devised a procedure to identify thyroxine (T4) and tri-iodothyronine (T3) residues on Tg from unfractionated serum. A two-step method, basedon (i)adsorption of Tg on an immobilized anti-human Tg (hTg) monoclonal antibody (mAb) and (ii)recognition of hormone residues on adsorbed Tg by binding of radioiodinated anti-T4 mAb and anti-T3 mAb, was used to analyze serum Tg from patients with either Graves' disease (GD), subacute thyroiditis (ST) or metastatic differentiated thyroid cancer (DTC). Purified hTg preparations with different iodine and hormone contents were used as reference. Adsorption of purified Tg and serum Tg on immobilized anti-hTg mAb ranged between 85 and 90% over a wide concentration range. Labeled anti-T4 and anti-T3 mAbs bound to adsorbed purified Tg in amounts related to its iodine content. Tg adsorbed from six out of six sera from ST exhibited anti-T4 and anti-T3 mAb binding activities. In contrast, significant mAb binding was only observed in one out of eight sera from untreated GD patients and in 1 out of 13 sera from patients with DTC. The patient with DTC, whose serum Tg contained T4 and T3, represented a case of hyperthyroidism caused by a metastatic follicular carcinoma. In conclusion, we have identified, for the first time, T4 and T3 residues on circulating Tg. The presence of Tg with hormone residues in serum is occasional in GD and DTC but is a common and probably distinctive feature of ST.
Thyroglobulin (Tg) present in the serum of normal individuals and patients with thyroid disorders could be partly newly synthesized non-iodinated Tg and partly Tg containing iodine and hormone residues originating from the lumen of thyroid follicles. With the aim of examining the contribution of the latter source of Tg to the elevation of serum Tg concentration in thyroid pathophysiological situations, we devised a procedure to identify thyroxine (T4) and tri-iodothyronine (T3) residues on Tg from unfractionated serum. A two-step method, basedon (i)adsorption of Tg on an immobilized anti-human Tg (hTg) monoclonal antibody (mAb) and (ii)recognition of hormone residues on adsorbed Tg by binding of radioiodinated anti-T4 mAb and anti-T3 mAb, was used to analyze serum Tg from patients with either Graves' disease (GD), subacute thyroiditis (ST) or metastatic differentiated thyroid cancer (DTC). Purified hTg preparations with different iodine and hormone contents were used as reference. Adsorption of purified Tg and serum Tg on immobilized anti-hTg mAb ranged between 85 and 90% over a wide concentration range. Labeled anti-T4 and anti-T3 mAbs bound to adsorbed purified Tg in amounts related to its iodine content. Tg adsorbed from six out of six sera from ST exhibited anti-T4 and anti-T3 mAb binding activities. In contrast, significant mAb binding was only observed in one out of eight sera from untreated GD patients and in 1 out of 13 sera from patients with DTC. The patient with DTC, whose serum Tg contained T4 and T3, represented a case of hyperthyroidism caused by a metastatic follicular carcinoma. In conclusion, we have identified, for the first time, T4 and T3 residues on circulating Tg. The presence of Tg with hormone residues in serum is occasional in GD and DTC but is a common and probably distinctive feature of ST.
Related Concept Videos
 01:20
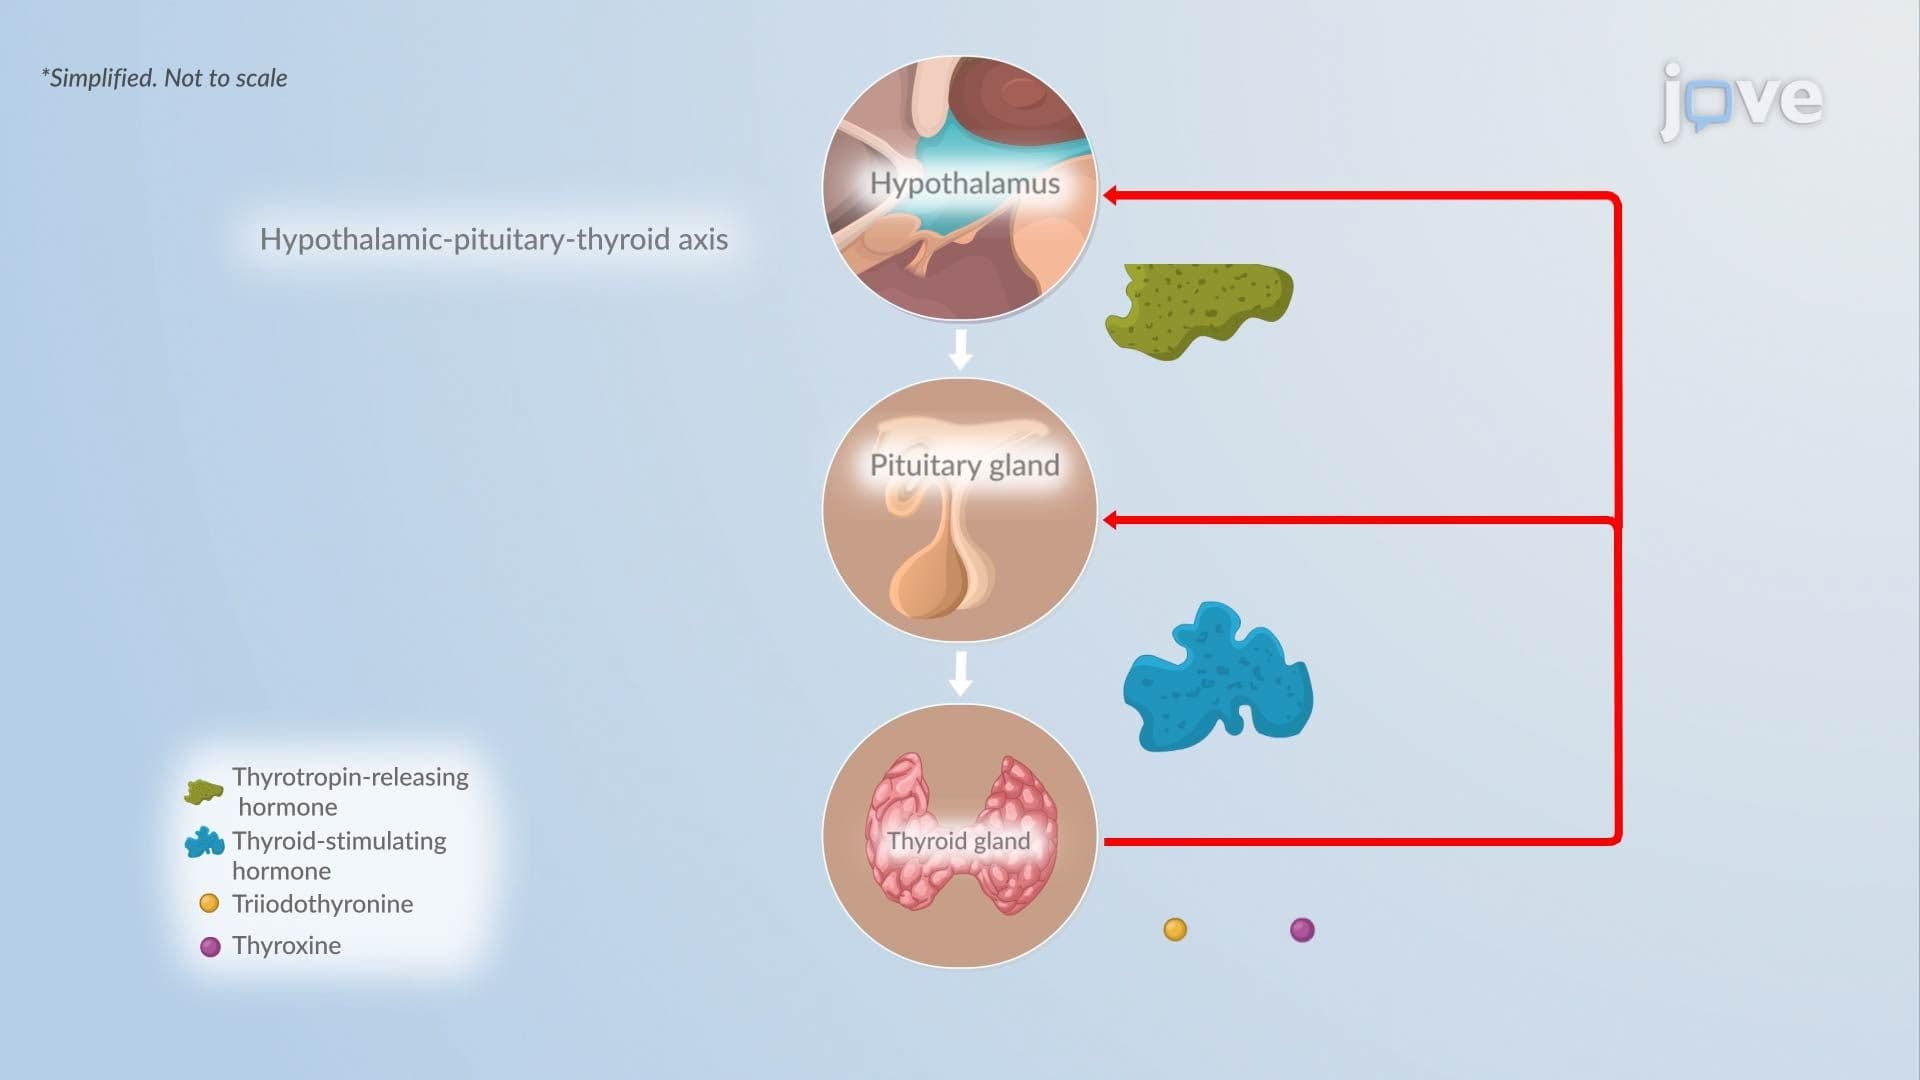
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
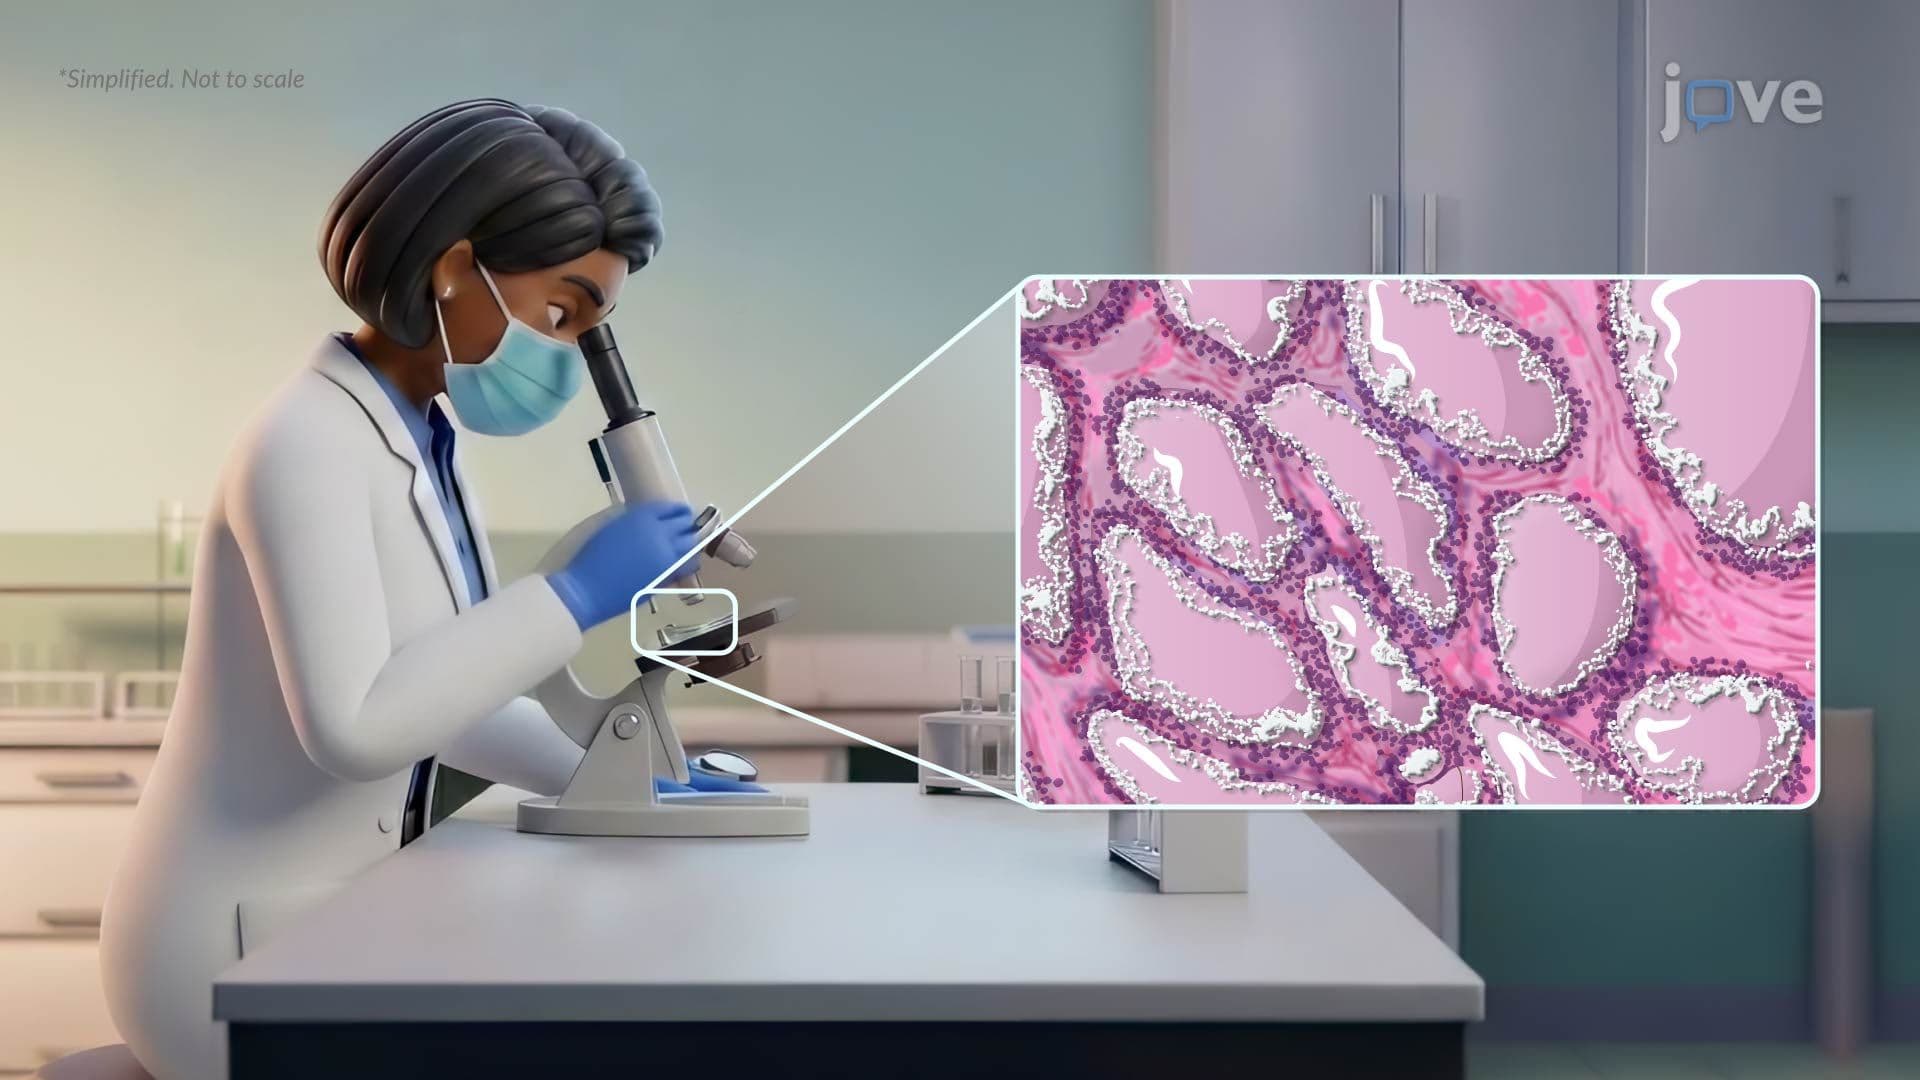
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:28
Graves' Disease I: Introduction