Related Experiment Video
Updated: Aug 19, 2026

A Model for Perineural Invasion in Head and Neck Squamous Cell Carcinoma
Published on: January 5, 2017

Insights
Healthcare spending in 1984 neared $400 billion, prompting changes in medical care financing. Greater savings are achievable by restructuring the healthcare environment, not just hospital payment systems.
Area of Science:
- Health Economics
- Healthcare Policy
- Medical Services Financing
Background:
- In 1984, US healthcare spending reached nearly $400 billion, with double-digit annual increases necessitating changes in financing.
- The Tax Equity and Fiscal Responsibility Act introduced prospective payment for hospitals, impacting healthcare economics.
- Despite improvements, 1984 saw a 9.1% rise in total healthcare spending and a 6.2% increase in medical prices.
Purpose of the Study:
- To evaluate the impact of the Tax Equity and Fiscal Responsibility Act on healthcare financing.
- To propose alternative strategies for achieving greater cost savings in the healthcare sector.
- To argue for a broader restructuring of the healthcare environment beyond hospital payment mechanisms.
Main Methods:
- Analysis of healthcare spending data from 1984.
- Review of the effects of the Tax Equity and Fiscal Responsibility Act.
- Comparative analysis of cost-saving strategies in healthcare.
Main Results:
- Healthcare spending and medical price inflation showed improvements compared to prior years.
- The prospective payment system marked a significant shift in hospital financing.
- The study suggests current reforms are insufficient for realizing maximal cost savings.
Conclusions:
- While hospital payment reforms offer some savings, they are not the sole solution for controlling healthcare costs.
- Significant financial benefits can be achieved by addressing broader systemic issues within the healthcare environment.
- A comprehensive restructuring of healthcare elements is recommended for substantial and sustainable cost reductions.
Abstract:
With almost a $400 billion price tag for medical services rendered in 1984 and annual spending levels increasing at double-digit rates, changes in the financing mechanism for medical care services were unavoidable. The passage of the Tax Equity and Fiscal Responsibility Act ushered in an era of prospective payment for hospitals, and in 1984 total healthcare spending in the United States increased by 9.1%. The medical price component of the consumer price index rose 6.2%. Although these annual increases are improvements over previous years' data, the author's contention is that significant and greater savings can be realized by restructuring several elements of the healthcare environment rather than concentrating efforts solely on reshaping the payment mechanism for the hospital industry.
More Related Videos

Related Concept Videos
 01:15
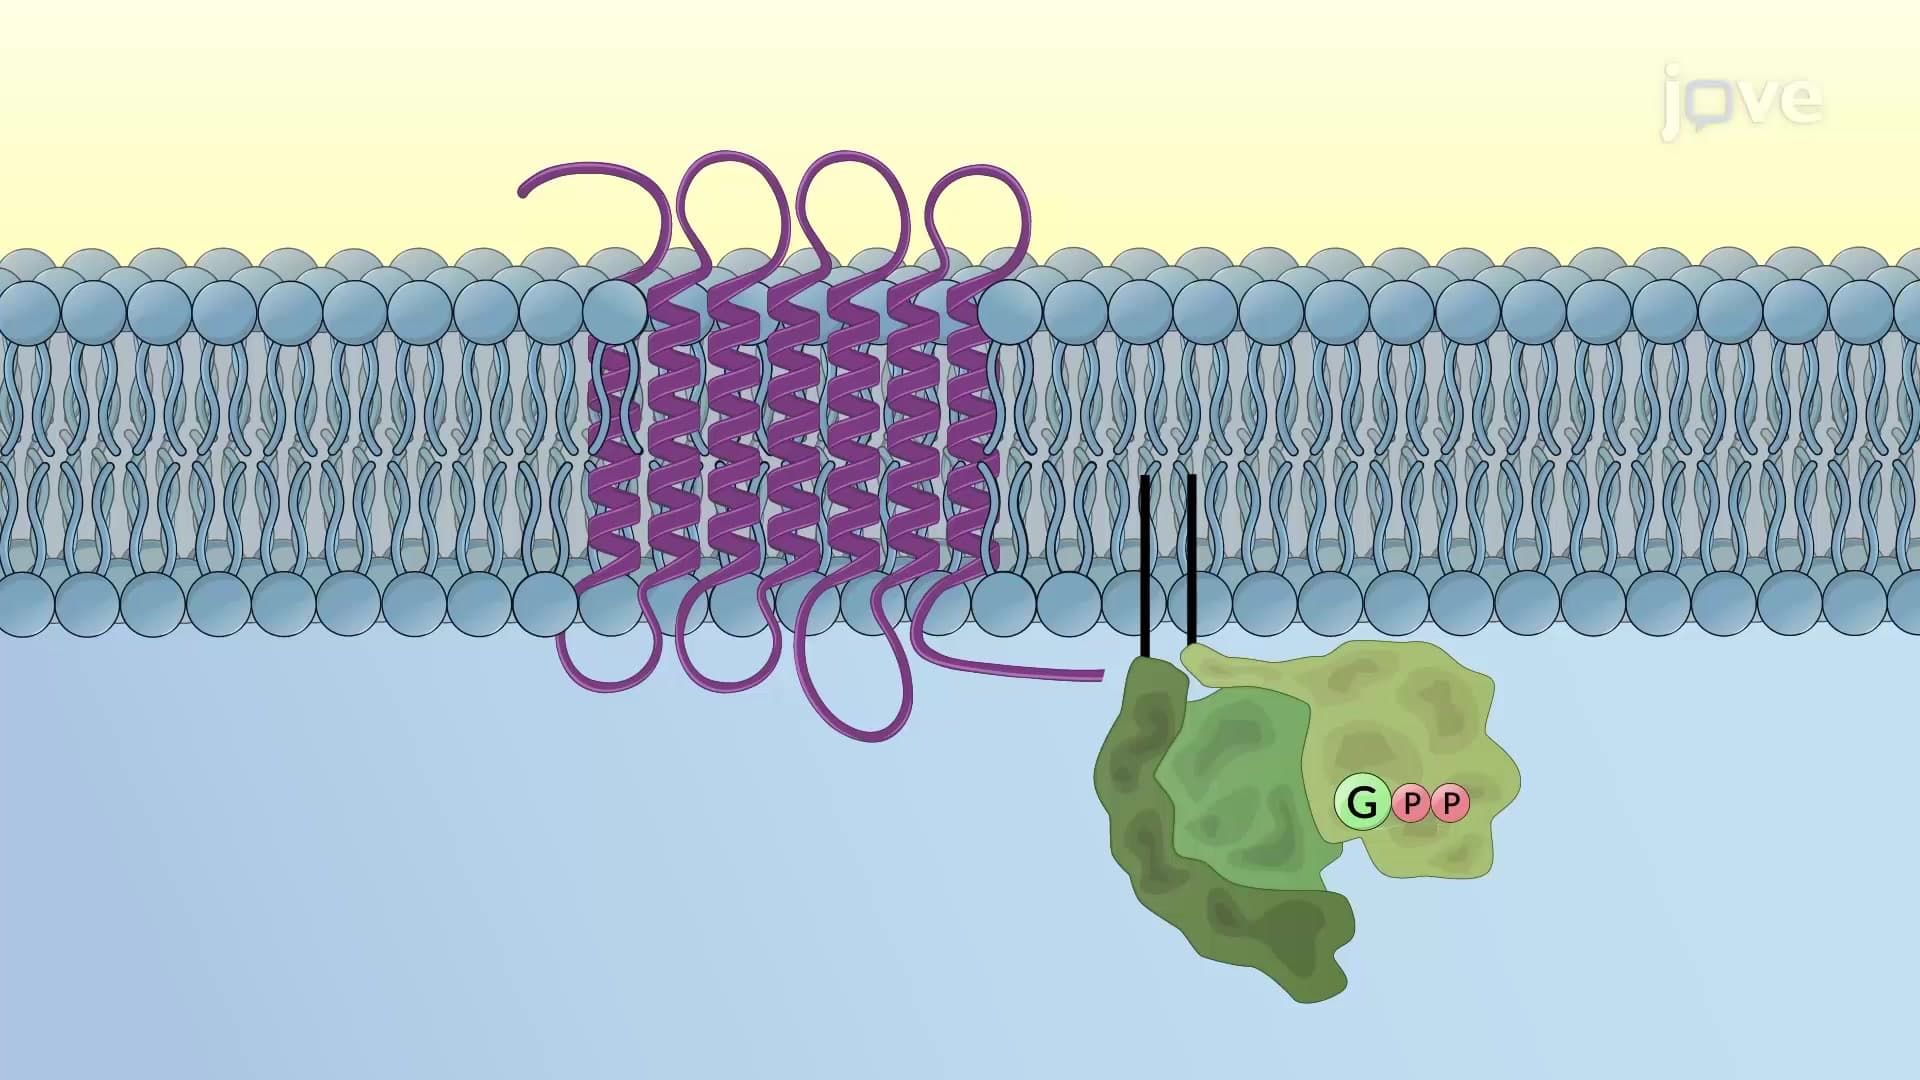
G Protein-coupled Receptors
GPCRs are also called heptahelical, 7TM, or serpentine receptors, and consist of seven (H1-H7) transmembrane alpha-helices that span the bilayer to form a cylindrical core. The transmembrane helices are connected by three extracellular loops and three...
 01:28
Dosage Regimens: Designs and Approaches
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:03
Pharmacodynamic Responses: Different Types