ATX II, a sodium channel toxin, sensitizes skeletal muscle to halothane, caffeine, and ryanodine
Related Experiment Video
Updated: Oct 22, 2026

In vitro Measurements of Tracheal Constriction Using Mice
Published on: June 25, 2012
J E Fletcher1, P J Adnet, H Reyford
1Trinity Communications, Conshohocken, Pennsylvania 19428-2977, USA. jfletcher@trinitycom.com

Background:
The function or expression of subtypes of the sodium ion (Na+) channel is altered in biopsies or cultures of skeletal muscle from many persons who are susceptible to malignant hyperthermia (MH). ATX II, a specific Na+ channel toxin from a sea anemone, causes delayed inactivation of the channel similar to that seen in cell cultures of MH muscle. ATX II was added to skeletal muscle to determine whether altered Na+ channel function could increase the sensitivity of normal skeletal muscle to agents (halothane, caffeine, ryanodine) to which MH muscle is hypersensitive.
Methods:
Studies were performed of fiber bundles from the vastus lateralis muscle of persons who were deemed not MH susceptible (MH-) or MH susceptible (MH+) according to the MH diagnostic test and of strips of diaphragm muscle from rats. Preparations in a tissue bath containing Krebs solution were connected to a force transducer. ATX II was introduced 5 min before halothane, caffeine, or ryanodine.
Results:
ATX II increased the magnitude of contracture to halothane in preparations from most MH-, but not MH+, human participants. After ATX II treatment, preparations from 9 of 24 MH- participants generated contractures to halothane, 3%, that were of the same magnitude as those from MH+ participants. Preparations from four of six ATX II-treated healthy participants also gave responses of the same magnitude as those of MH-susceptible participants to a graded halothane challenge (0.5-3%). The contractures to bolus doses of halothane in specimens from male participants were more than three times larger than the contractures in specimens from female participants. In rat muscle, ATX II increased the magnitude of contracture to caffeine (2 mM) and decreased the time to produce a 1-g contracture to ryanodine (1 microM).
Conclusions:
ATX II, which causes delayed inactivation of the Na+ channel in cell cultures similar to that reported in cultures of MH+ skeletal muscle, increased the sensitivity of normal muscle to three agents to which MH+ muscle is hypersensitive. The increased sensitivity to halothane, 3%, occurred in most (79%), but not all, MH- participants, and this effect was most evident in male participants. Therefore, abnormal function of the Na+ channel, even if it is a secondary event in MH, may contribute to a positive contracture test result for MH.
Insights
Altering sodium ion (Na+) channel function with ATX II toxin increased normal muscle sensitivity to malignant hyperthermia (MH) triggering agents. This suggests abnormal Na+ channel function may contribute to MH susceptibility, particularly in males.
Area of Science:
- Physiology
- Pharmacology
- Genetics
Background:
- Altered sodium ion (Na+) channel function is observed in skeletal muscle of individuals susceptible to malignant hyperthermia (MH).
- ATX II toxin induces delayed Na+ channel inactivation, mimicking changes seen in MH muscle cultures.
- Investigating ATX II's effect on normal muscle assesses if Na+ channel dysfunction increases sensitivity to MH-associated agents.
Purpose of the Study:
- To determine if modifying normal skeletal muscle Na+ channel function with ATX II enhances sensitivity to halothane, caffeine, and ryanodine.
- To compare the response of ATX II-treated normal muscle to that of MH-susceptible muscle.
Main Methods:
- Fiber bundles from human vastus lateralis (MH- and MH+ susceptible) and rat diaphragm muscle were used.
- Muscle preparations were exposed to ATX II followed by halothane, caffeine, or ryanodine in a tissue bath.
- Contracture force was measured using a force transducer.
Main Results:
- ATX II increased halothane-induced contractures in most MH- individuals, mimicking MH+ responses.
- Significant halothane sensitivity was observed in ATX II-treated normal muscle, particularly in male participants.
- In rat muscle, ATX II potentiated caffeine contractures and accelerated ryanodine-induced contractures.
Conclusions:
- ATX II enhances normal skeletal muscle sensitivity to MH-associated agents, suggesting a role for Na+ channel dysfunction.
- Abnormal Na+ channel function, even if secondary, may contribute to positive results in MH diagnostic tests.
- The findings highlight the potential impact of Na+ channel abnormalities on MH susceptibility and diagnosis.
More Related Videos
 10:45
Levator Auris Longus Preparation for Examination of Mammalian Neuromuscular Transmission Under Voltage Clamp Conditions
Published on: May 5, 2018
 09:39
Establishing a Mouse Model of a Pure Small Fiber Neuropathy with the Ultrapotent Agonist of Transient Receptor Potential Vanilloid Type 1
Published on: February 13, 2018
Related Concept Videos
 01:26
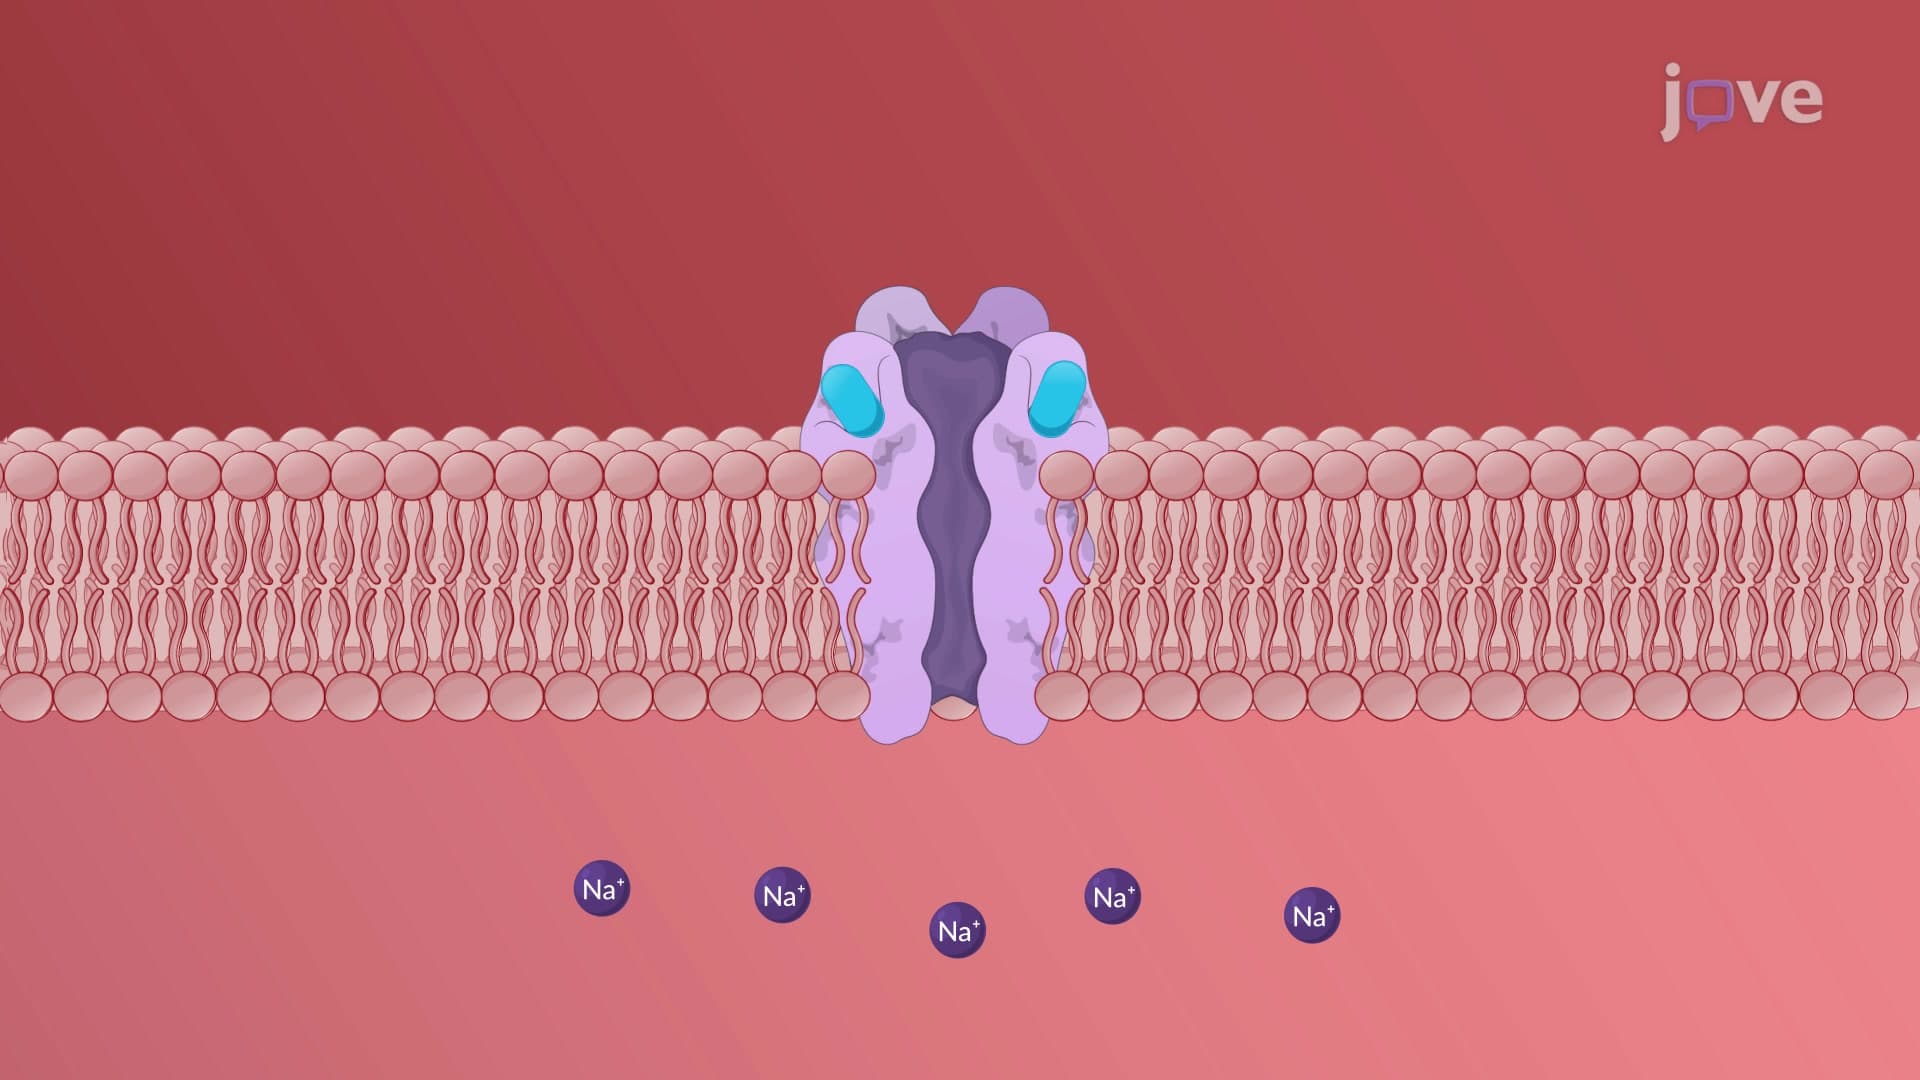
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:17
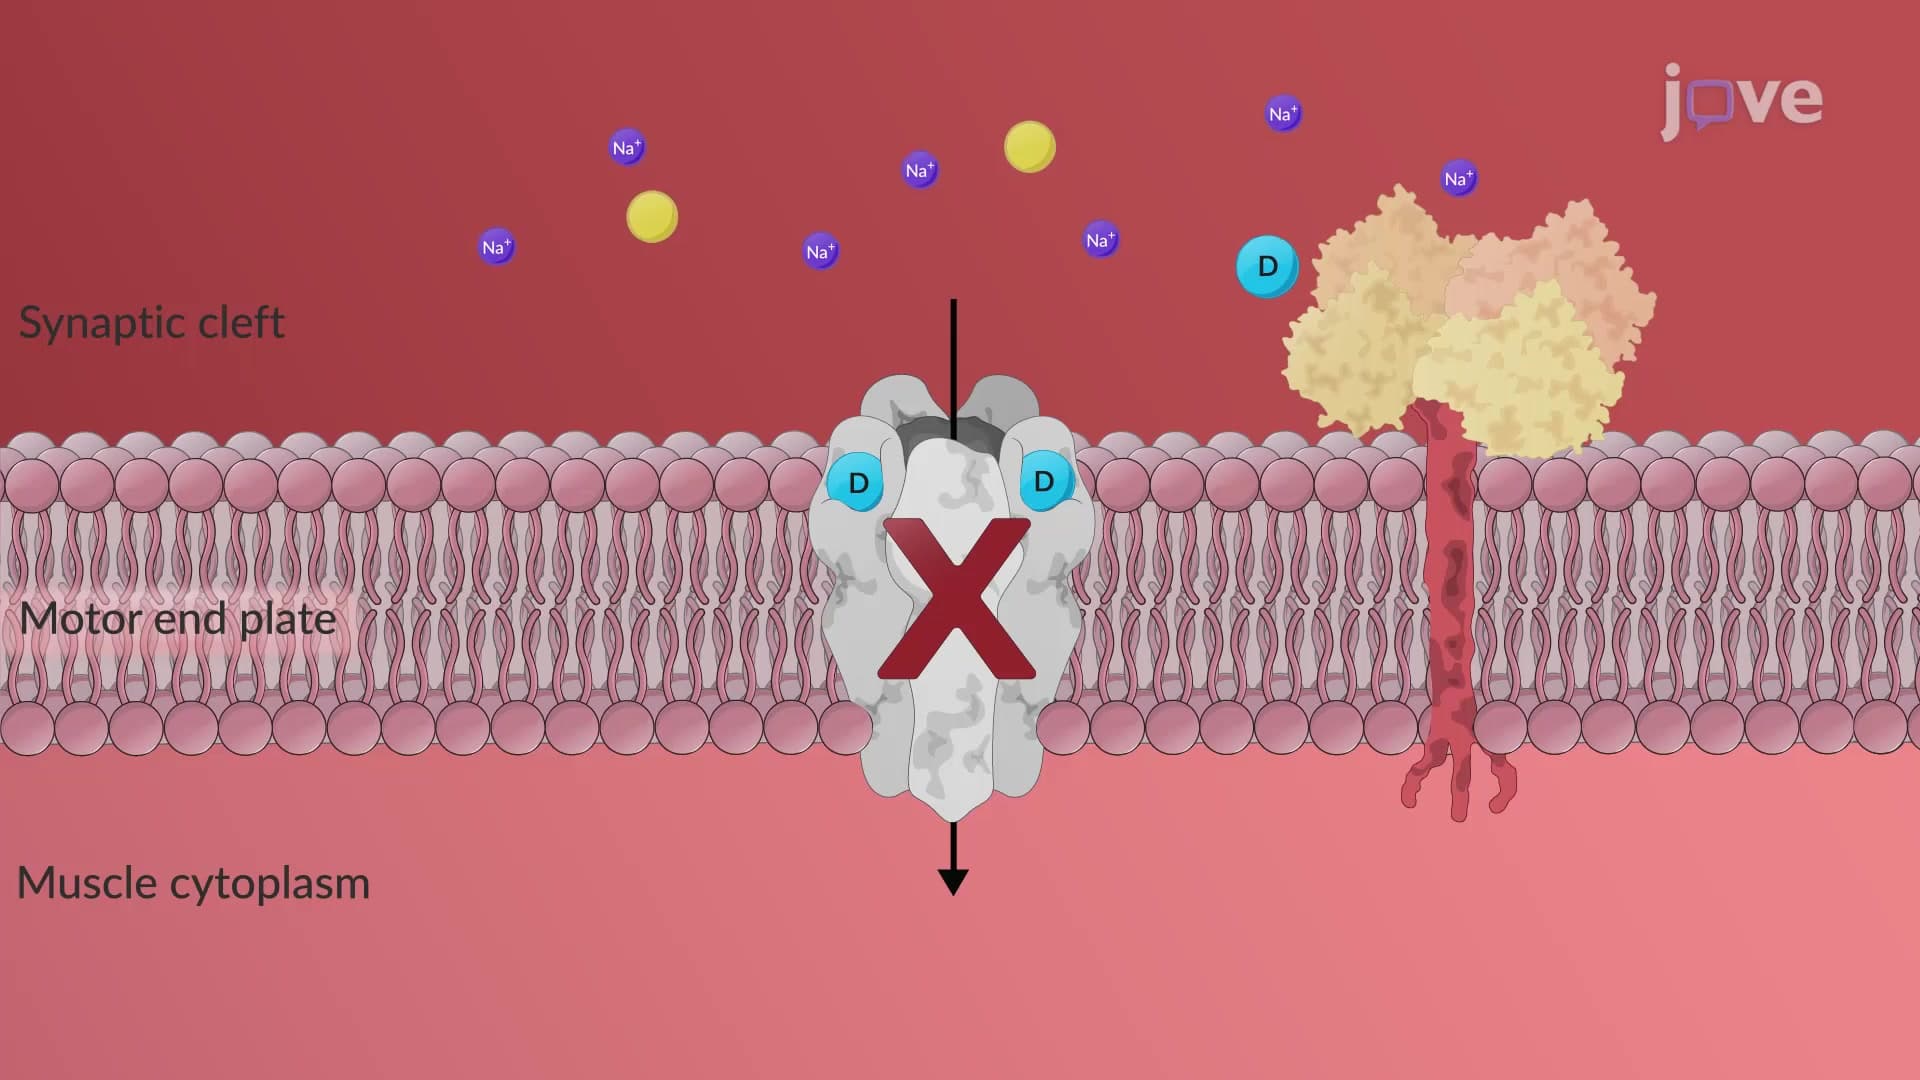
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:29
Tetanus
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...