Related Experiment Video
Updated: Oct 22, 2026

Behavioral Approaches to Studying Innate Stress in Zebrafish
Published on: May 1, 2019
Clinical pharmacokinetics and pharmacodynamics of buspirone, an anxiolytic drug
1Division of Pharmaceutical Evaluation I, Food and Drug Administration, Rockville, Maryland, USA. Mahmoodi@CDER.FDA.GOV

Abstract:
Buspirone is an anxiolytic drug given at a dosage of 15 mg/day. The mechanism of action of the drug is not well characterised, but it may exert its effect by acting on the dopaminergic system in the central nervous system or by binding to serotonin (5-hydroxytryptamine) receptors. Following a oral dose of buspirone 20 mg, the drug is rapidly absorbed. The mean peak plasma concentration (Cmax) is approximately 2.5 micrograms/L, and the time to reach the peak is under 1 hour. The absolute bioavailability of buspirone is approximately 4%. Buspirone is extensively metabolised. One of the major metabolites of buspirone is 1-pyrimidinylpiperazine (1-PP), which may contribute to the pharmacological activity of buspirone. Buspirone has a volume of distribution of 5.3 L/kg, a systemic clearance of about 1.7 L/h/kg, an elimination half-life of about 2.5 hours and the pharmacokinetics are linear over the dose range 10 to 40 mg. After multiple-dose administration of buspirone 10 mg/day for 9 days, there was no accumulation of either parent compound or metabolite (1-PP). Administration with food increased the Cmax and area under the plasma concentration-time curve (AUC) of buspirone 2-fold. After a single 20 mg dose, the Cmax and AUC increased 2-fold in patients with renal impairment as compared with healthy volunteers. The Cmax and AUC were 15-fold higher for the same dose in patients with hepatic impairment compared with healthy individuals. The half-life of buspirone in patients with hepatic impairment was twice that in healthy individuals. The pharmacokinetics of buspirone were not affected by age or gender. Coadministration of buspirone with verapamil, diltiazem, erythromycin and itraconazole substantially increased the plasma concentration of buspirone, whereas cimetidine and alprazolam had negligible effects. Rifampicin (rifampin) decreased the plasma concentrations of buspirone almost 10-fold.
Related Concept Videos
 01:29
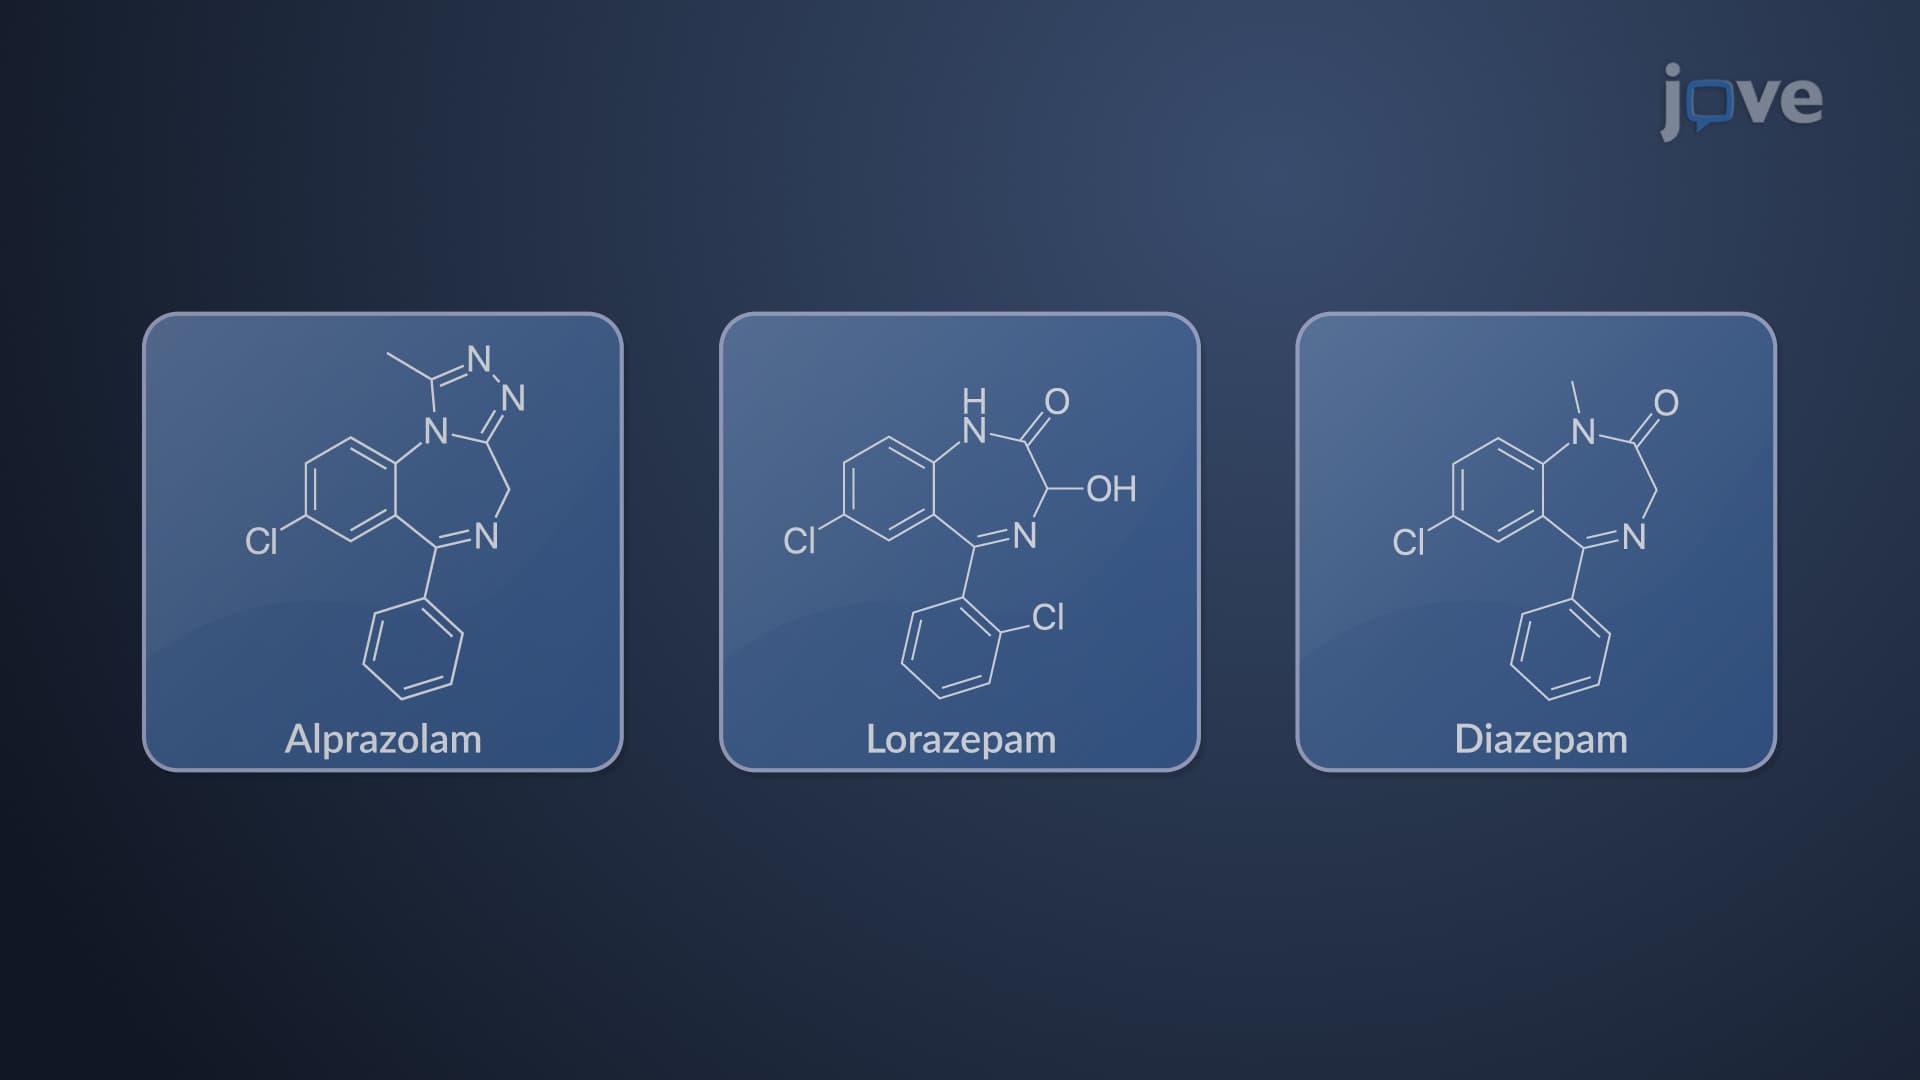
Anxiolytic Drugs: Benzodiazepines and Buspirone
 01:26
Anxiolytic Drugs: Overview
Primary Types of Anxiolytic Drugs
1. Benzodiazepines:
Benzodiazepines bind to the GABA-A receptor in the brain, enhancing GABA's interaction. This action reduces neurotransmission, effectively blocking anxiety-associated limbic circuitry.
 01:23
Nonlinear Pharmacokinetics: Dependence of Elimination Half-Life and Dose Clearance
A study on guinea pigs examined the...
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:17
Sedatives and Hypnotics Drugs: Miscellaneous Agents
Melatonin congeners like ramelteon (Rozerem) and tasimelteon (Hetlioz) selectively bind to melatonin receptors (MT1 and MT2) and thus mimic the actions of melatonin, a hormone that regulates sleep-wake cycles. Tasimelteon is primarily used for non-24-hour sleep-wake disorder, common in blind patients. They are also used to treat conditions like insomnia...