Related Experiment Video
Updated: Aug 3, 2026
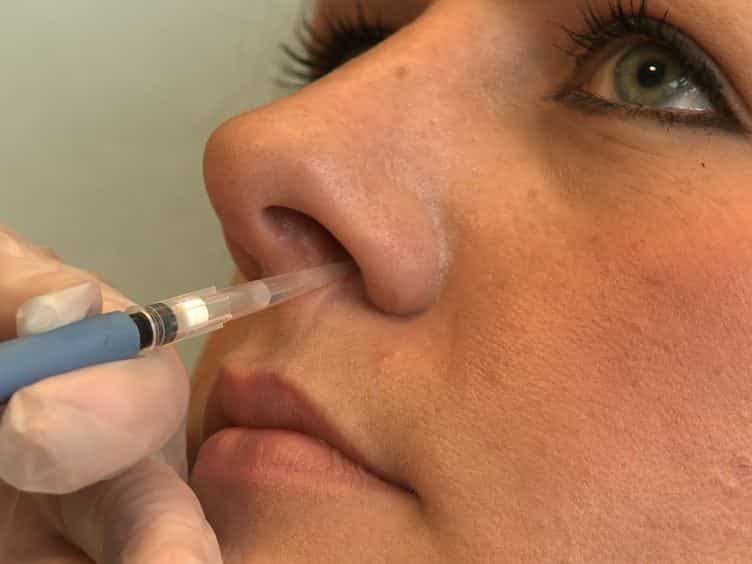
Experimental Human Pneumococcal Carriage
Published on: February 15, 2013

Insights
A new pneumococcal vaccine shows 100% efficacy against the deadliest forms of pneumococcal disease, bacterial meningitis and bacteremia. This breakthrough offers significant protection for infants and young children against severe pneumococcus infections.
Area of Science:
- Bacteriology
- Vaccinology
- Pediatric Infectious Diseases
Background:
- Pneumococcal diseases, caused by Streptococcus pneumoniae, lead to millions of doctor visits and over a million deaths globally each year.
- Pneumonia and otitis media are common manifestations, with children under five accounting for a significant proportion of fatalities.
- Bacterial meningitis and bacteremia represent the most lethal pneumococcal infections.
Purpose of the Study:
- To evaluate the efficacy of a novel pneumococcal vaccine in preventing severe pneumococcal diseases.
- To assess the vaccine's impact on bacterial meningitis and bacteremia in infants.
Main Methods:
- A three-year, Phase III clinical trial was conducted involving 38,000 infants.
- Participants were randomized to receive either the new pneumococcal vaccine or a placebo.
- Efficacy rates against specific pneumococcal afflictions were meticulously recorded.
Main Results:
- The new pneumococcal vaccine demonstrated a 100% efficacy rate against bacterial meningitis.
- The vaccine also achieved 100% efficacy against bacteremia, the two most deadly pneumococcal conditions.
- The trial involved a large cohort, ensuring robust statistical power.
Conclusions:
- The novel pneumococcal vaccine is highly effective in preventing the most severe outcomes of Streptococcus pneumoniae infection.
- This vaccine represents a significant advancement in pediatric infectious disease prevention.
- Widespread vaccination could dramatically reduce pneumococcal disease mortality, especially in young children.
Abstract:
Pneumococcal diseases, caused by the bacterium Streptococcus pneumoniae, include pneumonia and otitis media, which accounts for some 12 million doctor visits per year in the United States alone. Each year around the world, pneumococcus causes 1.2 million deaths due to pneumonia, 39% of which are in children under the age of five. In a three-year Phase III clinical trial involving 38,000 children, in which half of the infants received a new pneumococcal vaccine and half received a placebo vaccine, the new vaccine demonstrated an efficacy rate of 100% against bacterial meningitis and bacteremia, the two most deadly pneumococcal afflictions.

Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:14
Atypical Pneumonia
 01:25
Clinical Significance of Antibiotic Resistance
 01:29
Pneumonia I: Introduction