Related Experiment Video
Updated: Oct 1, 2026
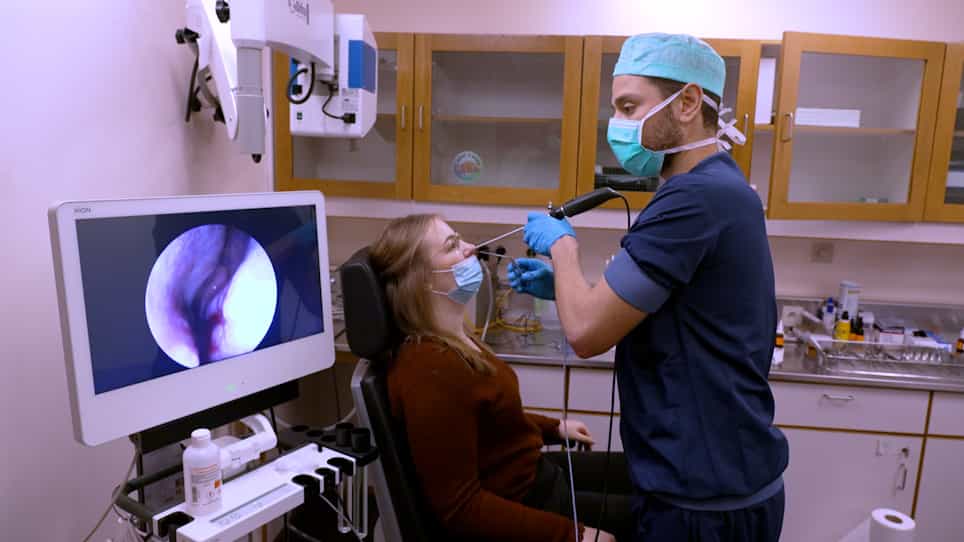
Nasal Brushing Sampling and Processing Using Digital High Speed Ciliary Videomicroscopy – Adaptation for the COVID-19 Pandemic
Published on: November 7, 2020
Current concepts in the management of paediatric rhinosinusitis
1Department of Otorhinolaryngology, Head and Neck Surgery, University Hospital Nottingham, UK.

Insights
Pediatric rhinosinusitis, often caused by adenoid hypertrophy and allergic rhinitis, typically resolves with conservative treatments. Watchful waiting and non-invasive methods are recommended over surgery for most children.
Area of Science:
- Pediatrics
- Otolaryngology
- Immunology
Background:
- Adenoid hypertrophy and allergic rhinitis are common in children, leading to symptoms of rhinosinusitis such as rhinorrhoea and nasal obstruction.
- Recurrent upper respiratory tract infections are frequent in childhood, often associated with these conditions.
Purpose of the Study:
- To emphasize conservative management strategies for pediatric rhinosinusitis.
- To advocate for non-invasive treatments and watchful waiting before considering surgical interventions.
Main Methods:
- Review of common pediatric upper respiratory conditions and their management.
- Emphasis on non-invasive measures like saline sprays, allergen avoidance, and topical anti-inflammatory nasal sprays.
- Discussion of the natural resolution of symptoms with age and immune system maturation.
Main Results:
- Most children outgrow adenoid hypertrophy and recurrent infections by age eight to 10.
- Conservative treatments and watchful waiting are effective for the majority of pediatric rhinosinusitis cases.
- Antibiotics often provide only short-term relief for chronic nasal discharge.
Conclusions:
- Pediatric rhinosinusitis is generally not a surgical condition, with conservative management being the primary approach.
- Safe, non-invasive methods and observation are recommended, as the condition typically resolves with time and immune development.
- Exceptions requiring further investigation include nasal polyps and periorbital cellulitis.
Abstract:
It is well recognized that adenoid hypertrophy and allergic rhinitis are common in children and that recurrent upper respiratory tract infections are a fact of life. The main causes of symptoms associated with rhinosinusitis in children are rhinorrhoea, nasal obstruction, mouth breathing, hyponasal speech and snoring. Most children grow out of adenoid hypertrophy and recurrent colds by the age of eight to 10 and this means that the main treatment strategy should therefore be conservative and not surgical. An explanation to anxious parents, simple non-invasive measures such as teaching nose-blowing, the use of saline sprays or a trial of allergen avoidance and age-appropriate topical nasal anti-inflammatory sprays should be tried before surgery is even contemplated. Because repeated infections are so common, antibiotics given for chronic nasal discharge often have only short-lived effects. Rhinosinusitis in children is not a surgical disease and 'watchful waiting' is advised. Any treatment should first of all be safe, as even without any intervention the problem usually resolves with time. It is likely that growth and maturation of the immunological response to pathogens play a major role in resolution of the disease. There are few exceptions to this principle: nasal polyps (indicating possible cystic fibrosis), and periorbital cellulitis where an assessment of vision, parenteral antibiotics, and if there is concern about the possibility of a subperiosteal abscess, computerized tomography (CT) and drainage of any pus is indicated.


Related Concept Videos
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:26
Tonsillitis II: Management
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:29
Microbiota of the Respiratory Tract