Glenohumeral motion after complete capsular release
Related Experiment Video
Updated: Oct 20, 2026

Rat Model of Adhesive Capsulitis of the Shoulder
Published on: September 28, 2018
M J Moskal1, D T Harryman, A A Romeo
1Department of Orthopaedics, The University of Washington School of Medicine, Seattle 98195-6500, USA.

Abstract:
The range of glenohumeral motion is primarily limited by the joint capsule. If the capsule is contracted, greater restriction in glenohumeral motion is exhibited. Release of a tight capsule has been an effective means of managing refractory stiffness of the glenohumeral joint. The effect of a complete capsular release on glenohumeral kinematics has not been previously studied in a cadaver model. Elevation, rotation, and translation of eight cadaveric glenohumeral preparations were studied before and after complete capsular release. As the intact joint was positioned near the limits of motion, glenohumeral torque rose rapidly with relatively small concomitant increases in elevation and rotational angles. Notable torque, due to tension in the capsule or cuff, ensued only after glenohumeral elevation reached approximately 80% of maximal range. After complete capsular release, maximal elevation increased on average 15%, yet retained definitive endpoints due to residual tension in the rotator cuff. Axial humeral rotation with an intact capsule decreased as maximum elevation approached, especially at elevation angles greater than 60 degrees. Maximum internal rotation was less than external, for all planes except +90 degrees. After complete capsular release, the greatest net gains for external rotation tended to be in the posterior scapular planes, whereas gains for internal rotation tended to be in the anterior scapular planes. Maximal translation in an intact vented capsule was 21 mm, 14 mm, and 15 mm in the anterior, posterior, and inferior directions, respectively. After complete capsular release, translation increased in all positions with maximal anterior, posterior, and inferior translations of 28 mm, 25 mm, and 28 mm, respectively. In general, relative gains in translation were greater in planes posterior to the scapula and at extremes of the range of motion. Although large glenohumeral translations were measured, no preparation could be dislocated before or after complete capsular release. Complete capsular release significantly increased glenohumeral range of motion and translation. The intact rotator cuff myotendinous units serves to limit the range of motion and translation after all capsuloligamentous attachments are rendered incompetent by complete capsular release.

Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:19
Bones of the Upper Limb: Humerus
 01:26
Joints
Structural joint classifications are based on the material that makes up the joint as well as whether or not the joint contains a space between the bones. Joints are structurally classified as fibrous, cartilaginous, or synovial.
Fibrous Joints Are Immovable
The bones of a...
 00:51
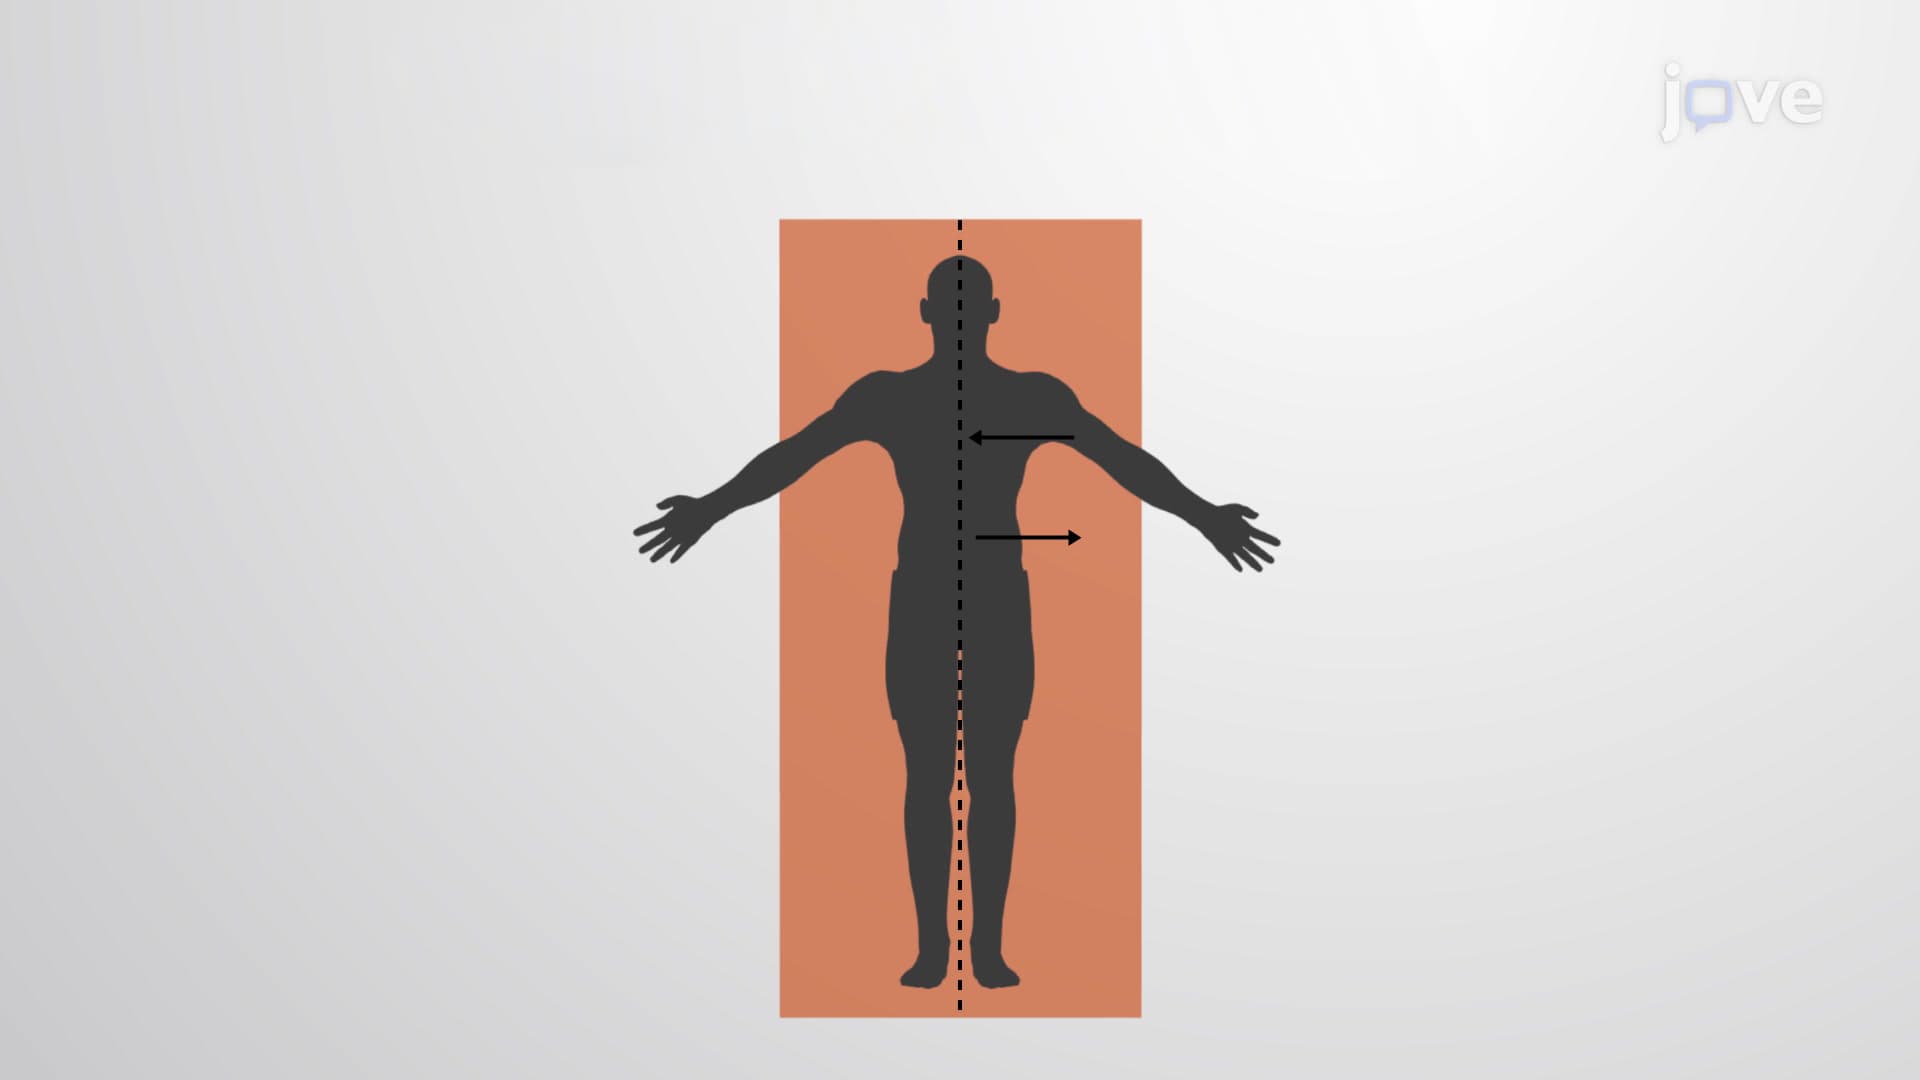
Anatomical Movements
Here are some common anatomical movements:
Flexion and extension motions are in the sagittal (anterior–posterior) plane of motion. These movements take place at the shoulder, hip, elbow, knee, wrist, metacarpophalangeal,...