Oral anticoagulation in nonvalvular atrial fibrillation
Related Experiment Video
Updated: Oct 20, 2026

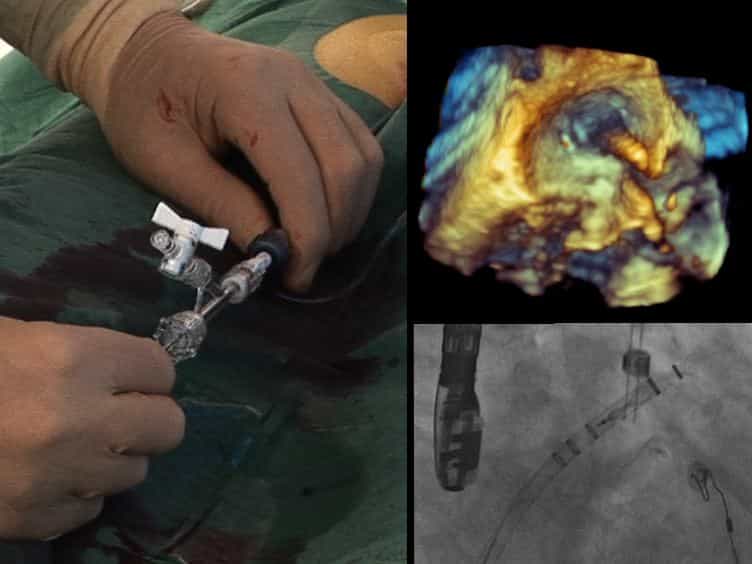
The WATCHMAN Left Atrial Appendage Closure Device for Atrial Fibrillation
Published on: February 28, 2012
1National Board of Health, Copenhagen, Denmark. bgk@sst.dk

Insights
For patients with atrial fibrillation, low-intensity warfarin alone or with aspirin is ineffective for preventing stroke. Optimal warfarin intensity (INR 2.0-3.0) is recommended for high-risk individuals, while aspirin may suffice for younger, low-risk patients.
Area of Science:
- Cardiology
- Neurology
- Pharmacology
Background:
- Chronic nonvalvular atrial fibrillation increases thromboembolic risk (4.5% annually).
- Risk factors include age, prior stroke, diabetes, hypertension, and left ventricular dysfunction.
- Warfarin effectively prevents stroke (68% risk reduction), but aspirin's efficacy is debated (18-44% reduction).
Purpose of the Study:
- To evaluate the effectiveness of low-intensity warfarin, alone or combined with aspirin, for stroke prevention in atrial fibrillation.
- To confirm optimal anticoagulation intensity for thromboembolic event prevention.
Main Methods:
- Review of placebo-controlled trials and clinical trials investigating warfarin and aspirin therapies.
- Analysis of SPAF III study results.
- Assessment of oral anticoagulation intensity (INR values).
Main Results:
- Mini-intensity warfarin plus aspirin was insufficient for stroke prevention in atrial fibrillation.
- Oral anticoagulation below INR 2.0 is ineffective for preventing thromboembolic events.
- Current recommendations favor warfarin at INR 2.0-3.0 for high-risk patients.
Conclusions:
- Low-intensity warfarin regimens are inadequate for stroke prevention in atrial fibrillation.
- Achieving specific INR targets with warfarin is crucial for effective thromboembolic event prevention.
- Aspirin may be suitable for younger patients (<65 years) without additional risk factors.
Abstract:
Chronic nonvalvular atrial fibrillation is associated with an overall risk of thromboembolic complications of 4.5% per year. Advancing age, prior stroke or transient cerebral ischaemia, diabetes, hypertension, and impaired function of the left ventricle are known risk factors. Placebo-controlled trials have demonstrated that oral anticoagulant therapy with warfarin is effective for primary and secondary prevention of ischaemic stroke, reducing the risk by 68%. The effect of aspirin is still controversial, reducing the risk by 18-44%. Recent clinical trials have investigated the effect of warfarin given at a very low intensity alone or combined with aspirin. The results from the SPAF III study demonstrated that a combination of mini-intensity warfarin plus aspirin was insufficient for stroke prevention in atrial fibrillation. More trials have now confirmed that oral anticoagulation at INR-values below 2.0 is not effective for prevention of thromboembolic events in these patients. It is currently recommended that patients at a high risk of stroke are treated with warfarin at an intensity of INR 2.0-3.0. Patients younger than 65 years without other risk factors can be given aspirin 325 mg day-1.
Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers