Related Experiment Video
Updated: Oct 20, 2026

Culturing and Measuring Fetal and Newborn Murine Long Bones
Published on: April 26, 2019
Achondroplasia-hypochondroplasia complex in a newborn infant
M J Huggins1, J R Smith, K Chun
1Department of Laboratory Medicine, Hamilton Health Sciences Corporation, Ontario, Canada. hugginsm@exchange1.cmh.on.ca

Insights
This case study details an 8-month-old girl with achondroplasia-hypochondroplasia complex, a rare genetic disorder. Molecular testing confirmed compound heterozygous mutations in the fibroblast growth factor receptor 3 (FGFR3) gene.
Area of Science:
- Genetics
- Pediatrics
- Skeletal Dysplasias
Background:
- Achondroplasia and hypochondroplasia are skeletal dysplasias caused by mutations in the fibroblast growth factor receptor 3 (FGFR3) gene.
- Genetic counseling and molecular testing are crucial for diagnosing skeletal dysplasias during pregnancy.
- This report focuses on a rare complex form of skeletal dysplasia.
Observation:
- Antenatal ultrasonography revealed severe fetal anomalies including short limbs, macrocephaly, and a small chest.
- The patient presented with rhizomelic limb shortening, large head, small chest, and mild lung hypoplasia postnatally.
- Clinical examination at 8 months showed disproportionate limb shortening, frontal bossing, depressed nasal bridge, and motor development delay.
Findings:
- Molecular testing confirmed compound heterozygous mutations in FGFR3: G1138A (achondroplasia) and C1620G (hypochondroplasia).
- Radiographs demonstrated characteristic features of achondroplasia, including shortened long bones and metaphyseal flaring.
- The patient exhibits features consistent with achondroplasia-hypochondroplasia complex, a condition with limited prior documentation.
Implications:
- This case highlights the importance of genetic testing for FGFR3 mutations in suspected skeletal dysplasias.
- Understanding the genetic basis of achondroplasia-hypochondroplasia complex can aid in prenatal diagnosis and management.
- Further research is needed to elucidate the long-term prognosis and management strategies for this rare condition.
Abstract:
We describe the case of an 8-month-old girl with achondroplasia-hypochondroplasia complex. The diagnosis was suggested antenatally when obstetrical ultrasonography at 27 weeks of gestation showed short limbs, small chest, and macrocephaly. The father has achondroplasia due to the common G1138A (G380R) mutation in the fibroblast growth factor receptor 3 (FGFR3) gene, while the mother has hypochondroplasia due to the C1620G (N450K) mutation in the FGFR3 gene. Neither had had genetic counseling or molecular testing prior to the pregnancy. Antenatal ultrasound study at 29 weeks of gestation showed a large head, very short limbs, and a small chest; the findings were more severe than in achondroplasia or hypochondroplasia alone. The patient was born by cesarean section at 37 weeks of gestation and had rhizomelic shortness of limbs with excess skin creases, large head, and small chest, diagnostic of achondroplasia. Radiographs showed shortness of the long bones and flaring of the metaphyses. She had mild hypoplasia of lungs. Molecular testing showed both the G1138A and the C1620G mutations in FGFR3, confirming the diagnosis of achondroplasia-hypochondroplasia complex. At 8 months, she has disproportionate shortness of the long bones and a large head with frontal bossing and a depressed nasal bridge. Her chest remains small, and she is on home oxygen at times of respiratory stress. She has a large gibbus. She is delayed in her motor development and has significant head lag. To our knowledge, there is only one previously published report of achondroplasia-hypochondroplasia complex.
Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
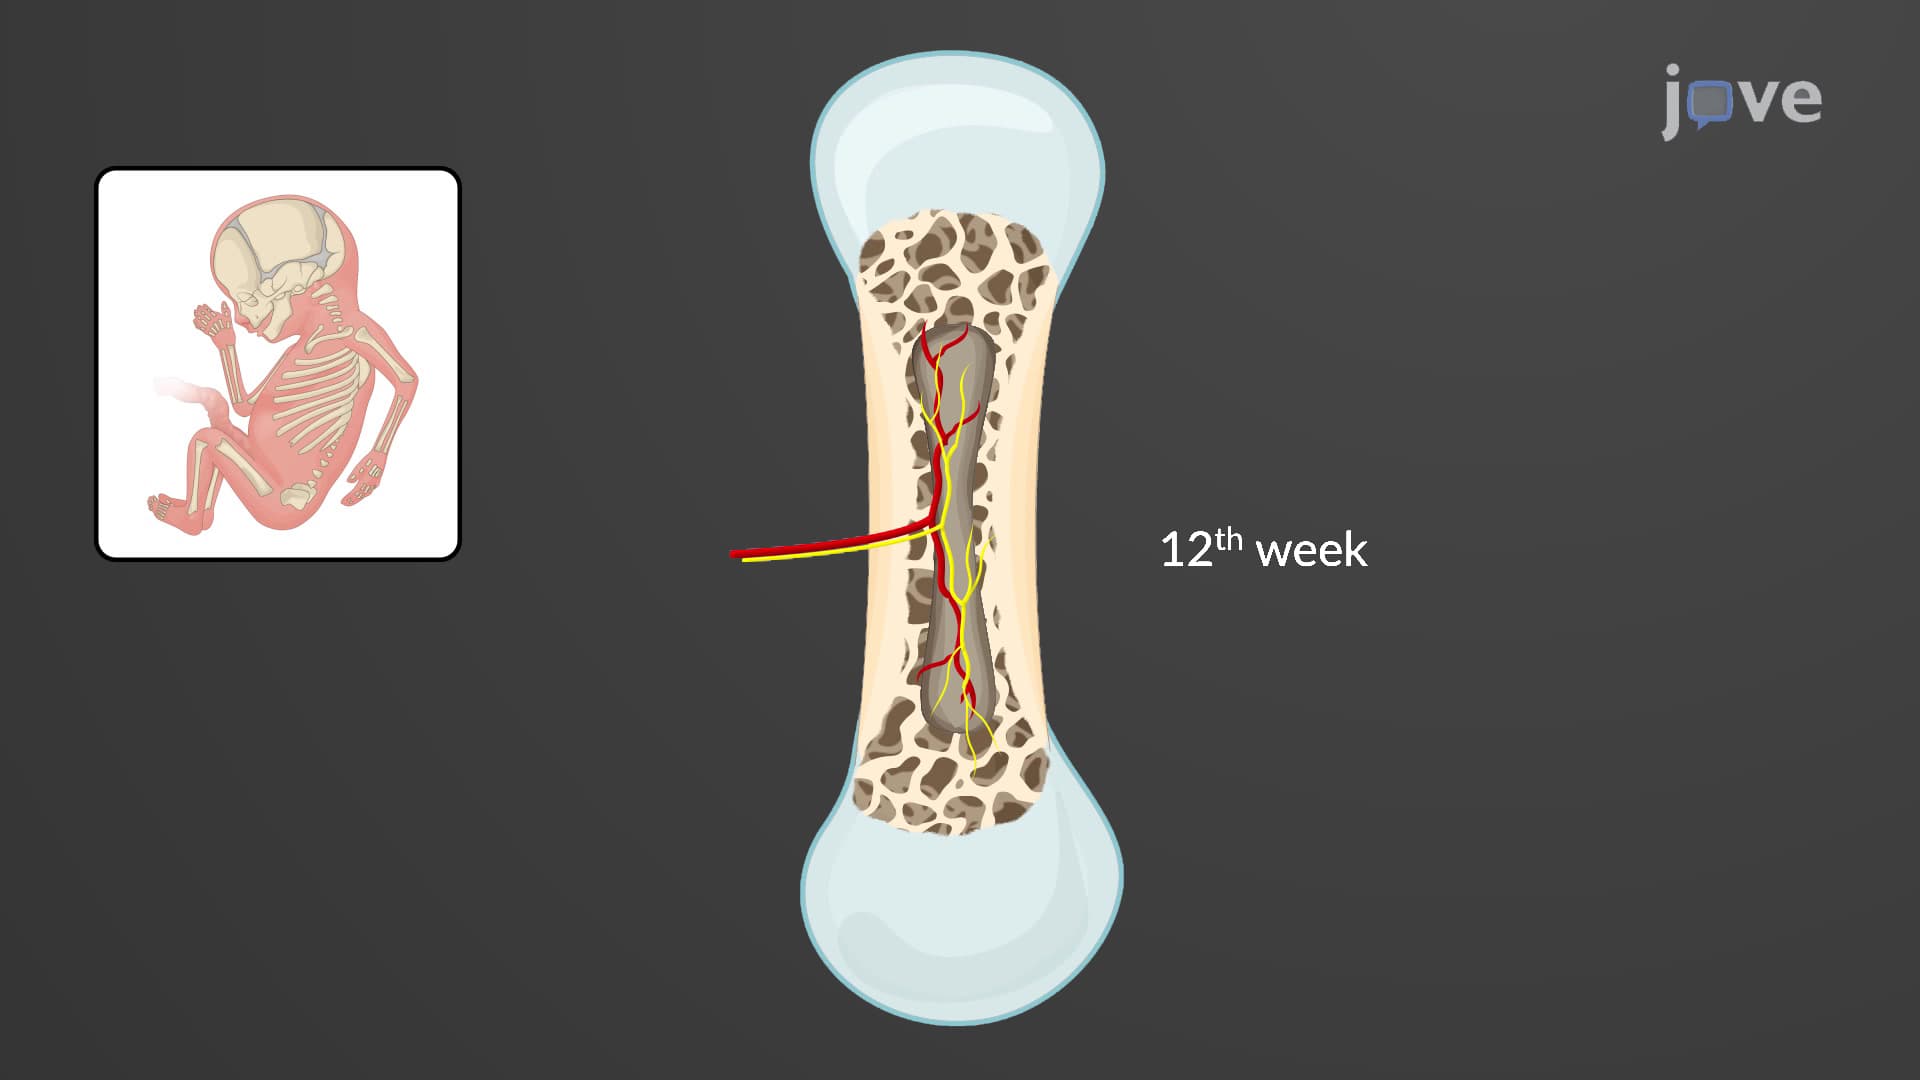
Bone Formation by Endochondral Ossification
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...
 01:11
Pyloric Obstruction
 01:18
Physical Growth During Infancy and Toddlerhood
 01:20
Inborn Errors of Metabolism