Related Experiment Video
Updated: Oct 20, 2026
Improved Rodent Model of Myocardial Ischemia and Reperfusion Injury
Published on: March 7, 2022
Role of A2A receptor in the modulation of myocardial reperfusion damage
A Cargnoni1, C Ceconi, A Boraso
1Cardiovascular Research Center, Salvatore Maugeri Foundation, Gussago, Brescia, Italy.

Abstract:
Adenosine protects myocardium from ischemia and reperfusion damage; however, the mechanism of action is still under discussion. We investigated whether (a) adenosine protects isolated crystalloid-perfused rabbit heart from ischemia/ reperfusion injury; (b) this action is receptor mediated and what receptor subtypes are involved, and (c) this action is dependent on an enhanced nitric oxide production. Our results showed a cardioprotective effect of adenosine (10(-4) M), of nonselective adenosine-receptor agonist 5'-N-ethyl-carboxamidoadenosine (NECA; 5 x 10(-6) M), and of A2A agonists CGS 21680 (10(-8) and 10(-6) M), 2-hexynylNECA (10(-7) M). On the contrary, A1 agonist CCPA (10(-8) and 10(-6) M) does not provide any protection. The effect has been achieved in terms of significant reduction in contracture development during reperfusion [diastolic pressure was 46.8 +/- 7.1 mm Hg (p < 0.01); 46.1 +/- 7.8 mm Hg (p < 0.01); 46.9 +/- 5.5 mm Hg (p < 0.01); and 59.3 +/- 6.7 mm Hg (p < 0.05) with 10(-4) M adenosine, 5 x 10(-6) M NECA, 10(-6) M CGS 21680, and 10(-7) M 2-hexynylNECA, respectively, versus 77.6 +/- 5.0 mm Hg in control]; reduced creatine phosphokinase release (13.5 +/- 1.6, 22.2 +/- 7.9, 14.2 +/- 3.3, and 14.1 +/- 4.5 U/gww in treated hearts vs. 34.6 +/- 7.2 U/gww in controls; p < 0.05); improved energy metabolism [adenosine triphosphate (ATP) content is 9.9 +/- 0.5, 10.4 +/- 0.6, 9.8 +/- 0.5, and 10.5 +/- 0.5 micromol/gdw in treated hearts vs. 7.6 +/- 0.2 micromol/gdw; p < 0.05]. Moreover, our data indirectly show a functional presence of A2A receptors on cardiomyocytes as the protection is A2A mediated and exerted only during reperfusion, although in the absence of blood and coronary flow changes. These activities appear independent of nitric oxide pathways, as adenosine and 2-hexynylNECA effects are not affected by the presence of a nitric oxide-synthase inhibitor (10(-4) M L-NNA).

Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:31
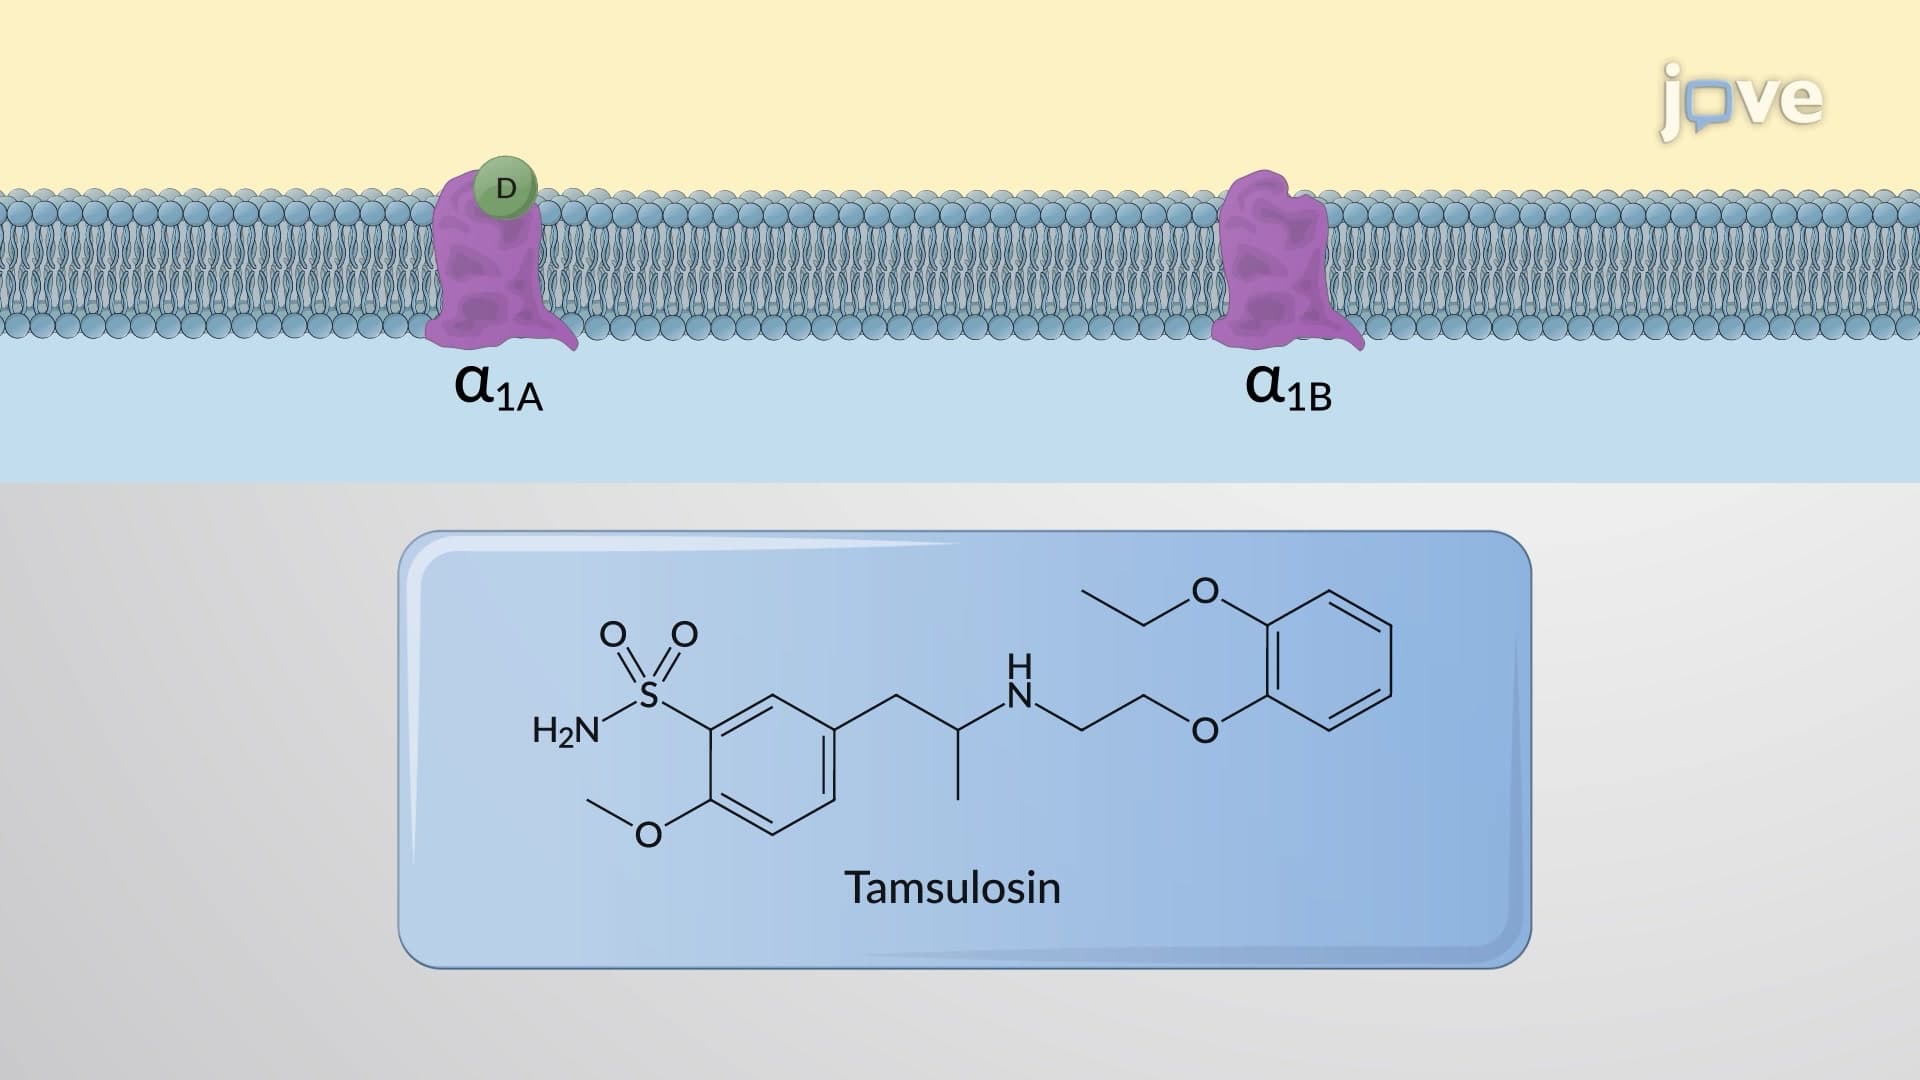
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:25
Aortic Regurgitation III: Medical Management
 01:22
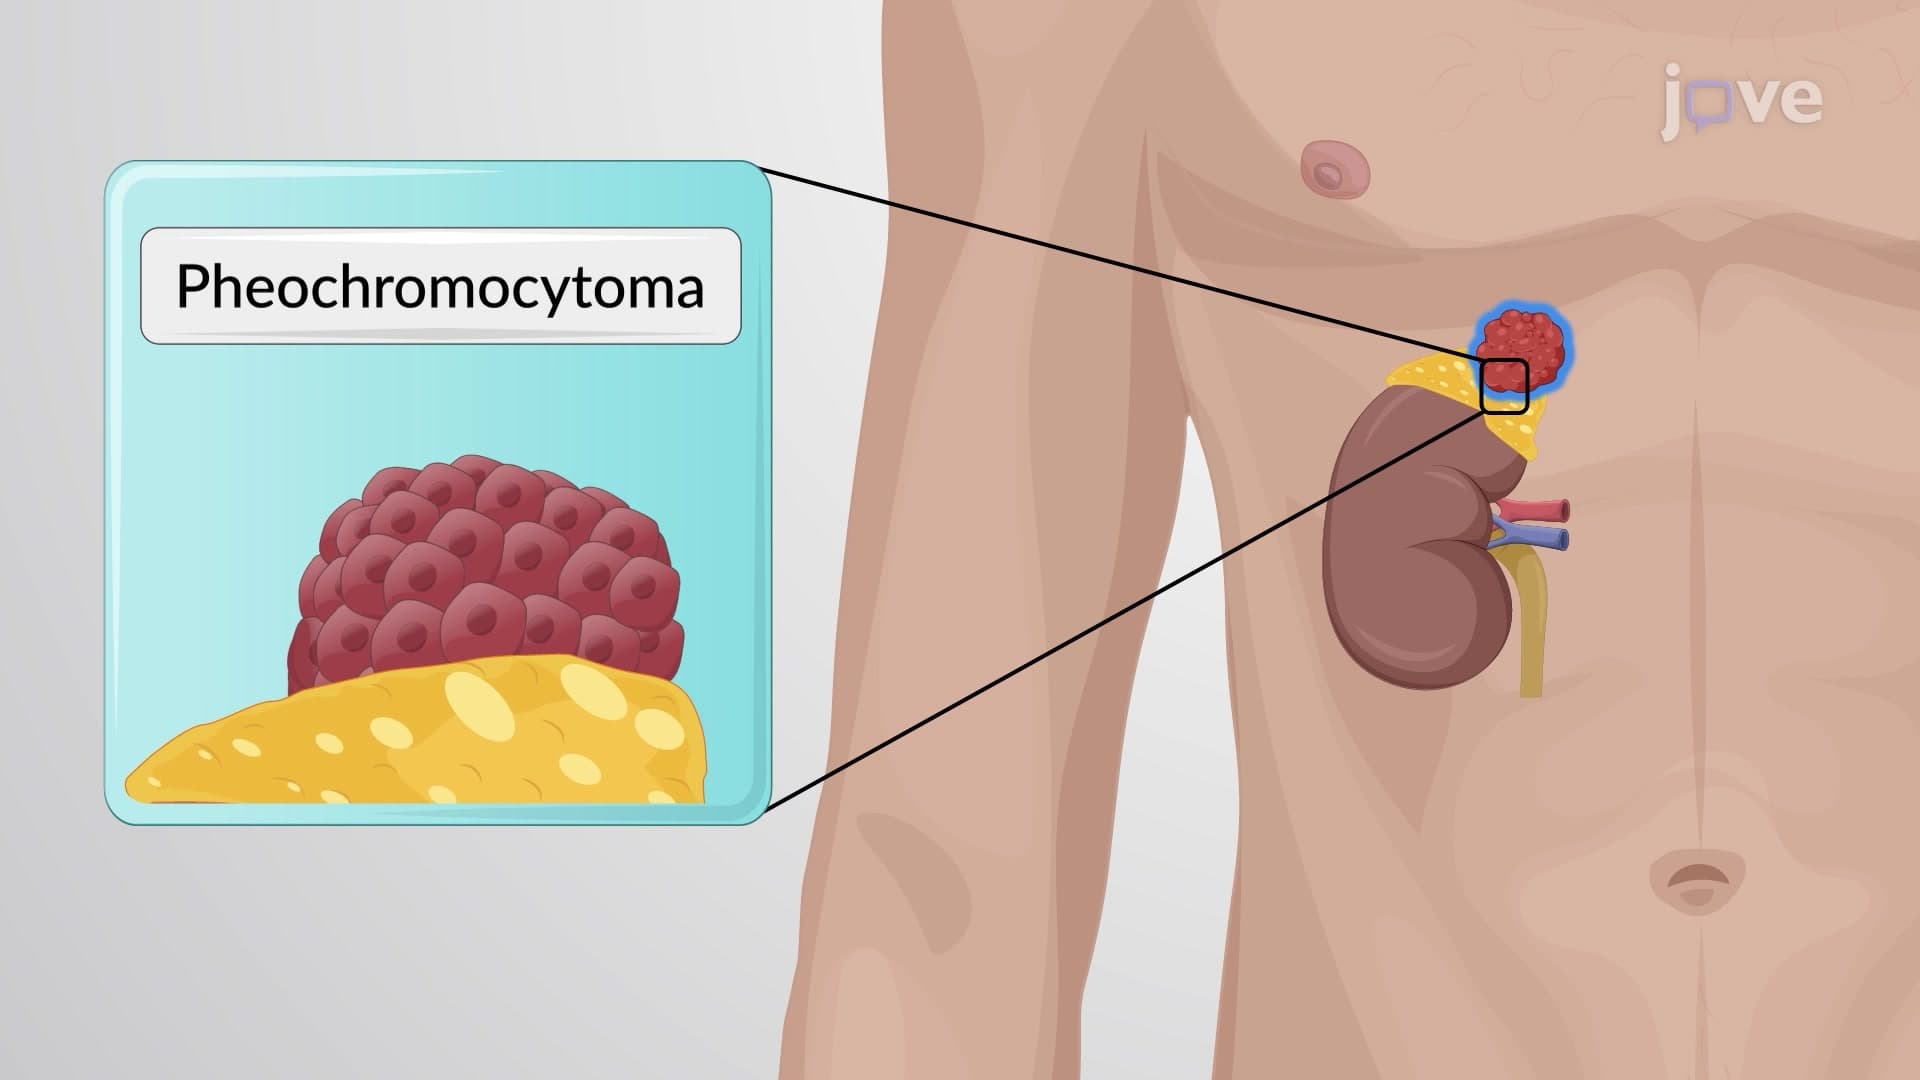
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...