Which unruptured cerebral aneurysms should be treated? A cost-utility analysis
Related Experiment Video
Updated: Oct 20, 2026
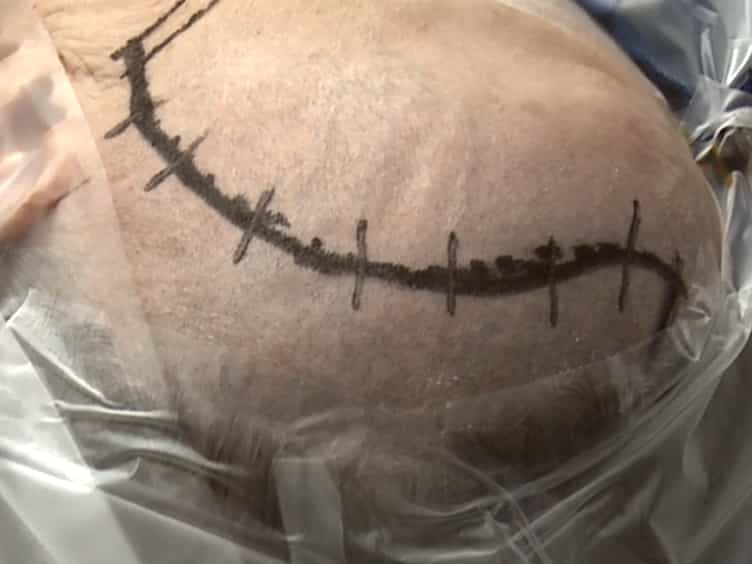
Minimally Invasive Thumb-sized Pterional Craniotomy for Surgical Clip Ligation of Unruptured Anterior Circulation Aneurysms
Published on: August 11, 2015
S C Johnston1, D R Gress, J G Kahn
1Department of Neurology, University of California, San Francisco 94143-0114, USA. clayj@itsa.ucsf.edu

Objective:
To determine which unruptured cerebral aneurysms should be treated considering the risks. benefits, and costs.
Background:
Asymptomatic unruptured cerebral aneurysms are commonly treated by surgical clipping or endovascular coil embolization to prevent subarachnoid hemorrhage (SAH).
Methods:
We performed a cost-utility analysis comparing surgical clipping and endovascular coil embolization with no treatment for unruptured aneurysms. Eight clinical scenarios were defined based on aneurysm size, symptoms, and history of SAH from a different aneurysm. Health outcomes of a hypothetical cohort of 50-year-old women were modeled over the projected lifetime of the cohort. Costs were assessed from the societal perspective. We compared net quality-adjusted life years (QALYs) and cost per QALY of each therapy to no treatment.
Results:
For an asymptomatic unruptured aneurysm less than 10 mm in diameter in patients with no history of SAH from a different aneurysm, both procedures resulted in a net loss in QALYs, and confidence intervals (CI) were not compatible with a benefit from treatment (clipping, loss of 1.6 QALY [95% CI 1.1 to 2.1]; coiling, loss of 0.6 QALY [95% CI 0.2 to 0.8]). For larger aneurysms (> or = 10 mm), those producing symptoms by compressing neighboring nerves and brain structures, or in patients with a history of SAH from a different aneurysm, treatment was cost-effective. Coiling appeared more effective and cost-effective than clipping but these differences depended on relatively uncertain model parameters.
Conclusions:
Treatment of small, asymptomatic, unruptured cerebral aneurysms in patients without a history of SAH worsens clinical outcomes, and thus is neither effective nor cost-effective. For aneurysms that are > or = 10 mm or symptomatic, or in patients with a history of SAH, treatment appears to be cost-effective.
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:22
Aneurysm IV: Nursing Management
 01:30
Aneurysm I: Introduction