Rapid progression to high-grade dysplasia in Barrett's esophagus after liver transplantation

J F Trotter1, S R Brazer

  • 1Division of Gastroenterology, Liver Transplant Service, Duke University Medical Center, Durham, NC 27710, USA.

Liver Transplantation and Surgery : Official Publication of the American Association for the Study of Liver Diseases and the International Liver Transplantation Society
|July 1, 1999
PubMed

Related Concept Videos

Barrett Esophagus-I: Introduction01:21

Barrett Esophagus-I: Introduction

Barrett's esophagus is a medical condition where the esophageal mucosa is significantly damaged by stomach acid or other digestive fluids, often due to long-term exposure associated with gastroesophageal reflux disease (GERD). In GERD, a weakened or abnormally relaxed lower esophageal sphincter allows stomach acid to flow persistently into the esophagus.
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
Barrett Esophagus-II: Clinical Manifestations and Management01:21

Barrett Esophagus-II: Clinical Manifestations and Management

Individuals with Barrett's esophagus are often asymptomatic, but they may experience symptoms commonly associated with GERD, such as heartburn and acid regurgitation. Additional symptoms can include difficulty swallowing, chest pain, unintentional weight loss, blood in the stool (which may appear black, tarry, or bloody), and episodes of vomiting.
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
Cellular Adaptation IV: Dysplasia and Metaplasia01:24

Cellular Adaptation IV: Dysplasia and Metaplasia

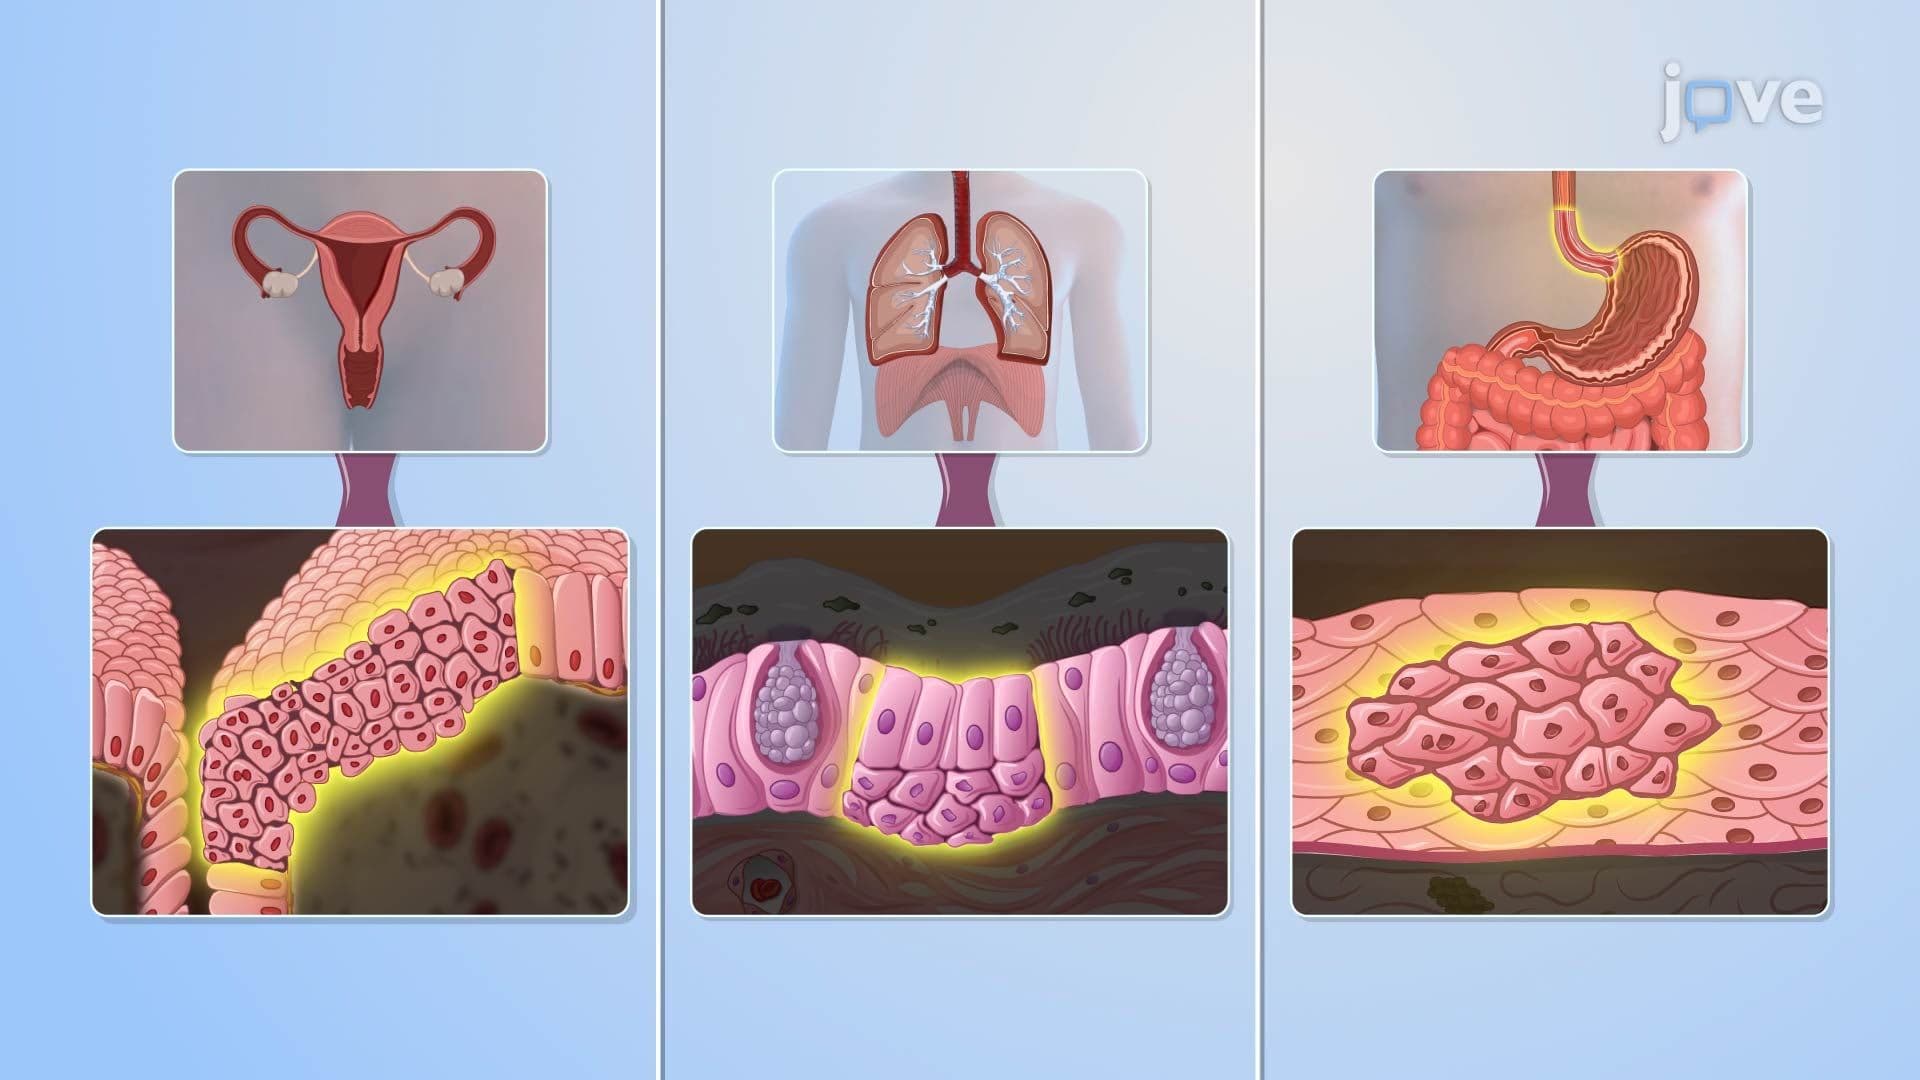
DysplasiaDysplasia refers to abnormal changes in the size, shape, and organization of mature cells, characterized by pleomorphism, nuclear abnormalities, and increased mitotic activity. It commonly affects epithelial tissues, including the cervix, gastrointestinal tract, respiratory mucosa, and endometrium. Although it may occur alongside hyperplasia, dysplasia is not a true adaptive response but a preneoplastic change with potential to progress to cancer.When confined above the basement...
Cirrhosis II: Pathophysiology01:24

Cirrhosis II: Pathophysiology

Cirrhosis is a progressive chronic liver injury caused by prolonged inflammation, excessive fibrotic remodeling, and impaired regeneration. Over time, repeated hepatic insults disrupt the liver’s architecture and function, leading to reduced blood flow, impaired bile drainage, and diminished metabolic capacity.Pathophysiology of cirrhosisCirrhosis arises from three main responses to chronic liver damage: inflammation, immune activation, and hepatocyte death. These processes lead to structural...
Esophageal Strictures-I: Introduction01:30

Esophageal Strictures-I: Introduction

Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
Esophageal Varices-I: Introduction01:24

Esophageal Varices-I: Introduction

Esophageal varices are dilated, tortuous veins which are found mainly in the submucosa of the lower esophagus but which may also appear higher up or extend into the stomach. They develop due to increased pressure in the portal venous system, often as a result of liver cirrhosis. This condition scars and damages the liver, impeding normal blood flow through the portal vein. To compensate, blood seeks alternative pathways, forming fragile new vessels (varices) in the esophagus and stomach. These...