Related Experiment Video
Updated: Aug 11, 2026

Humanized NOD/SCID/IL2rγnull (hu-NSG) Mouse Model for HIV Replication and Latency Studies
Published on: January 7, 2019
Hepatitis C virus-associated glomerular disease in patients with human immunodeficiency virus coinfection
J T Cheng1, H L Anderson, G S Markowitz
1Department of Medicine at Harlem Hospital Center, New York, New York 10037, USA. jc31@columbia.edu

Insights
Hepatitis C virus (HCV)-associated glomerular disease in HIV coinfection rapidly progresses to kidney failure. This aggressive renal disease, common in intravenous drug users, requires renal biopsy for accurate diagnosis and differs from HIV-associated nephropathy.
Area of Science:
- Nephrology
- Infectious Diseases
- Immunology
Background:
- Chronic Hepatitis C virus (HCV) infection is a known cause of glomerular disease.
- HCV is prevalent in intravenous drug users, a population also at risk for HIV coinfection.
- HIV-HCV coinfection can lead to complex renal pathologies that mimic HIV-associated nephropathy.
Purpose of the Study:
- To describe the clinical-pathologic features and outcomes of HCV-associated glomerular disease (HCV-GD) in patients coinfected with HIV.
- To differentiate HCV-GD from HIV-associated nephropathy in this coinfected population.
Main Methods:
- Retrospective analysis of 14 patients with HCV-GD and HIV coinfection.
- Review of clinical presentations, laboratory findings (hypocomplementemia, cryoglobulinemia), renal biopsy results (membranoproliferative glomerulonephritis, membranous glomerulopathy), and patient outcomes.
- Comparison of survival rates between patients with and without advanced Acquired Immunodeficiency Syndrome (AIDS).
Main Results:
- The predominant renal biopsy findings were membranoproliferative glomerulonephritis (79%) and membranous glomerulopathy (21%).
- Clinical presentations included renal insufficiency, hematuria, hypertension, and nephrotic syndrome.
- The disease course was aggressive, with rapid progression to end-stage renal disease requiring dialysis (median 5.8 months).
- Patients with advanced AIDS had significantly shorter survival.
- High morbidity and mortality were observed, often linked to immunosuppression and advanced AIDS.
Conclusions:
- HCV-GD in HIV coinfection represents an aggressive renal disease that can be mistaken for HIV-associated nephropathy.
- Clinical clues like hypocomplementemia, cryoglobulinemia, hypertension, and hematuria may suggest HCV-GD.
- Renal biopsy is crucial for accurate diagnosis and differentiation from HIV-associated nephropathy.
- Coinfection with HIV portends a poor prognosis for patients with HCV-GD.
Abstract:
Chronic infection with hepatitis C virus (HCV) has been linked to the development of glomerular disease. HCV infection is highly prevalent among intravenous drug users, a population that is also at risk for HIV coinfection. This study reports the clinical-pathologic features and outcome of HCV-associated glomerular disease (HCV-GD) in 14 patients with HIV coinfection. All were intravenous drug users and all but one were African-Americans. Renal presentations included renal insufficiency, microscopic hematuria with active urine sediment, hypertension, and nephrotic syndrome or nephrotic-range proteinuria without hypercholesterolemia. Hypocomplementemia and cryoglobulinemia were present in 46 and 33% of patients, respectively. The predominant renal biopsy findings were membranoproliferative glomerulonephritis type 1 or type 3 (Burkholder subtype) in 79% of patients and membranous glomerulopathy with atypical features in 21% (including overlap with collapsing glomerulopathy in one patient). The clinical course was characterized by rapid progression to renal failure requiring dialysis. The overall morbidity and mortality were high with median time of 5.8 mo to dialysis or death. Although most patients died in renal failure, cause of death was primarily attributable to long-term immunosuppression and advanced AIDS. Patients with AIDS had shorter survival than those without (median survival time of 6.1 mo versus 45.9 mo, log-rank test P = 0.02). Only two patients were alive with stable renal function at follow-up of 28.5 mo. In patients with HCV-GD, coinfection with HIV leads to an aggressive form of renal disease that can be easily confused with HIV-associated nephropathy. Although hypocomplementemia, cryoglobulinemia, and more prominent hypertension and microscopic hematuria may provide clues to the presence of HCV-GD, renal biopsy is essential to differentiate HCV-GD from HIV-associated nephropathy.

Related Concept Videos
 01:10
Retrovirus Life Cycles
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...
 01:27
Cytomegalovirus Disease
 01:25
Hepatitis
 01:27
Cryptococcal Meningitis
 01:28
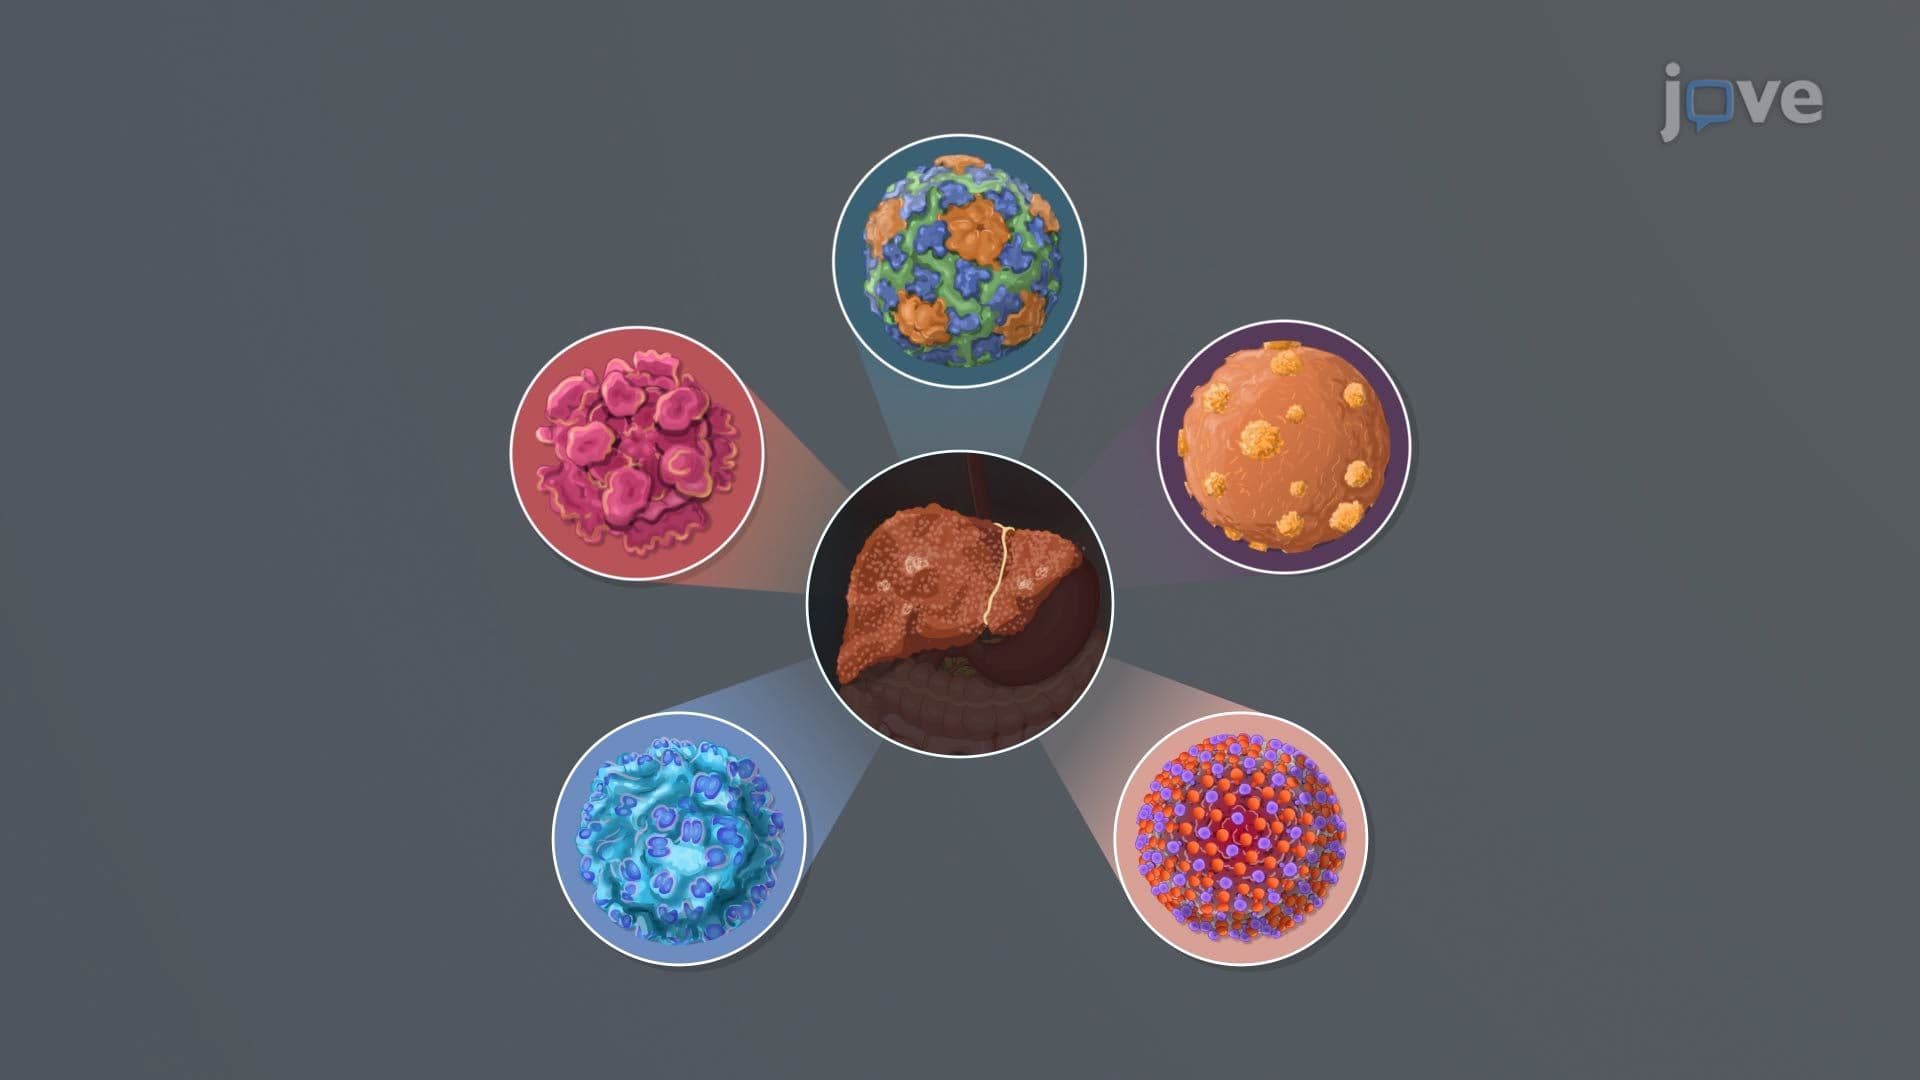
Viral Hepatitis I: Introduction