Heparin and low molecular weight heparin for treatment of acute pulmonary embolism
Related Experiment Video
Updated: Oct 13, 2026
Rapid Point-of-Care Assay of Enoxaparin Anticoagulant Efficacy in Whole Blood
Published on: October 12, 2012
1Department of Biostatistics, University of Oklahoma Health Sciences Center, Oklahoma City 73190, USA.

Abstract:
Pulmonary embolism occurs in more than 175,000 patients each year in the United States. The objectives of treatment are to prevent death from the existing embolus, to prevent death and morbidity from recurrent pulmonary embolism, and to prevent morbidity from recurrent deep-vein thrombosis. For patients with adequate cardiorespiratory reserve, the primary objective is to prevent recurrent pulmonary embolism. Anticoagulant therapy with intravenous unfractionated heparin or subcutaneous low molecular weight heparin followed by oral anticoagulant treatment for at least 3 months is the treatment of choice for most of these patients. Clinical trials indicate that the effectiveness of intravenous heparin depends on achieving an adequate heparin effect (activated partial thromboplastin time above lower limit) during the initial 24 hours. A validated protocol for intravenous heparin should be used to lessen the likelihood of delayed heparinization. Low molecular weight heparin given subcutaneously either once or twice daily is as effective as intravenous heparin for the treatment of patients with deep-vein thrombosis and submassive pulmonary embolism. Low molecular weight heparin enables many patients with uncomplicated deep-vein thrombosis to be treated in an outpatient setting.

Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:19
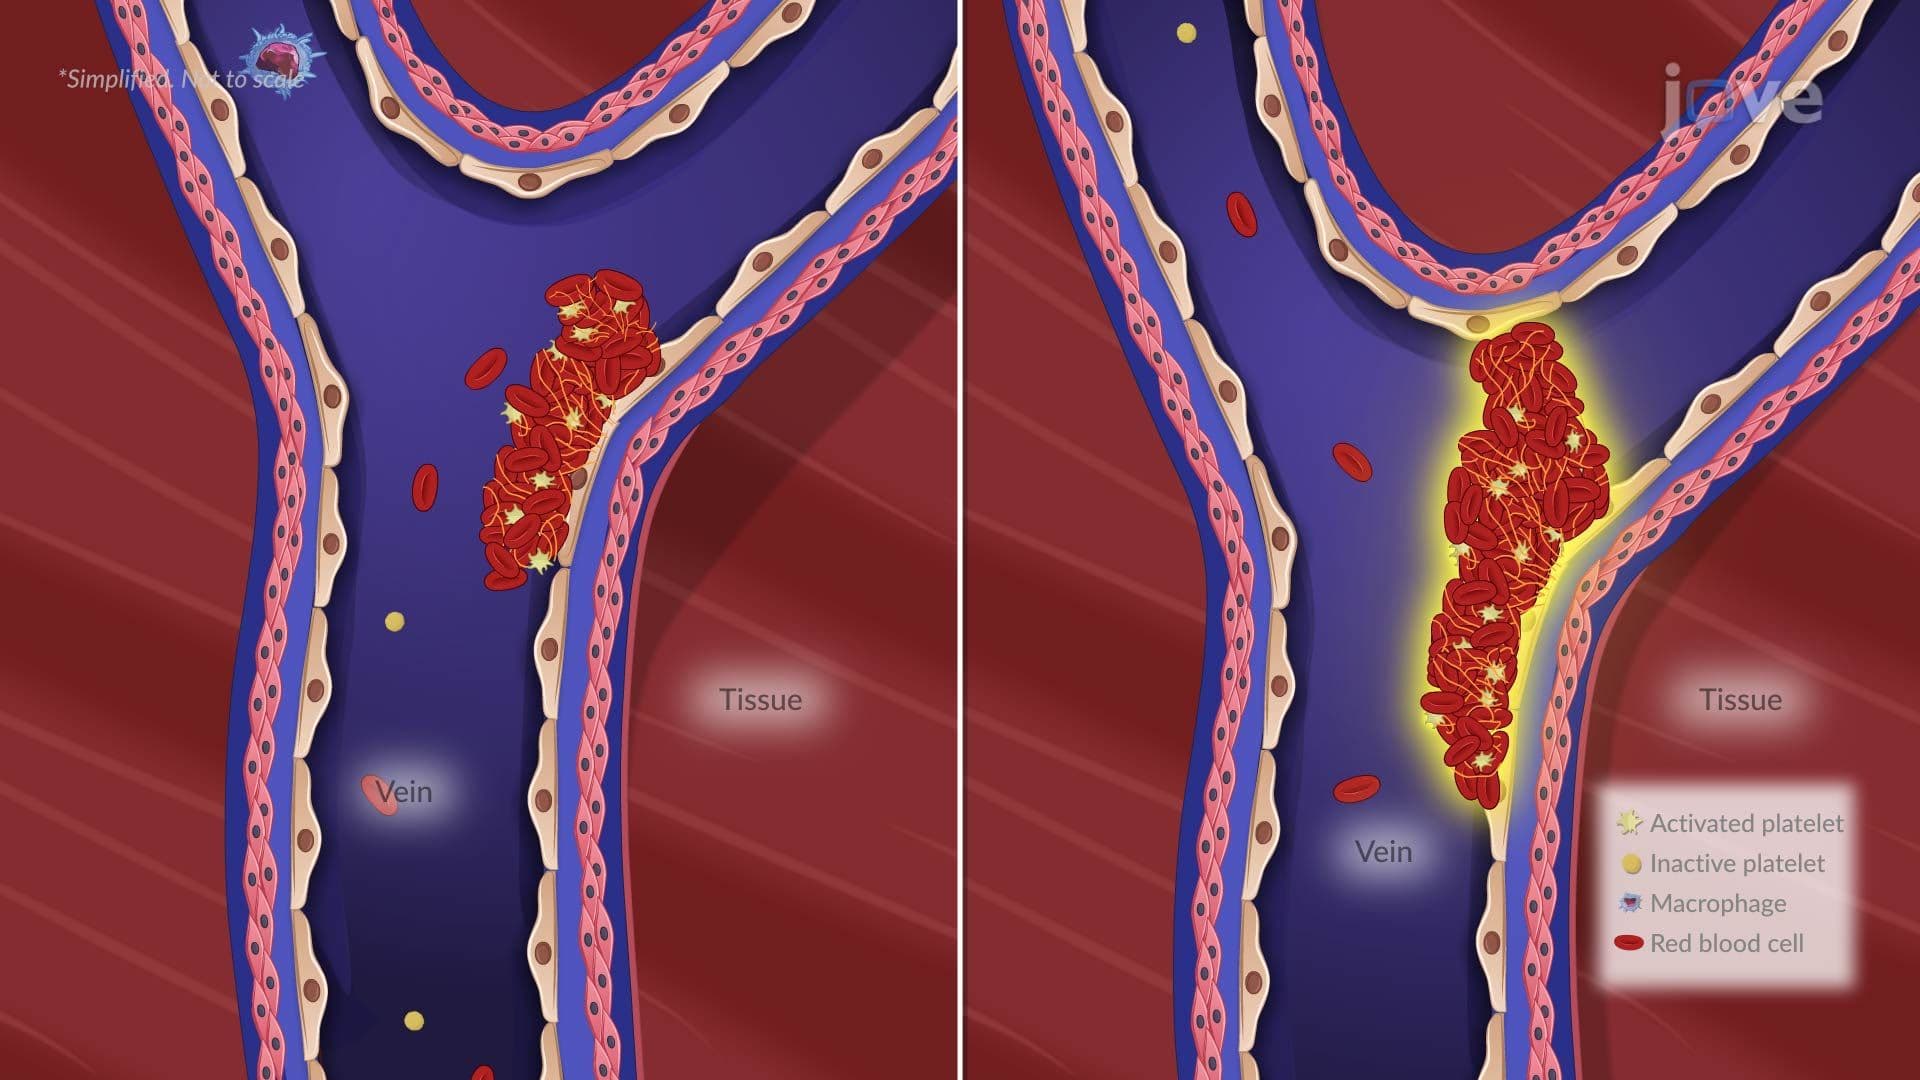
Pulmonary Embolism I: Introduction