Related Experiment Video
Updated: Oct 19, 2026

Visualization of Streptococcus pneumoniae within Cardiac Microlesions and Subsequent Cardiac Remodeling
Published on: April 7, 2015
Chlamydia pneumoniae infection and incident coronary heart disease: the Atherosclerosis Risk in Communities Study
F J Nieto1, A R Folsom, P D Sorlie
1Department of Epidemiology, School of Hygiene and Public Health, The Johns Hopkins University, Baltimore, MD 21205, USA.

Insights
Past Chlamydia pneumoniae infection may not be a significant risk factor for coronary heart disease (CHD). Further long-term studies are needed to confirm its role in early atherosclerosis development.
Area of Science:
- Epidemiology
- Infectious Disease
- Cardiovascular Science
Background:
- Past Chlamydia pneumoniae infection is suggested to link with atherosclerotic disease.
- Prospective study evidence remains limited.
Purpose of the Study:
- To investigate the association between chronic Chlamydia pneumoniae infection and incident coronary heart disease (CHD).
Main Methods:
- A case-cohort study design was employed using data from the Atherosclerosis Risk in Communities Study.
- Serum C. pneumoniae immunoglobulin G (IgG) antibody titers were measured at baseline in incident CHD cases (n=246) and a cohort sample (n=550).
- Multivariate analyses adjusted for traditional CHD risk factors.
Main Results:
- A higher prevalence of IgG antibody titers (≥1:64) was observed in CHD cases (65%) compared to non-cases (55%).
- Initial analyses showed a relative hazard of 1.6 for CHD with elevated titers (p < 0.01).
- Multivariate adjustment attenuated this association (relative hazard = 1.2), rendering it nonsignificant. However, a significant association persisted among nonsmokers.
Conclusions:
- The study does not provide strong evidence supporting Chlamydia pneumoniae infection as a risk factor for clinical CHD.
- Longer follow-up studies are required to ascertain the role of C. pneumoniae in early atherogenesis.
Abstract:
Pathologic findings and cross-sectional epidemiologic studies suggest that past infection with Chlamydia pneumoniae is associated with clinical and subclinical atherosclerotic disease, although evidence from prospective studies is still scarce. The association between chronic infection by C. pneumoniae and incident coronary heart disease (CHD) was investigated in a case-cohort study conducted among participants in the Atherosclerosis Risk in Communities Study who were free of CHD at the baseline examination (1986-1989). Levels of C. pneumoniae immunoglobulin G (IgG) antibodies in serum collected at baseline from 246 incident cases of CHD identified during follow-up (median, 3.3 years; maximum, 5 years) were compared with those from a stratified sample of the baseline cohort (n = 550). Among incident CHD cases, 65% had IgG antibody titers > or =1:64, compared with 55% of noncases (compared with negative IgG titers, the relative hazard of CHD was 1.6 (p < 0.01)). In multivariate analyses controlling for other risk factors (age, gender, smoking, serum cholesterol, hypertension, diabetes mellitus, and educational level), the above estimates were substantially reduced and became statistically nonsignificant (relative hazard = 1.2). A significantly increased CHD hazard associated with IgG antibody titers > or =1:64 was observed among nonsmokers, even after adjustment for other risk factors. Overall, these results do not provide strong support for the hypothesis that C. pneumoniae infection is a risk factor for clinical CHD. Studies with longer follow-up periods will be necessary to determine whether C. pneumoniae infection is involved as an etiologic factor in earlier phases of atherogenesis.
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:25
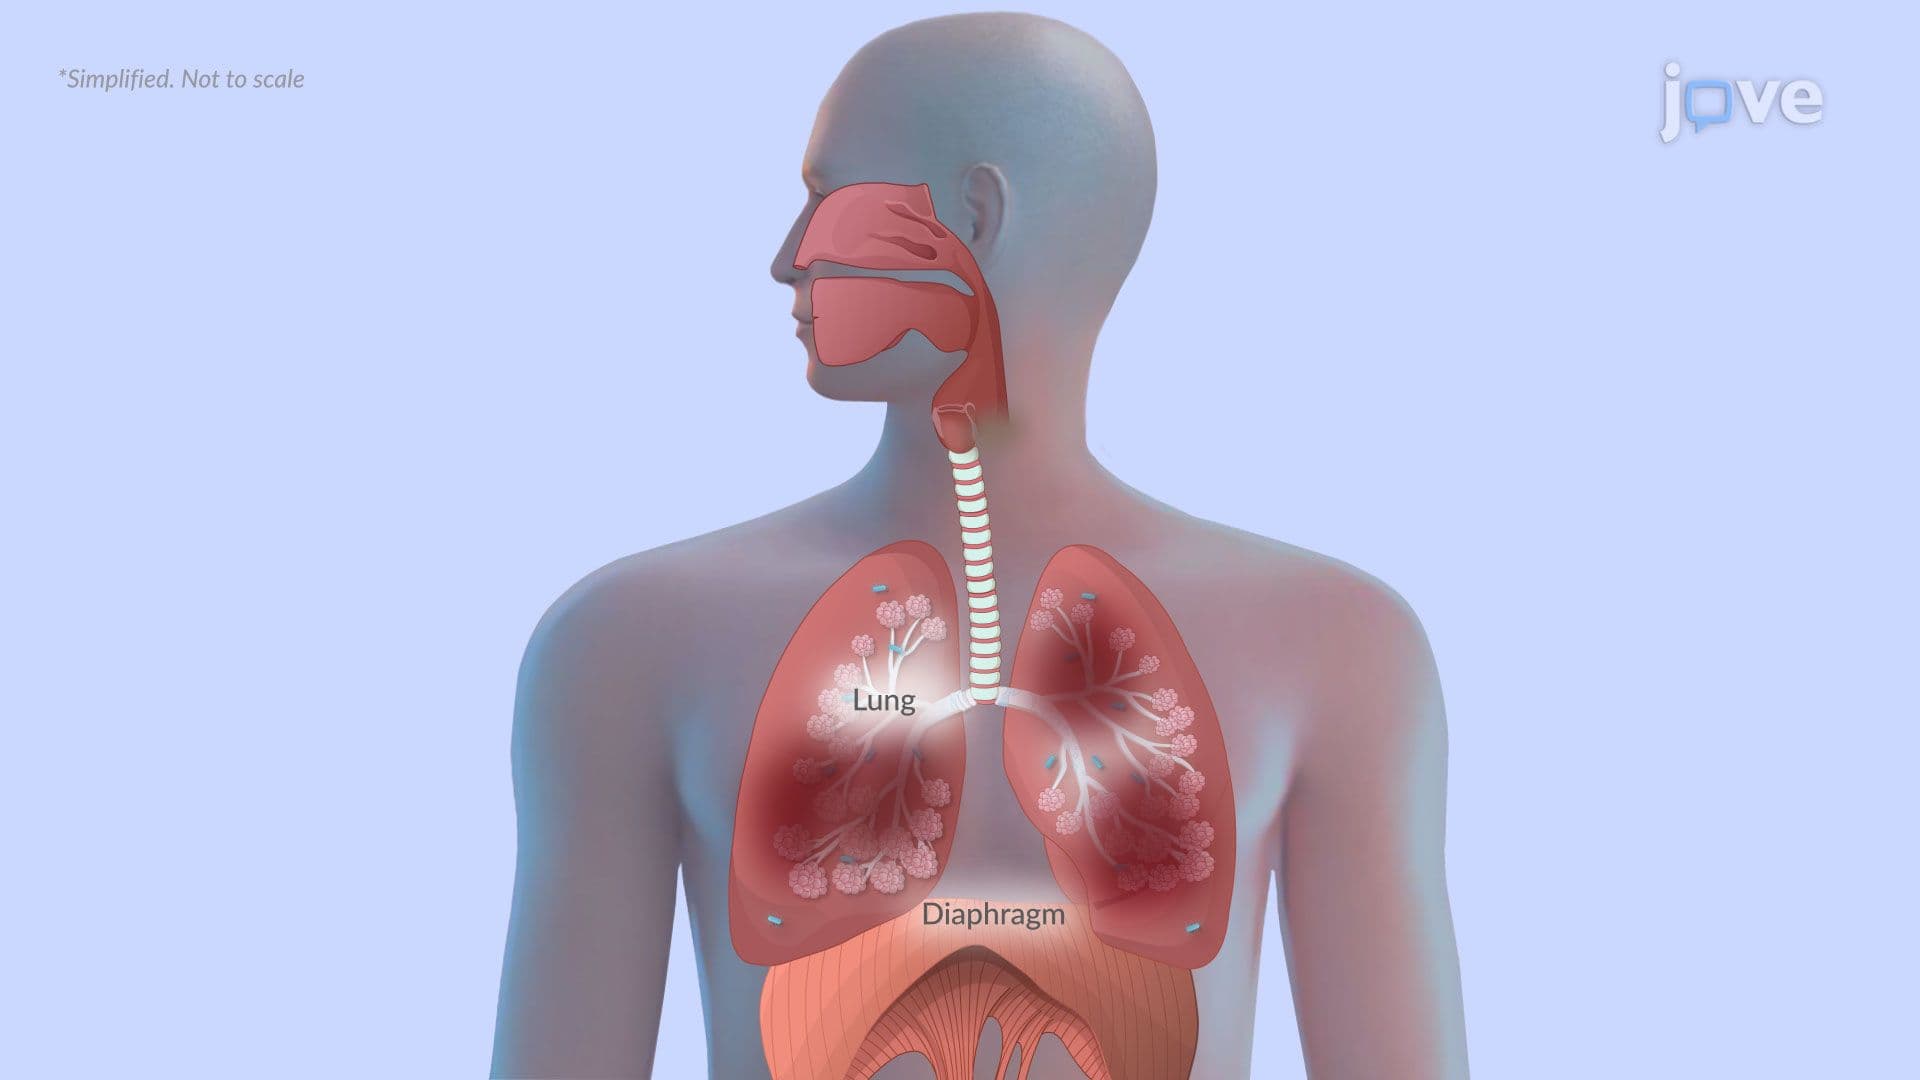
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology