Related Experiment Video
Updated: Aug 18, 2026


Quantifying Glomerular Permeability of Fluorescent Macromolecules Using 2-Photon Microscopy in Munich Wistar Rats
Published on: April 17, 2013
Characterization of gentamicin pharmacokinetics in patients hemodialyzed with high-flux polysulfone membranes
N B Amin1, I D Padhi, M A Touchette
1Division of Nephrology, Henry Ford Hospital, Detroit, MI, USA.

Abstract:
To characterize the pharmacokinetics of gentamicin during and after hemodialysis (using polysulfone Fresenius F-80 membranes (Fresenius USA, Inc, Walnut Creek, CA), surface area 1.6 m(2)), eight patients with end-stage renal disease undergoing chronic hemodialysis receiving the drug for therapeutic indications were enrolled. Intradialytic gentamicin half-life, clearance, and amount of gentamicin recovered during a hemodialysis session were also determined. Serum gentamicin concentrations were analyzed using fluorescence polarization immunoassay. The amount of gentamicin recovered was 64.3 +/- 14.4 mg, whereas the intradialytic gentamicin half-life was 2.24 +/- 0.83 hours, with a clearance of 116 +/- 9 mL/min. Gentamicin concentrations rebounded by 27.86% +/- 16.4% at 1. 5 +/- 0.52 hours after the end of the hemodialysis session. The decrease in gentamicin concentrations comparing maximum rebound to prehemodialysis concentrations was 53.54% +/- 9.97%. A variable yet substantial amount of gentamicin is removed during hemodialysis using F-80 membranes; hence, supplemental doses are necessary to avoid potential treatment failures. The supplemental doses of gentamicin calculated based on gentamicin concentrations obtained immediately postdialysis could be overestimated if the postdialysis rebound concentrations are not considered. A dosing regimen is suggested using the pharmacokinetic parameters defined by the present study and population estimate of volume of distribution.
Related Concept Videos
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
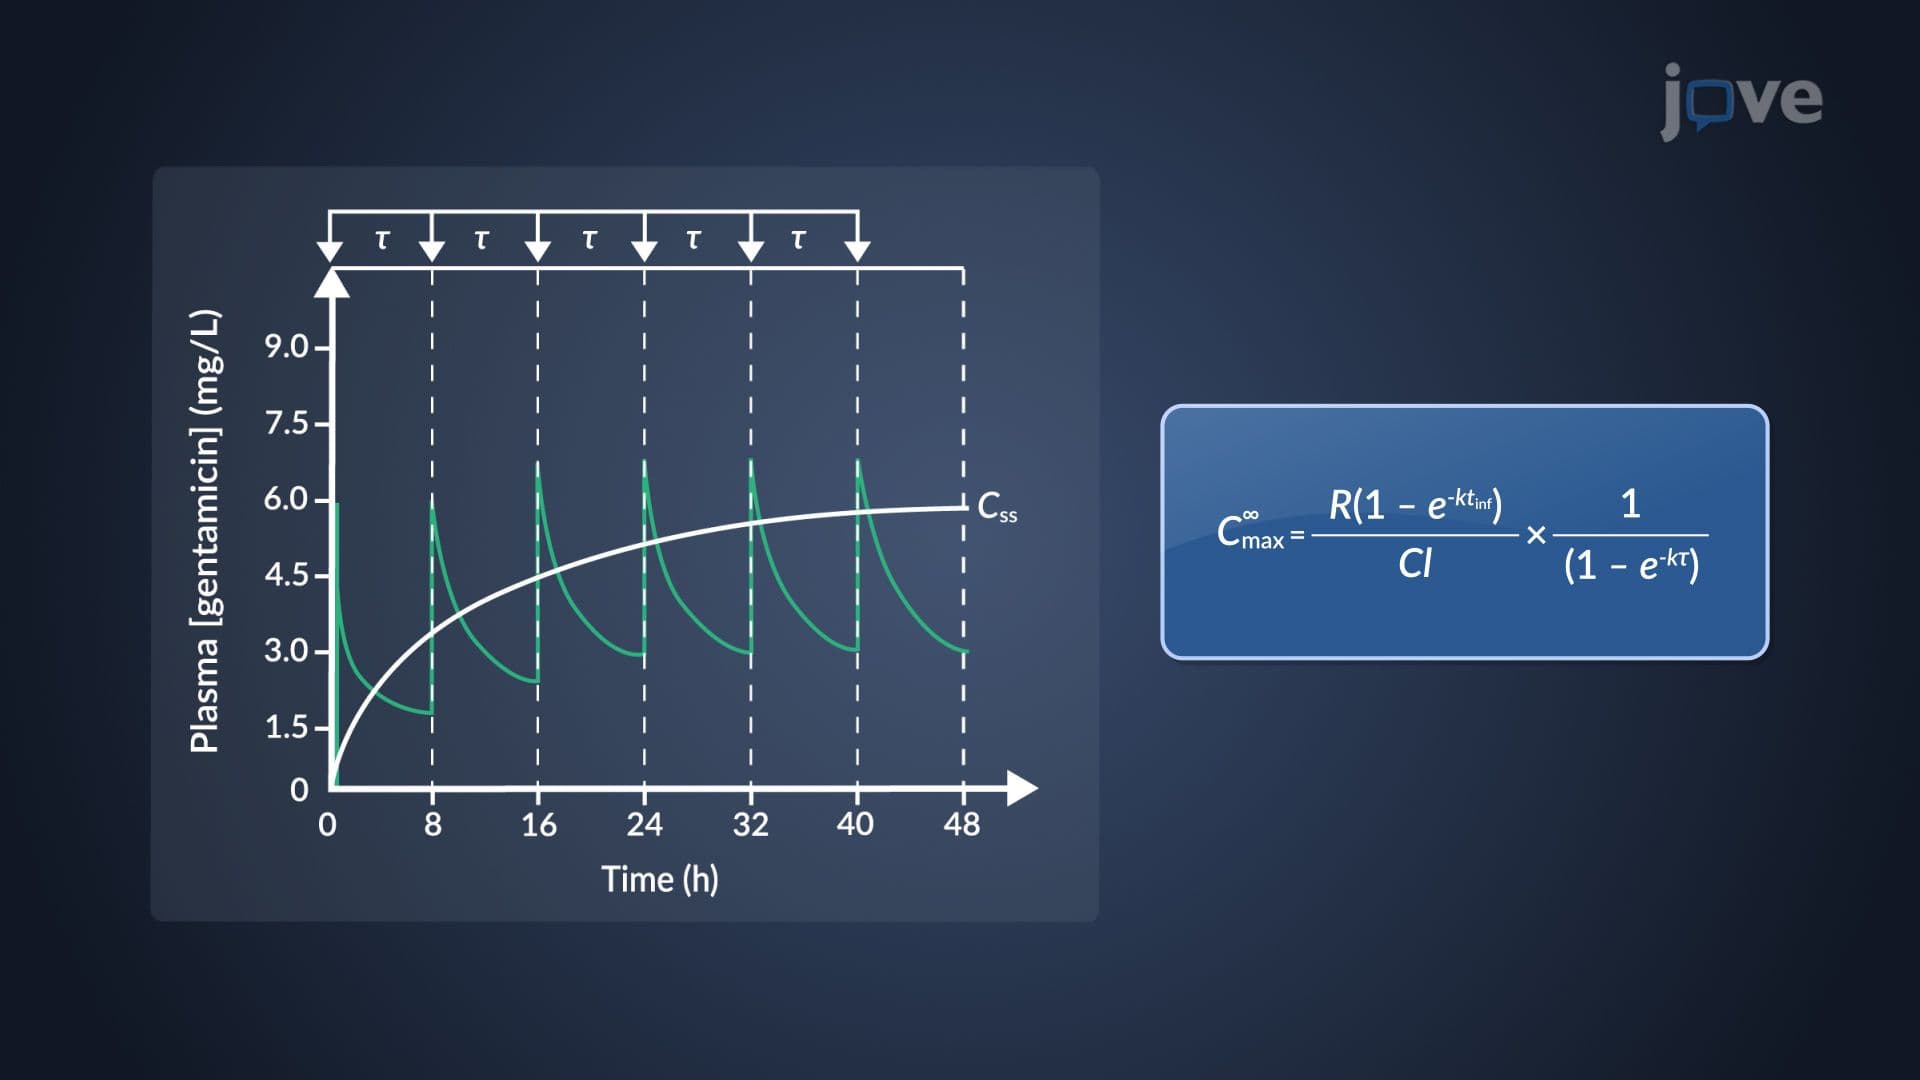
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
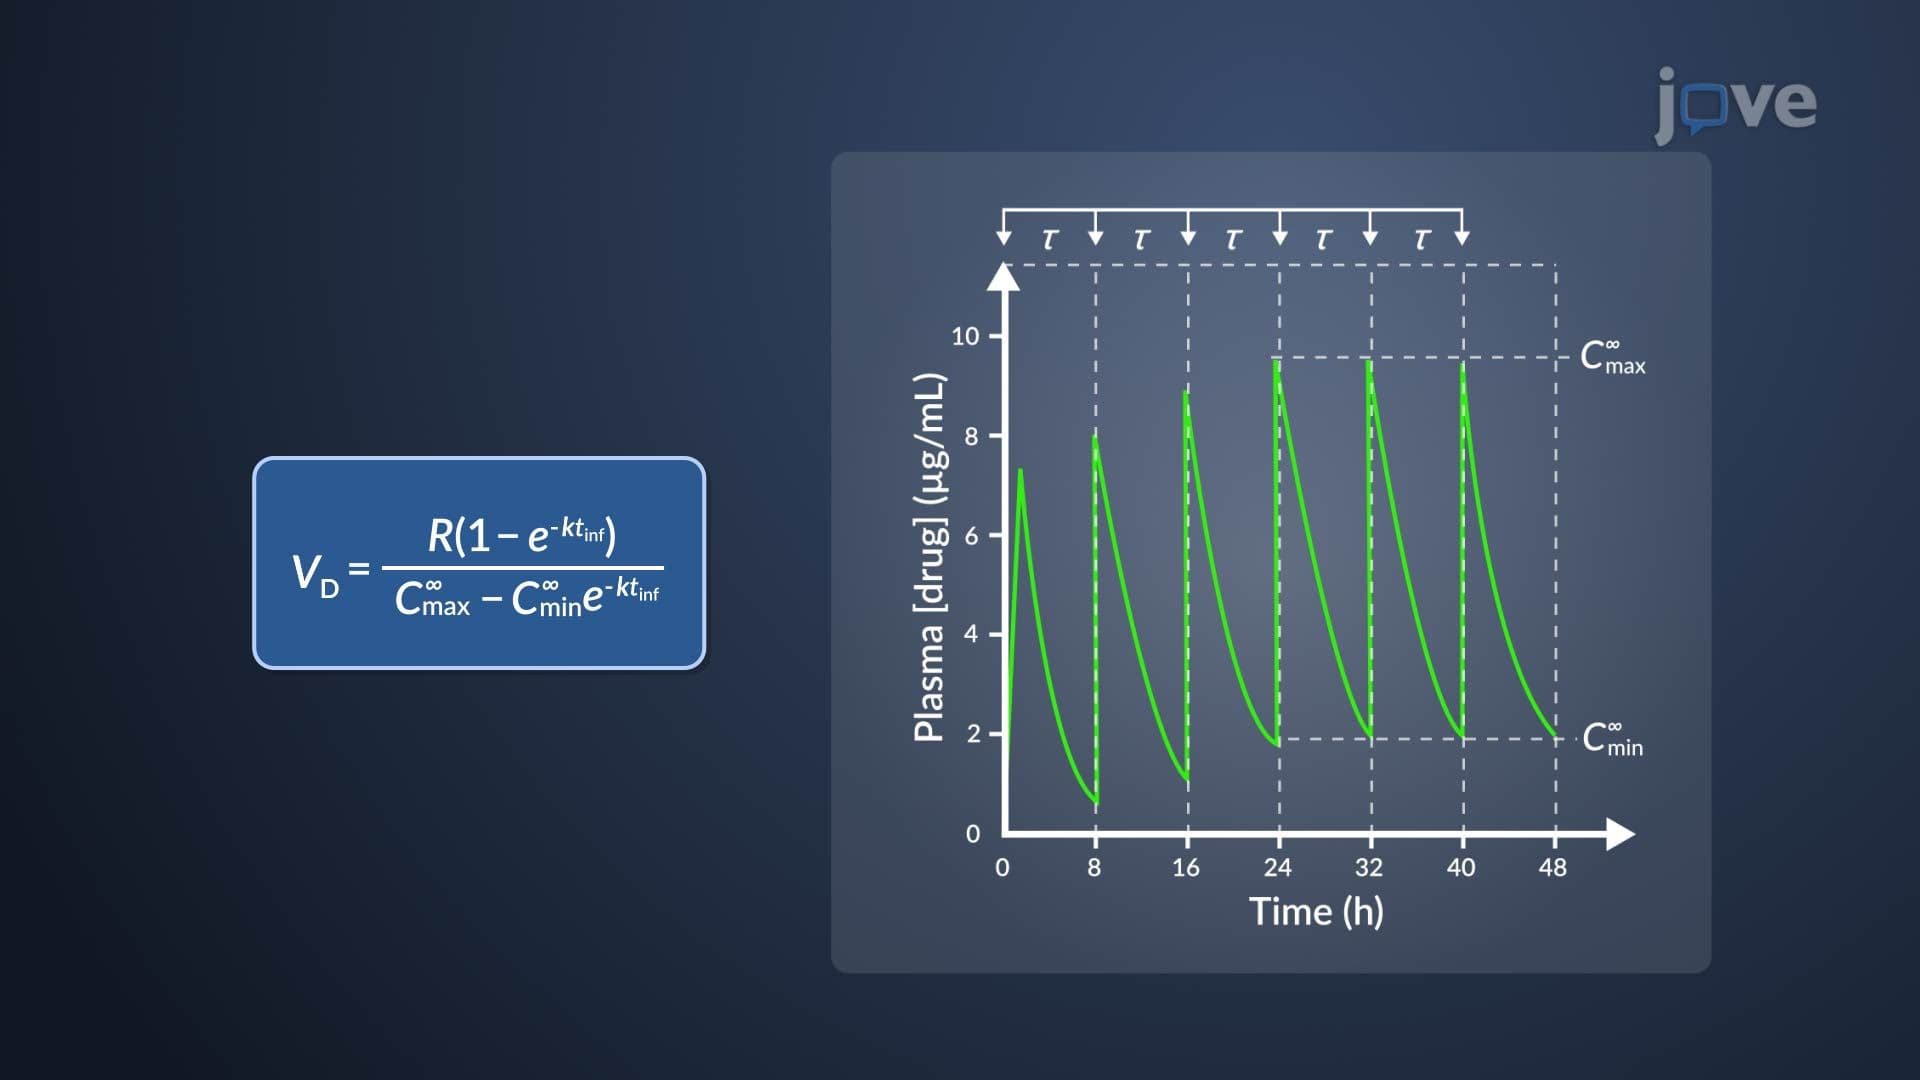
Estimation of k and VD of Aminoglycosides
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion