Related Experiment Video
Updated: Aug 4, 2026
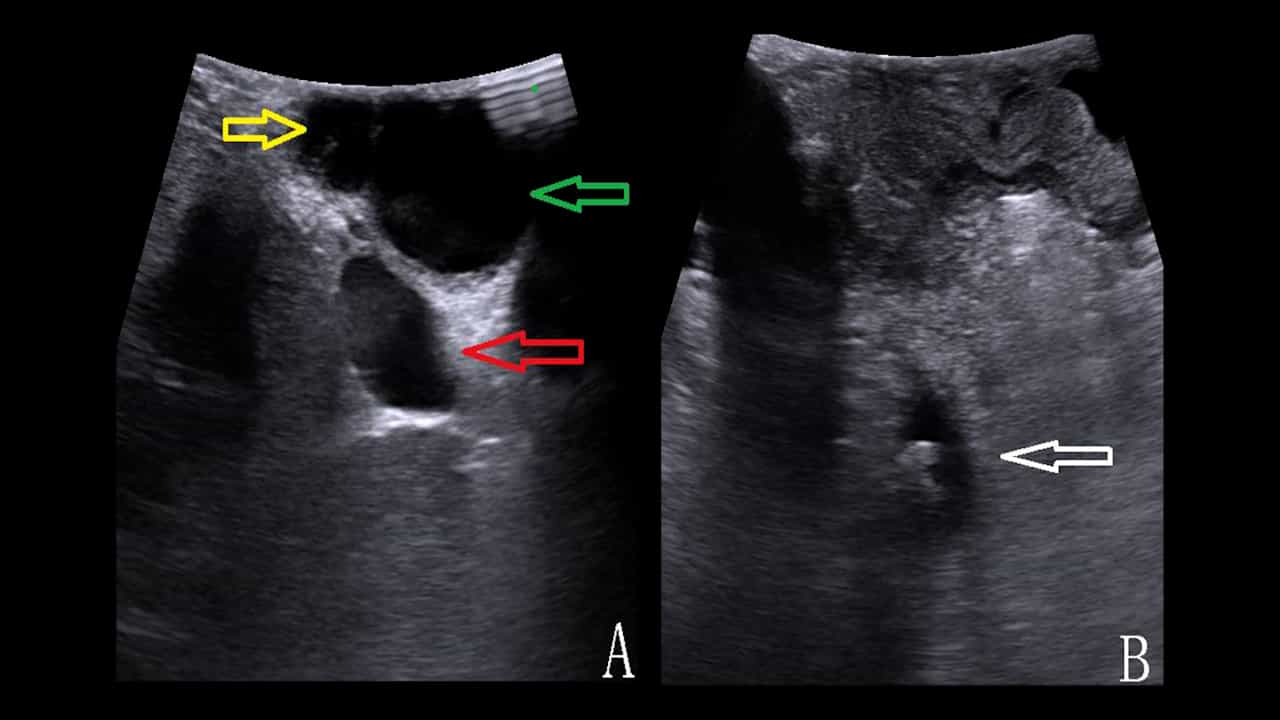
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
The efficacy of laparoscopy in acute cholecystitis
F Chahin1, N Elias, A Paramesh
1Department of Surgery, North Oakland Medical Centers, Pontiac, MI 48341, USA.

Insights
Laparoscopic cholecystectomy is a safe and effective treatment for acute cholecystitis, offering shorter operating times and hospital stays. Conversion rates improved with surgeon experience, indicating a reliable surgical option.
Area of Science:
- Laparoscopic surgery
- Gastrointestinal surgery
- Surgical outcomes
Background:
- Acute cholecystitis management
- Cholecystectomy techniques
- Gallbladder disease treatment
Purpose of the Study:
- Evaluate laparoscopic cholecystectomy for acute cholecystitis
- Assess treatment outcomes
- Compare with open cholecystectomy
Main Methods:
- Retrospective analysis (1994-1996)
- University-affiliated teaching hospital
- Comparison of laparoscopic vs. open cholecystectomy
Main Results:
- Laparoscopic cholecystectomy associated with younger females
- Shorter operating times and length of stay for laparoscopic approach
- Lower complication rates and improving conversion rates with experience
Conclusions:
- Laparoscopic cholecystectomy is reliable, safe, and cost-effective for acute cholecystitis
- Caution advised due to potential technical hazards
- Surgical approach outcomes improve with surgeon experience
Objective:
To evaluate the role of laparoscopic cholecystectomy in acute cholecystitis and establish the outcomes of this treatment modality at North Oakland Medical Centers.
Methods:
This was a retrospective analysis over a three-year period (January 1, 1994 to December 31, 1996), performed at a University-affiliated urban teaching hospital, North Oakland Medical Centers, Pontiac, Michigan. Five hundred and fifty-seven patients underwent surgical treatment for gallbladder disease; 88 patients had acute cholecystitis, and 469 patients had chronic cholecystitis. Acute cholecystitis patients underwent surgery within 72 hours of the onset of symptoms; the patient's selection for laparoscopic cholecystectomy or open cholecystectomy depended on severity of disease, co-morbid factors and surgeon's preference. The parameters of age, gender, operating (OR) time, length of stay, complications, conversion rates from laparoscopic cholecystectomy to open cholecystectomy, and cost were compared in patients who underwent laparoscopic cholecystectomy and/or open cholecystectomy.
Results:
Patients chosen to undergo laparoscopic cholecystectomy for acute cholecystitis tended to be younger females. Patients treated with laparoscopic cholecystectomy for acute cholecystitis had shorter OR times and LOS compared to patients treated with open cholecystectomy for acute cholecystitis. Conversion rates (CR) were 22% in acute cholecystitis and 5.5% in chronic cholecystitis during the study period; CR diminished considerably between the first and third year. Complications were also lower in patients who underwent laparoscopic cholecystectomy vs. open cholecystectomy.
Conclusions:
Laparoscopic cholecystectomy appears to be a reliable, safe, and cost-effective treatment modality for acute cholecystitis; however, the surgical approach should be cautionary because of the spectrum of potential technical hazards. CR is improving as surgeons gain experience.