Related Experiment Video
Updated: Aug 15, 2026
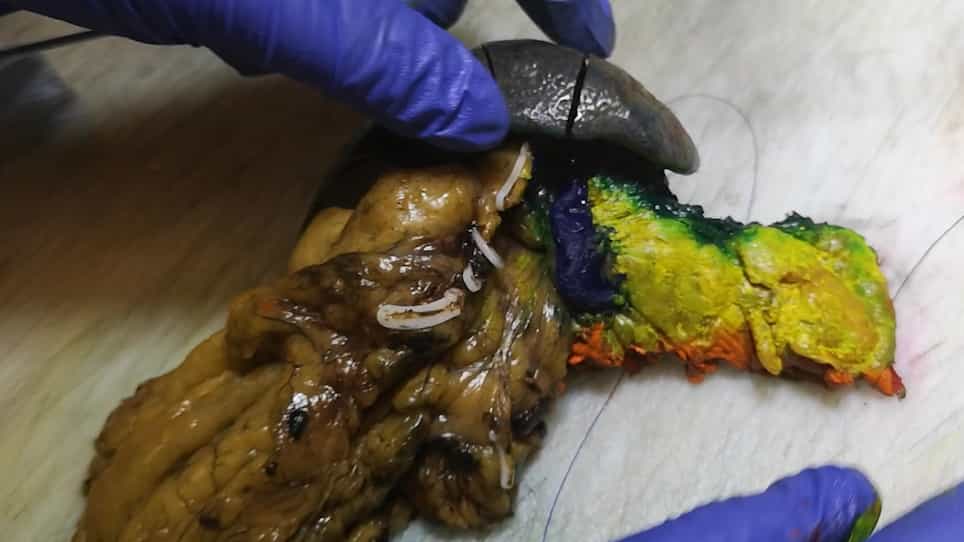

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Development and progress in resective surgery for pancreatic cancer
1Department of Surgery, Medical College of Ohio, 3065 Arlington Avenue, Toledo, Ohio 43614-5807, USA.

Abstract:
Pancreatoduodenectomy was developed from experience gained with transduodenal ampullectomy, preceded by a relatively bloodless cholecystoenterostomy. Although Codivilla (1898) and Kausch (1909) each achieved a single survivor following pancreatoduodenectomy, further development of the operation had to await discovery of vitamin K and a description of human blood types, the latter leading to the development of blood banks. After vitamin K and blood banks became available, Allen O. Whipple and his resident C.R. Mullins developed the two-stage pancreatoduodenectomy (1934-1935) and Whipple the one-stage procedure (1940). Although the mortality rate from pancreatoduodenectomy remained approximately 33% for more than 25 after Whipple's reports, concentration of resection in "centers of specialization" has now reduced mortality rates below 5%. Thus operative survival has been achieved, but long-term survival has not kept pace. Long-term data remain inadequate because they are usually expressed as Kaplan-Meier estimates and because of the nonuniformity of reporting (e.g., exclusion of postoperative deaths and palliative resections, intraoperative adjuvant therapies, and variations of operative techniques). Widely based Kaplan-Meier estimates of 5-year survival range from 12% to 15% after resection and more than 20% in selected categories. Total pancreatectomy has not improved short- or long-term survival rates. Extended lymphadenectomy and resection of peripancreatic soft tissues, as currently developed in several surgical clinics in Japan, suggest a higher incidence of complications but perhaps more long-term survivors. Interpretation of their data is currently subject to the same limitations noted above. As our surgical forebears needed vitamin K and blood banks to achieve postresection survival, we and our students need effective adjuvant therapy of micrometastases and better modalities for early diagnosis to improve long-term survival.
More Related Videos
 12:34
Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
 13:56
Robot Assisted Distal Pancreatectomy with Celiac Axis Resection (DP-CAR) for Pancreatic Cancer: Surgical Planning and Technique
Published on: August 14, 2021