Related Experiment Video
Updated: Aug 9, 2026


Flow Cytometry to Estimate Leukemia Stem Cells in Primary Acute Myeloid Leukemia and in Patient-derived-xenografts, at Diagnosis and Follow Up
Published on: March 26, 2018
Acute myelogenous leukemia blasts as accessory cells during T lymphocyte activation: possible implications for future
1Department of Medicine, Haukeland University Hospital and the University of Bergen, Norway.

Both clinical and experimental evidence indicate that T lymphocytes can mediate antileukemic effects in acute myelogenous leukemia (AML). These antileukemic effects can be either nonspecific cytotoxicity (killer cell activity) or reactivity against leukemia-specific antigenic peptides presented by self-HLA molecules. The antigen-specific T cell activation requires recognition of specific peptides together with costimulatory signalling. For most patients the AML blasts express both HLA class I and class II molecules for antigenic presentation, but patients are heterogeneous with regard to: (1) expression of costimulatory binding molecules; (2) expression of receptors/counterreceptors involved in induction of apoptosis; (3) constitutive release of immunomodulatory soluble mediators. This heterogeneity suggests that the ability of AML blasts to initiate an antileukemic T cell response will differ between individual patients. Thus, clinical approaches for immunotherapy in AML have to overcome three major problems. First, the therapy should reduce the patient heterogeneity so that therapeutic effects become more predictable; or alternatively one should define patient subsets which are likely to benefit from immunotherapy. Second, immunotherapy should enhance antileukemic T cell reactivity or blast susceptibility to immune attacks. Third, the therapeutic procedures must be safe and suitable for routine use. All three problems probably have to be solved before immunotherapy can become a routine treatment.
Both clinical and experimental evidence indicate that T lymphocytes can mediate antileukemic effects in acute myelogenous leukemia (AML). These antileukemic effects can be either nonspecific cytotoxicity (killer cell activity) or reactivity against leukemia-specific antigenic peptides presented by self-HLA molecules. The antigen-specific T cell activation requires recognition of specific peptides together with costimulatory signalling. For most patients the AML blasts express both HLA class I and class II molecules for antigenic presentation, but patients are heterogeneous with regard to: (1) expression of costimulatory binding molecules; (2) expression of receptors/counterreceptors involved in induction of apoptosis; (3) constitutive release of immunomodulatory soluble mediators. This heterogeneity suggests that the ability of AML blasts to initiate an antileukemic T cell response will differ between individual patients. Thus, clinical approaches for immunotherapy in AML have to overcome three major problems. First, the therapy should reduce the patient heterogeneity so that therapeutic effects become more predictable; or alternatively one should define patient subsets which are likely to benefit from immunotherapy. Second, immunotherapy should enhance antileukemic T cell reactivity or blast susceptibility to immune attacks. Third, the therapeutic procedures must be safe and suitable for routine use. All three problems probably have to be solved before immunotherapy can become a routine treatment.


Related Concept Videos
 01:15
Differentiation of Common Myeloid Progenitor Cells
 01:23
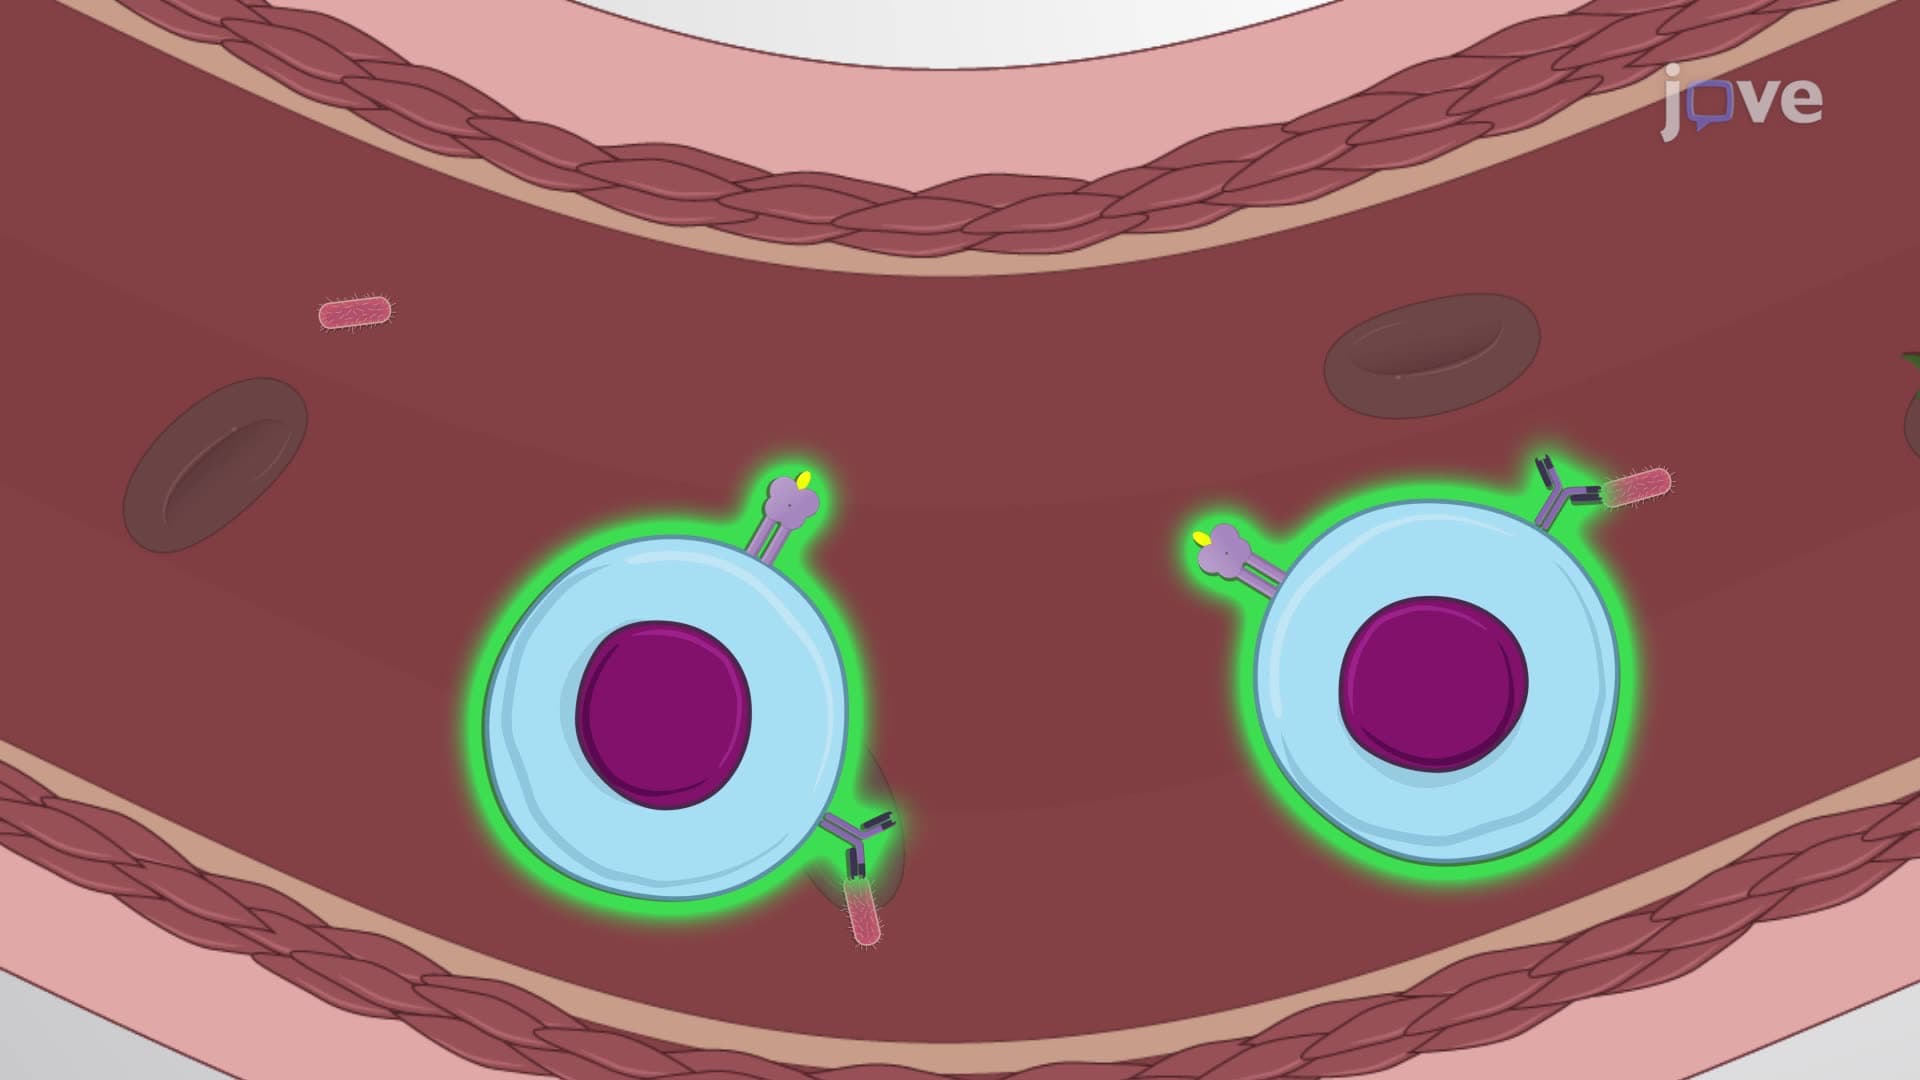
Cells of the Adaptive Immune Response
 01:22
T Cell Activation and Clonal Selection
Naive T cells that have not yet encountered an antigen express two primary CD...
 01:24
T Cell Types and Functions
Th1 cells stimulate dendritic cells to express necessary co-stimulatory molecules on their surfaces for...
 01:24
B Cell Activation and Differentiation
When naive B cells encounter a specific antigen that can bind to the B cell receptor (BCR) on their surface, they undergo sensitization to respond to the antigen's presence. Sensitization begins with...