Related Experiment Video
Updated: Jul 16, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
A comparison of calcium, vitamin D, or both for nutritional rickets in Nigerian children
T D Thacher1, P R Fischer, J M Pettifor
1Department of Family Medicine, Jos University Teaching Hospital, Nigeria.

Background:
Nutritional rickets remains prevalent in many tropical countries despite the fact that such countries have ample sunlight. Some postulate that a deficiency of dietary calcium, rather than vitamin D, is often responsible for rickets after infancy.
Methods:
We enrolled 123 Nigerian children (median age, 46 months) with rickets in a randomized, double-blind, controlled trial of 24 weeks of treatment with vitamin D (600,000 U intramuscularly at enrollment and at 12 weeks), calcium (1000 mg daily), or a combination of vitamin D and calcium. We compared the calcium intake of the children at enrollment with that of control children without rickets who were matched for sex, age, and weight. We measured serum calcium and alkaline phosphatase and used a 10-point radiographic score to assess the response to treatment at 24 weeks.
Results:
The daily dietary calcium intake was low in the children with rickets and the control children (median, 203 mg and 196 mg, respectively; P=0.64). Treatment produced a smaller increase in the mean (+/-SD) serum calcium concentration in the vitamin D group (from 7.8+/-0.8 mg per deciliter [2.0+/-0.2 mmol per liter] at base line to 8.3+/-0.7 mg per deciliter [2.1+/-0.2 mmol per liter] at 24 weeks) than in the calcium group (from 7.5+/-0.8 [1.9+/-0.2 mmol per liter] to 9.0+/-0.6 mg per deciliter [2.2+/-0.2 mmol per liter], P<0.001) or the combination-therapy group (from 7.7+/-1.0 [1.9+/-0.25 mmol per liter] to 9.1+/-0.6 mg per deciliter [2.3+/-0.2 mmol per liter], P<0.001). A greater proportion of children in the calcium and combination-therapy groups than in the vitamin D group reached the combined end point of a serum alkaline phosphatase concentration of 350 U per liter or less and radiographic evidence of nearly complete healing of rickets (61 percent, 58 percent, and 19 percent, respectively; P<0.001).
Conclusions:
Nigerian children with rickets have a low intake of calcium and have a better response to treatment with calcium alone or in combination with vitamin D than to treatment with vitamin D alone.
Related Concept Videos
 01:33
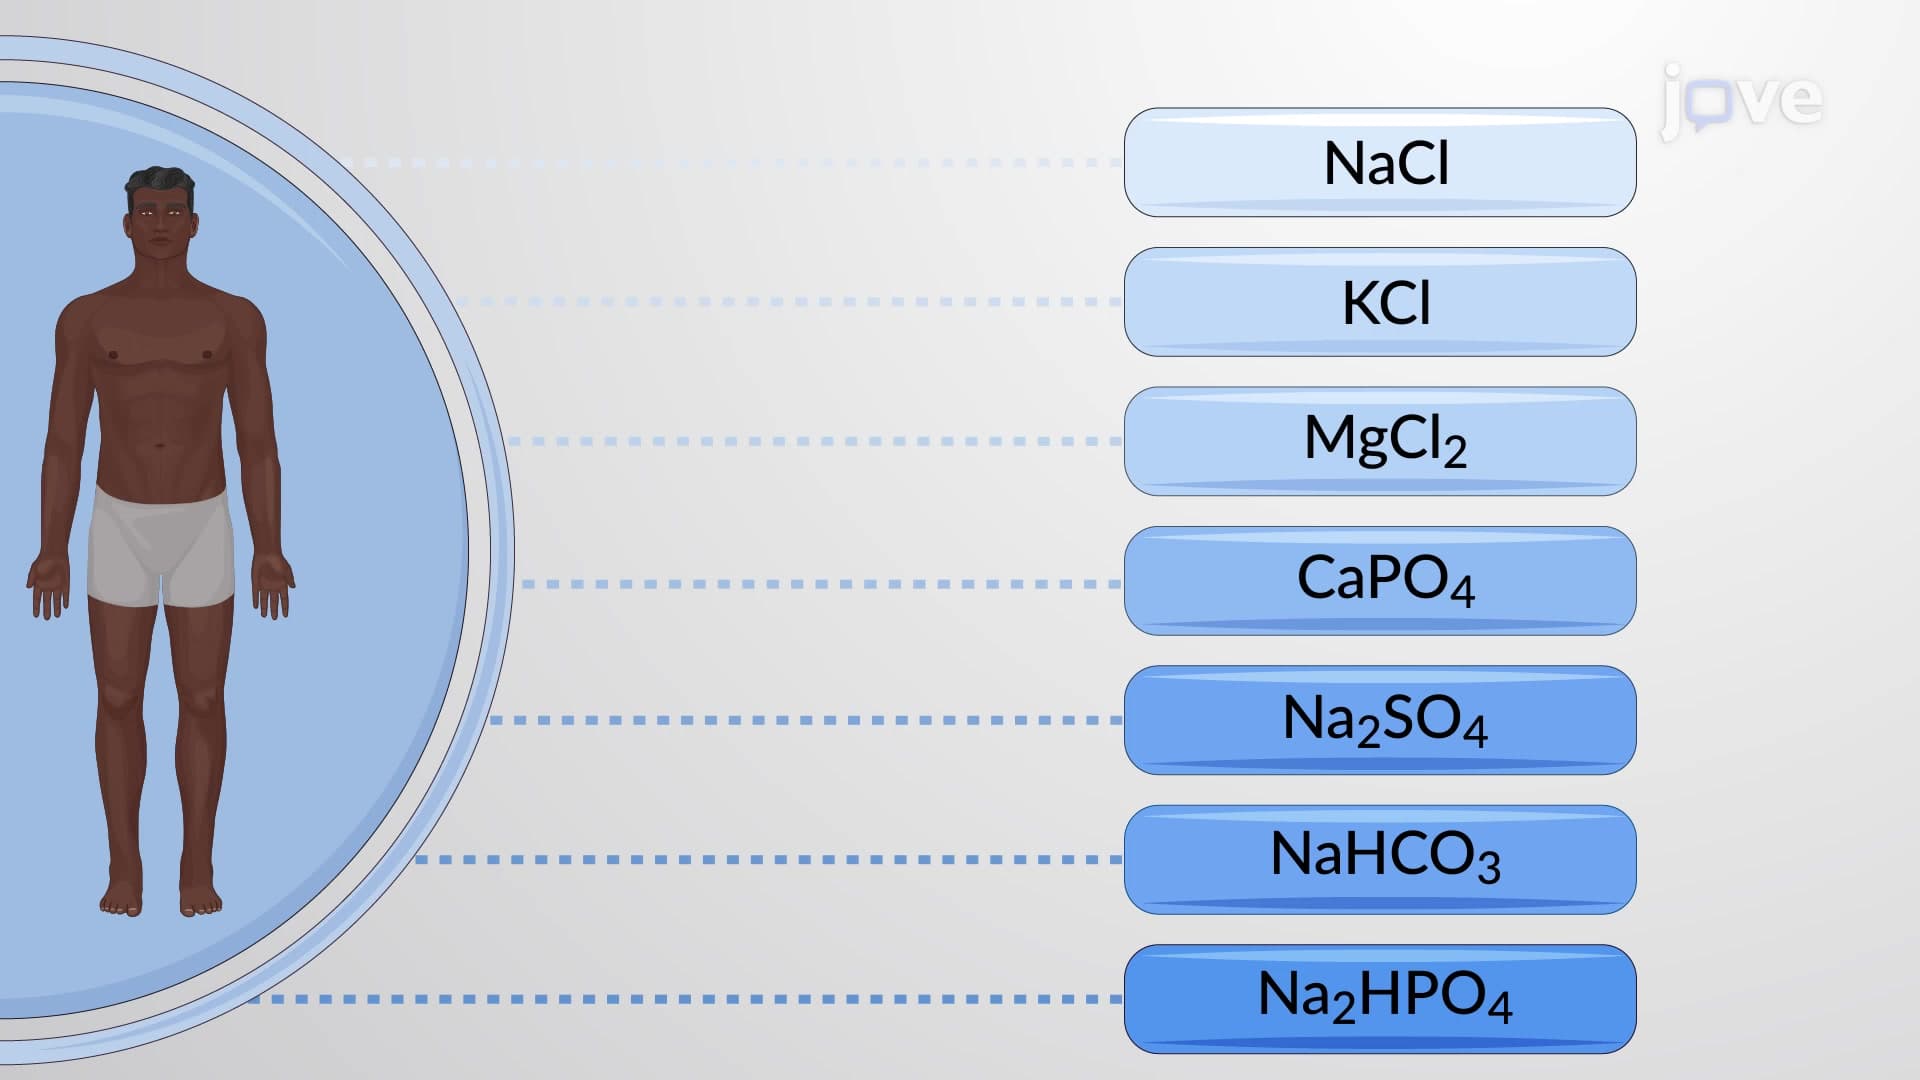
Introduction to Electrolytes
Role of Sodium
One...
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin D3(cholecalciferol).
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:21
Skeleton and Calcium Homeostasis
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:30
Vitamins