Generalized lupus panniculitis and antiphospholipid syndrome in a patient without complement deficiency

H C Nousari1, A Kimyai-Asadi, H M Santana

  • 1Department of Dermatology, Johns Hopkins Medical Institutions, Baltimore, Maryland 21205, USA. hnousari@welchlinkwelch.jhu.edu

Pediatric Dermatology
|September 1, 1999
PubMed

Related Concept Videos

Complement System01:27

Complement System

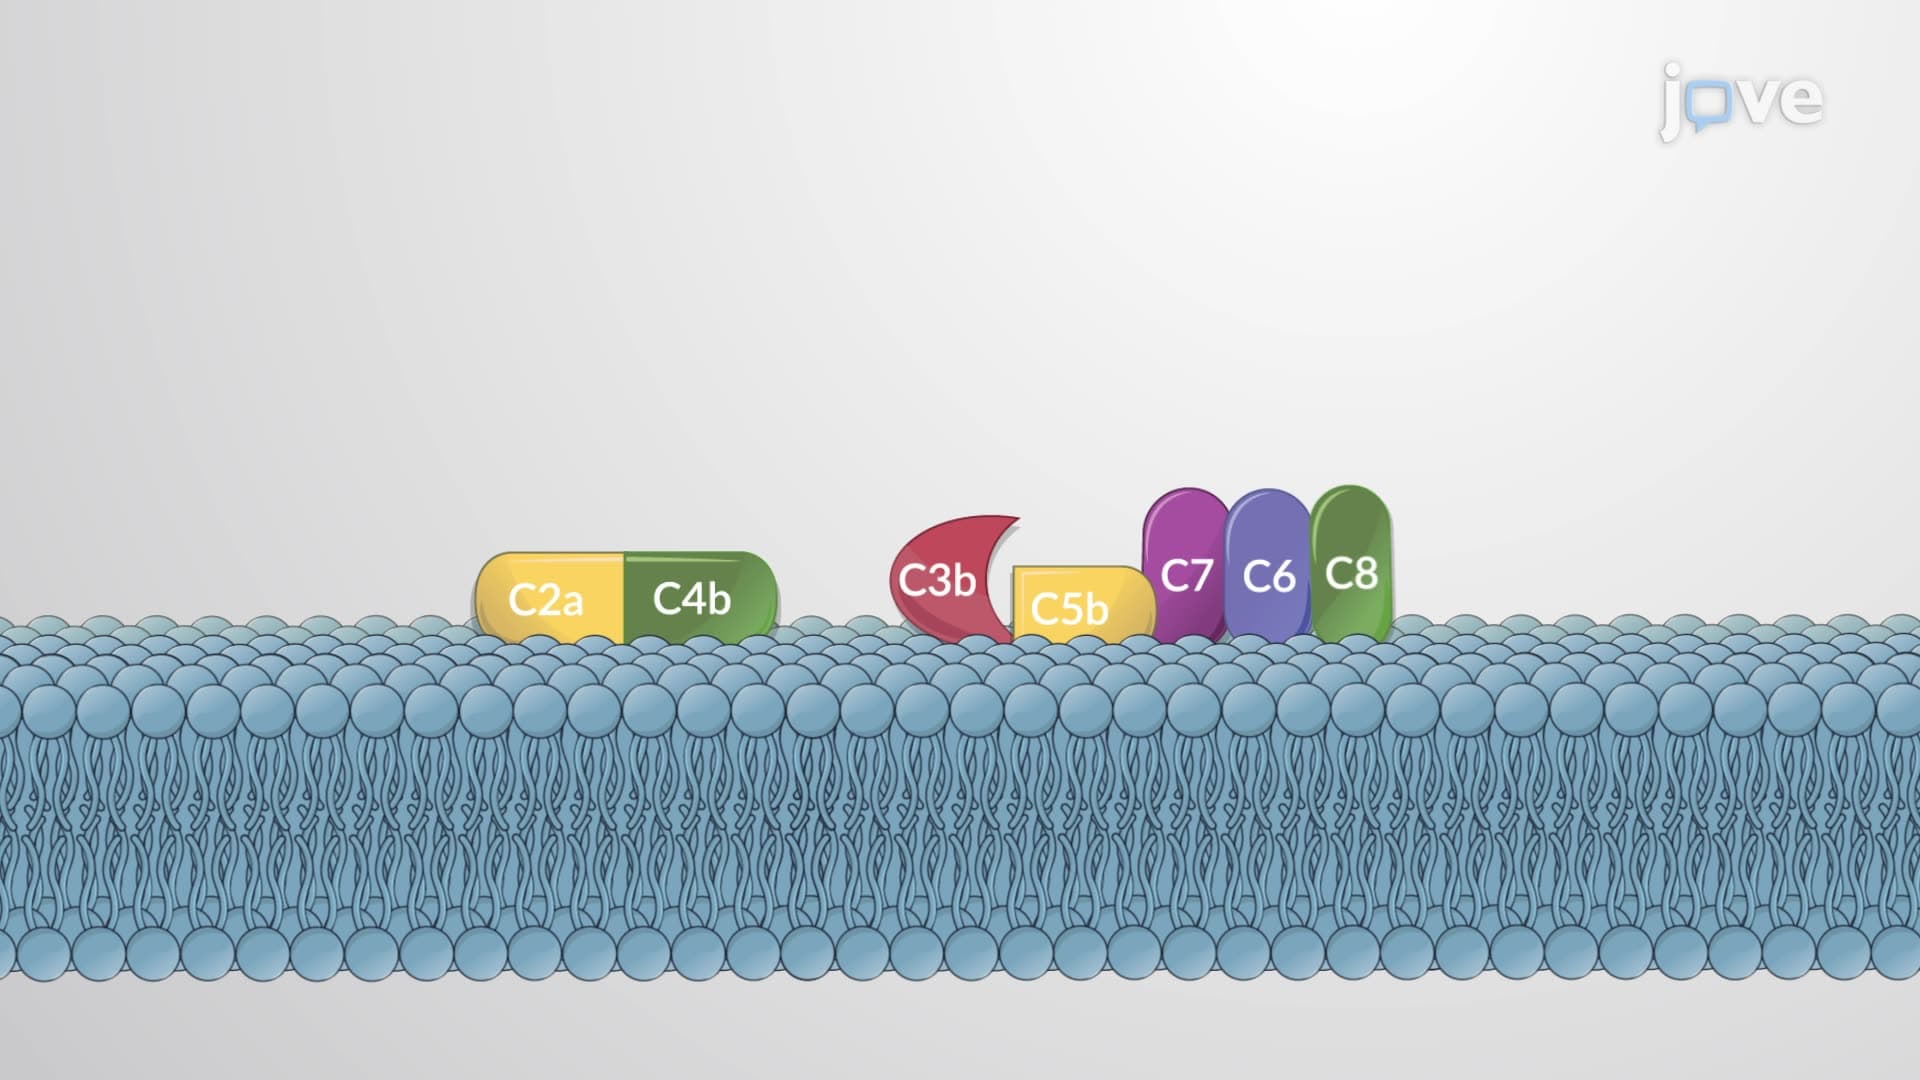
The complement system is a group of approximately 20 plasma proteins that strengthen the body's defenses against infections through opsonization, inflammation, and cell lysis. Opsonization involves coating pathogens with complement proteins, making them more recognizable and facilitating phagocyte engulfment. Certain complement proteins induce inflammation that attracts immune cells to the site of infection. Cell lysis involves the destruction of pathogens through the formation of a membrane...
Peripheral Artery Disease I: Introduction01:30

Peripheral Artery Disease I: Introduction
Peripheral artery disease (PAD) predominantly results from atherosclerosis, which involves the accumulation of fatty deposits, or plaques, within the walls of arteries. This causes them to narrow and harden, significantly reducing blood flow. PAD predominantly affects the legs, particularly the arteries supplying the thighs and calves. In rare cases, it may involve other arteries, including those in the arms.Etiology of PAD:The principal cause of PAD is atherosclerosis, which results from fatty...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

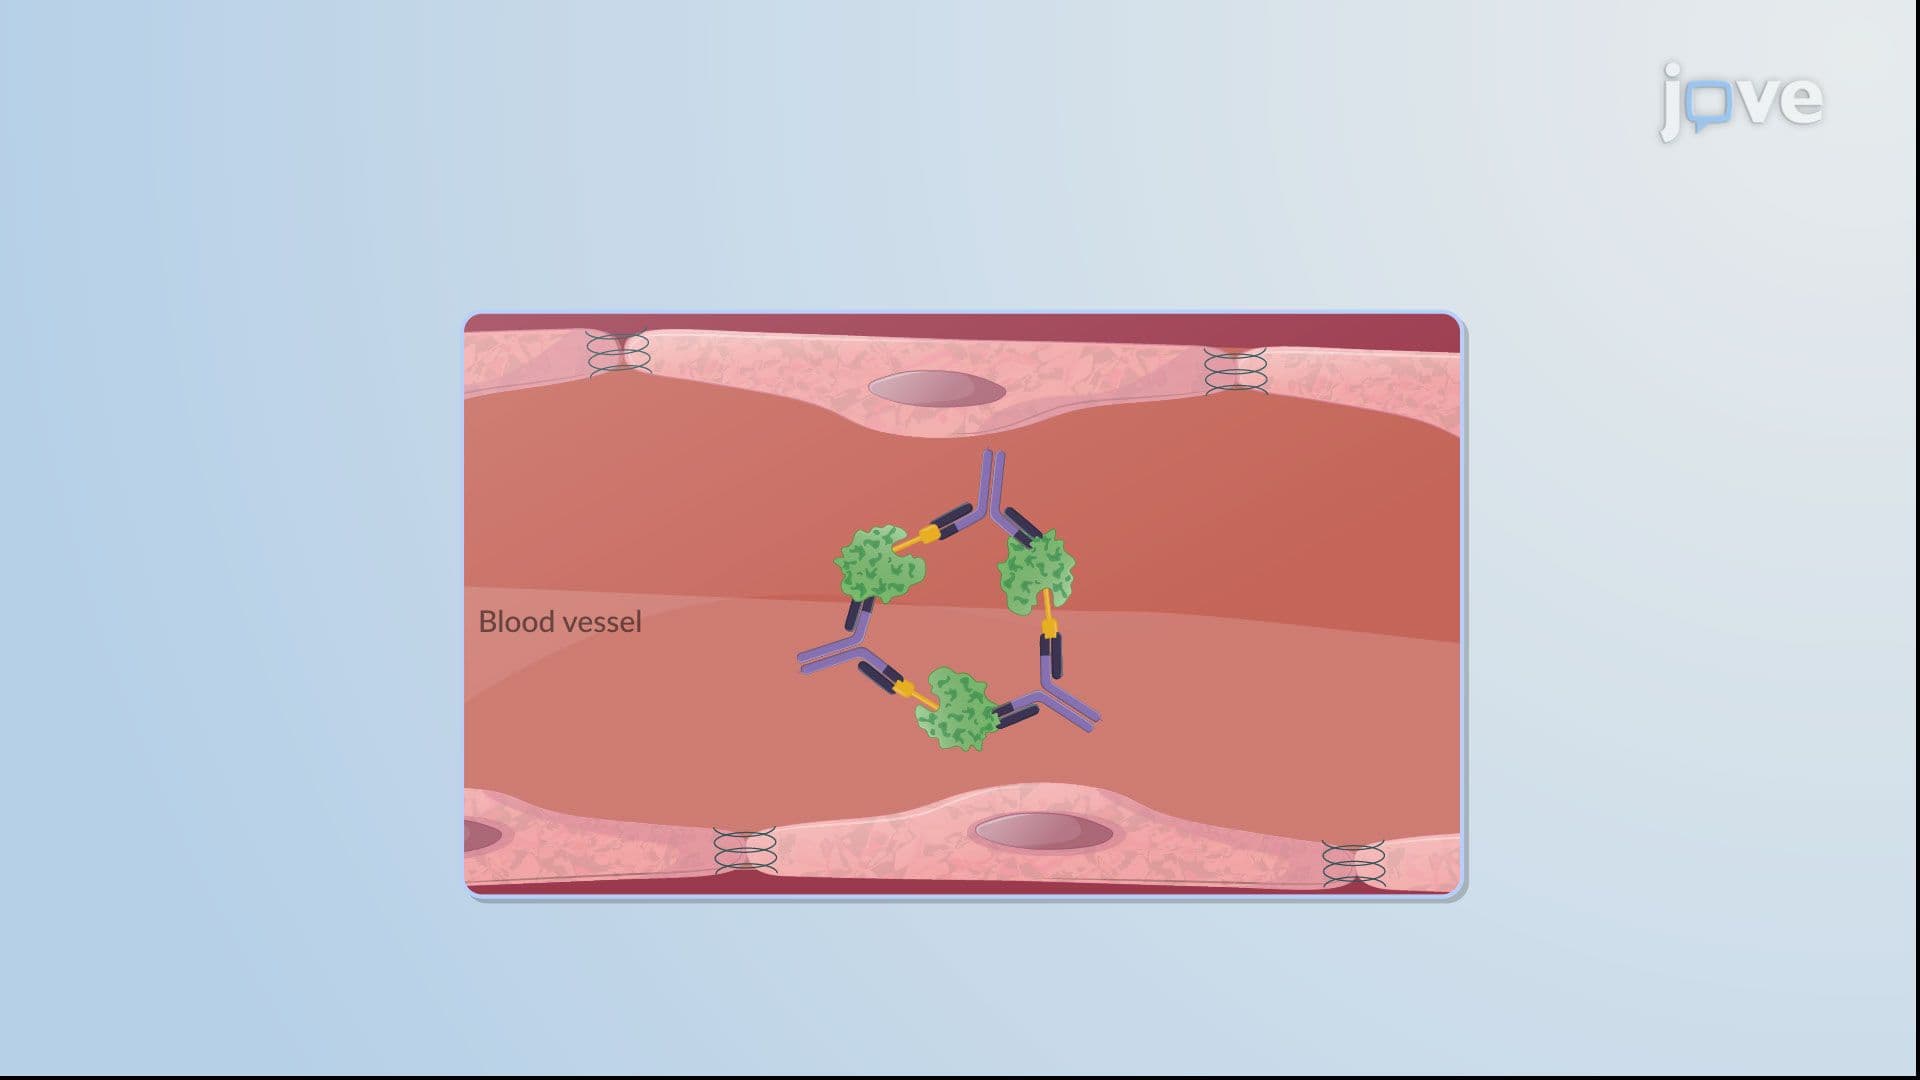
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation01:21

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation

Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
Endocarditis II: Clinical Features of Infective Endocarditis01:25

Endocarditis II: Clinical Features of Infective Endocarditis

Endocarditis can present various clinical features depending on the causative organism and the patient's underlying health conditions. Initially, the clinical features of infective endocarditis develop gradually, presenting with nonspecific symptoms that can be easily mistaken for other illnesses.General SymptomsEarly symptoms of infective endocarditis are fever, chills, weakness, malaise, fatigue, and weight loss. These symptoms reflect the systemic nature of the infection and the body's...
Nephrotic Syndrome I : Introduction01:24

Nephrotic Syndrome I : Introduction

Nephrotic Syndrome is a chronic kidney disorder defined by clinical findings such as severe proteinuria, hypoalbuminemia, hyperlipidemia, and edema. These symptoms result from damage to the glomeruli, the kidney’s filtering units, increasing their permeability to proteins.Definition and Meaning:Proteinuria, defined as the loss of more than 3.5 grams of protein per day in adults, is a crucial feature of nephrotic syndrome. This condition is often accompanied by edema, the accumulation of fluid...