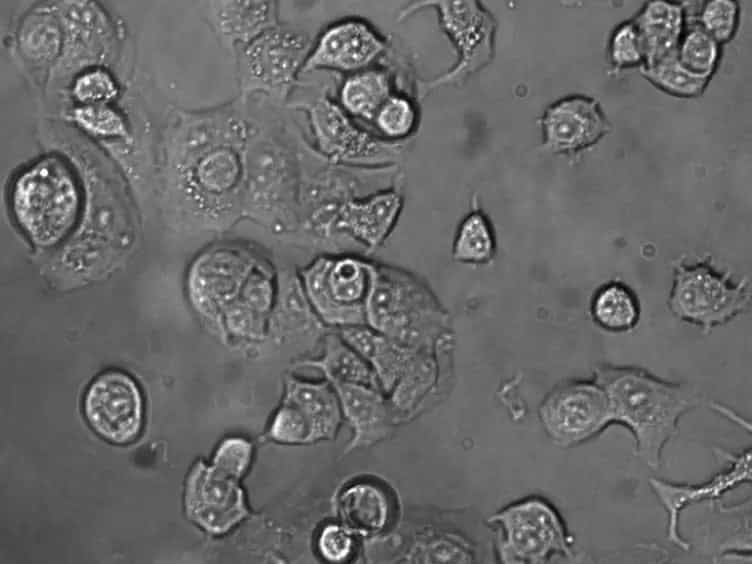

Aspirin induced apoptosis in gastric cancer cells
1Department of Medicine, University of Hong Kong, Queen Mary Hospital, China.

Abstract:
Aspirin has been well known for its anti-pyretic and anti-inflammatory action over the past century. Its main action in the gastro-intestinal tract has always been associated with erosion and ulceration. However in recent years, there has been evidence suggesting that aspirin and the more potent non-steroidal anti-inflammatory drugs (NSAIDs), could reduce the risk of gastric and colon cancer. One of the possible mechanisms in chemo-prevention is the ability to induce apoptosis in epithelial cells of the gastro-intestinal origin. This article introduces the role of apoptosis in the body and the gastro-intestinal tract. Evidence on the chemo-preventive role of aspirin and NSAIDs are listed, and the mechanisms of action discussed.
More Related Videos
 13:38
Synthesis and Characterization of an Aspirin-fumarate Prodrug that Inhibits NFκB Activity and Breast Cancer Stem Cells
Published on: January 18, 2017
 06:21
Multi-Gene Single Nucleotide Polymorphism Detection in Gastric Cancer Based on Ion Semiconductor Sequencing Platform
Published on: May 10, 2024
Related Concept Videos
 01:31
The Intrinsic Apoptotic Pathway
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:24
Peptic Ulcer Disease II: Pathophysiology