Related Experiment Video
Updated: Aug 10, 2026


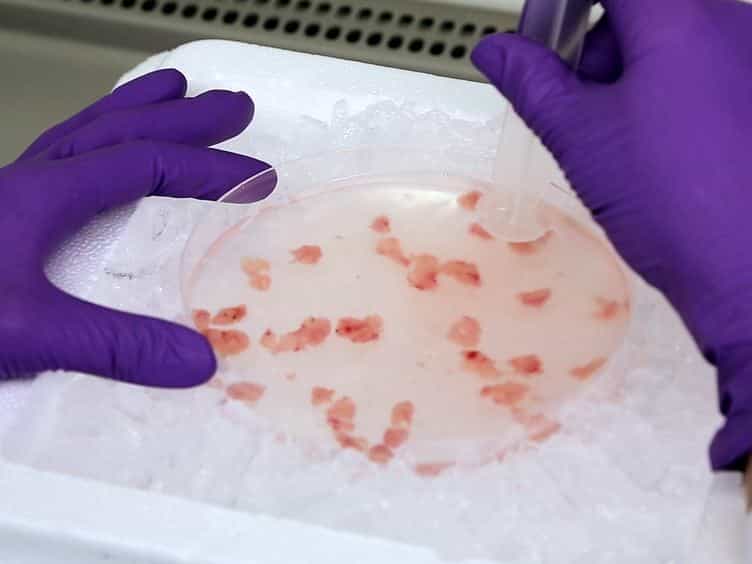
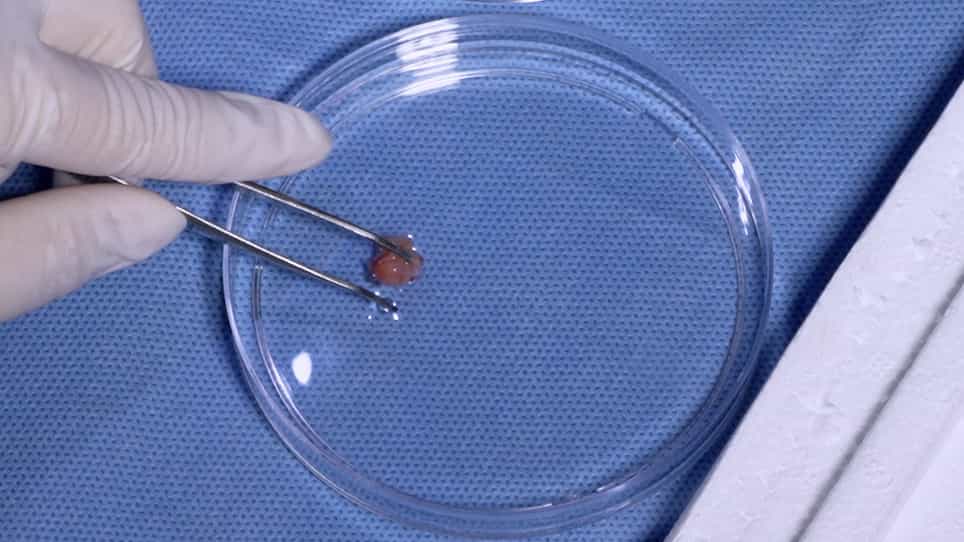
Derivation of Thymic Lymphoma T-cell Lines from Atm-/- and p53-/- Mice
Published on: April 3, 2011
Thymic tumours in Denmark. A retrospective study of 213 cases from 1970-1993
P Engel1, A Marx, H K Müller-Hermelink
1Department of Pathology, County Hospital Roskilde, Denmark.

Abstract:
Histological slides of 213 thymic tumours were reviewed twice and classified according to Kirchner and Müller-Hermelink into 122 thymomas (syn. organotypic thymic epithelial tumours (TET)), 58 thymic carcinomas (syn. non-organotypic TET) and 16 lymphomas. Tumour heterogeneity (i.e. features of two subtypes in one tumour) appeared in 38% of the organotypic TET. The overall diagnostic correspondence between the reviews of the 122 organotypic TET was 48%. By reducing the five diagnostic groups to three: organotypic TET benign (medullary and mixed thymomas), organotypic TET low-grade (organoid and cortical thymomas and well-differentiated thymic carcinoma (WDTC)) and non-organotypic TET (usually high-grade thymic carcinomas), and minimising the effect of tumour heterogeneity in this way, the diagnostic correspondence increased to 82%. Correlating histological type with stage, we found that 80% of medullary and 87% of mixed thymomas were stage I, that 85% of cortical and 81% of WDTC were stage II or III, and that non-organotypic TET were stage II or III (86%) or stage IV (14%), respectively. It is suggested to report on the heterogeneity of a given case of thymic epithelial tumour in the pathology reports and give the approximate percentage of each component, telling the clinician which component may determine the prognosis.