Related Experiment Video
Updated: Oct 19, 2026

Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
Bi-directional cavopulmonary shunt: is accessory pulsatile flow, good or bad?
H J van de Wal1, R Ouknine, D Tamisier
1Department of Thoracic and Cardiovascular surgery, Laennec Hospital, Paris, France. vandewal@wxs.nl

Objective:
Evaluation of the effect and long-term outcome of accessory pulsatile blood flow versus classical bi-directional cavopulmonary connection (BCPC).
Methods:
Retrospective review of the medical and surgical records.
Results:
Two-hundred and five patients (119 boys, 86 girls) underwent BCPC from 1990 to 1996. Accessory pulsatile flow was present in 68%, flow being maintained through the pulmonary trunc in 46%, systemic-to-pulmonary artery shunt in 13% and mixed in 7%, or patent ductus arteriosus in 2%. Patients with accessory pulsatile flow had lower hospital mortality (3% versus 5%), while mean pulmonary artery pressure (14.1 versus 12.6 mmHg P = 0.050) and increase of oxygen saturation (12.4 versus 8.7, P = 0.034) were significantly higher. The period of artificial ventilation (1.9 day) and ICU stay (6 days) did not differ for both groups. Late mortality was higher following accessory pulsatile flow (6% versus 1%). At late follow-up patients with accessory pulsatile flow had significantly higher oxygen saturation (mean 85 +/- 4%, versus 79 +/- 4%; P < or = 0.005). If subsequent completion of Fontan is considered the optimal palliation and subsequent systemic to pulmonary artery shunt, arteriovenous fistula and transplantation is considered a failure, patients with accessory pulsatile flow had significantly more and earlier completion of the Fontan procedure (mean 1.7 +/- 2.4 years, versus 2.7 +/- 4.4 years; P = 0.008). Survival is not influenced by age at bi-directional cavopulmonary shunt surgery, left or right functional ventricular anatomy or previous palliative surgery. One patient with accessory pulsatile flow developed systemic-to-pulmonary collateral's eventually requiring lobectomy.
Conclusion:
Despite two different initial palliative techniques the outcome was not significantly different. Accessory pulsatile blood flow appeared not to be a contra-indication for a completion Fontan procedure. Moreover, the data suggest that after accessory pulsatile flow can safely be performed, at late follow-up oxygen saturation is higher, while, significantly more and earlier completion of Fontan occurred. Age at bi-directional cavopulmonary shunt, basic left or right ventricular anatomy or previous palliative surgery did not influence survival.
Related Concept Videos
 01:19
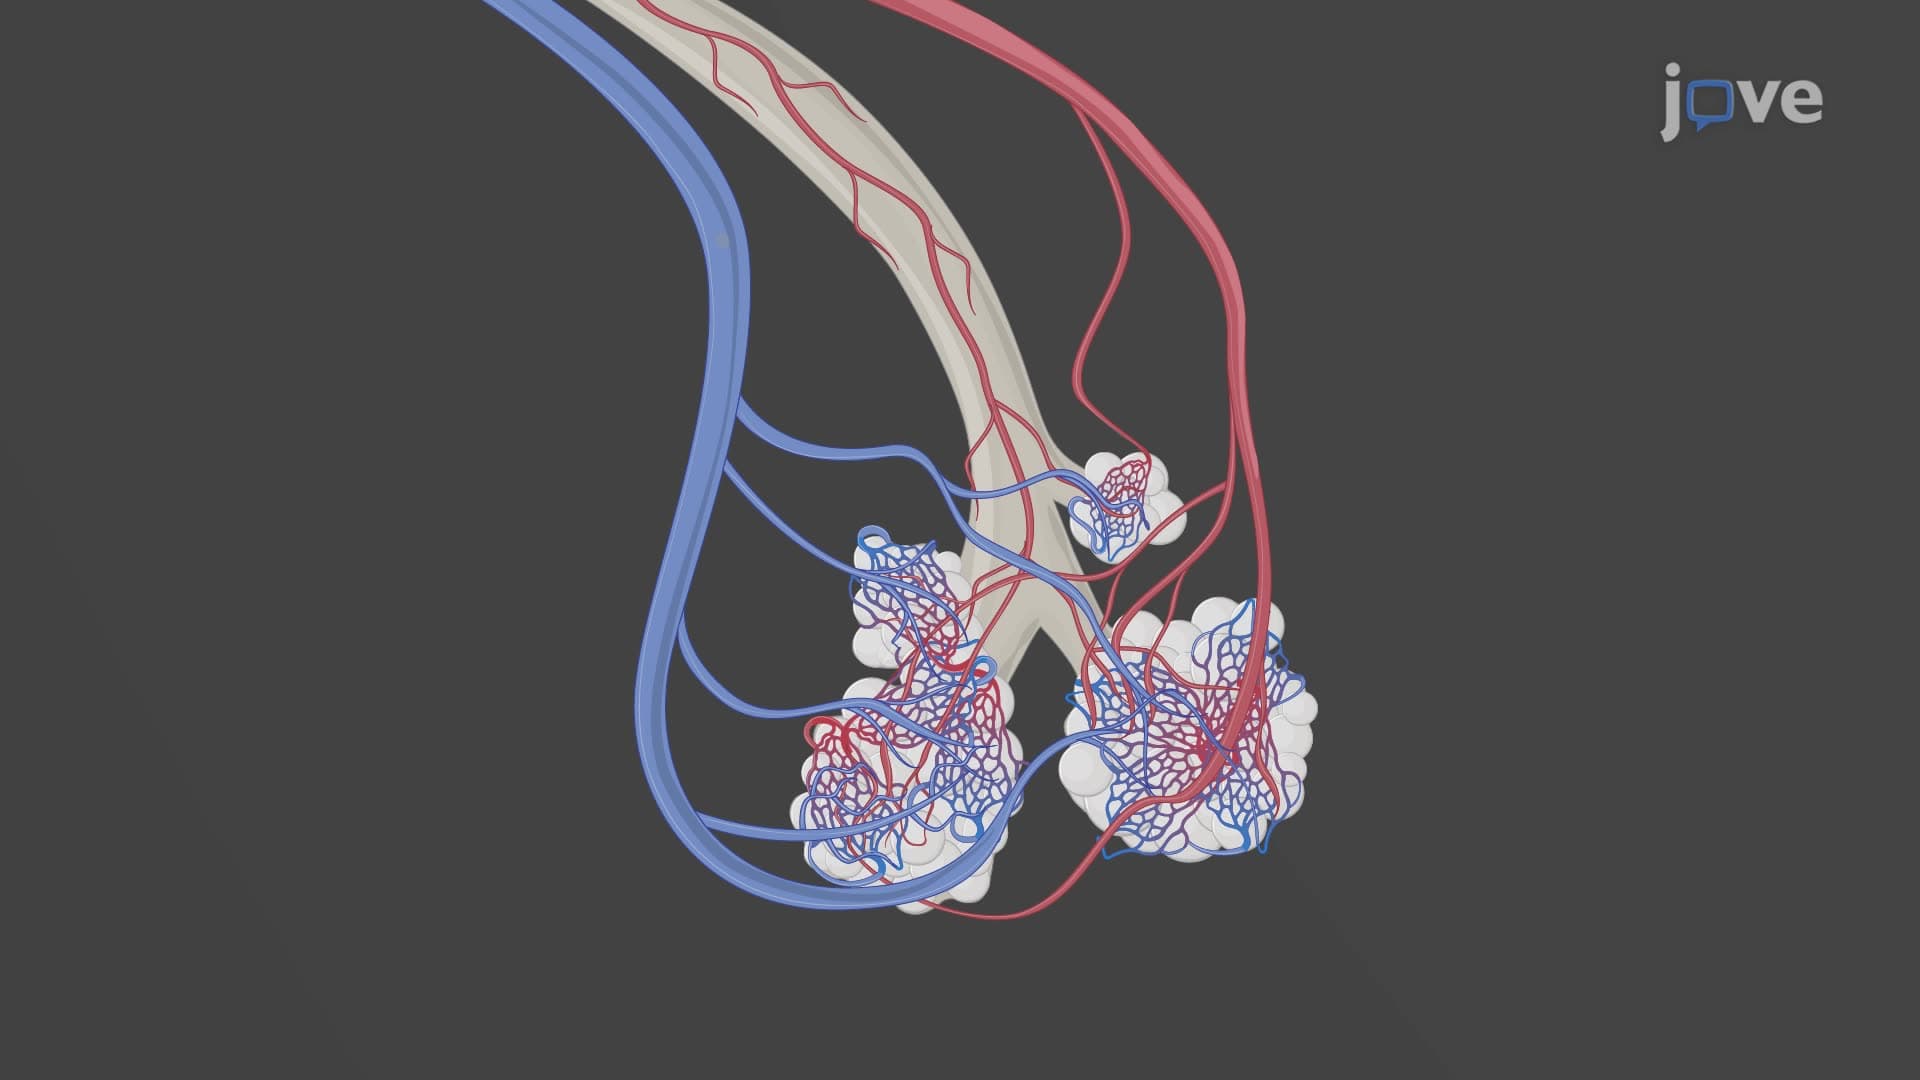
Overview of Pulmonary Circulation
The process begins with the right ventricle of the heart pumping deoxygenated blood into the pulmonary trunk. This large vessel extends about 5 centimeters before splitting into the left and right pulmonary arteries. These arteries...
 01:15
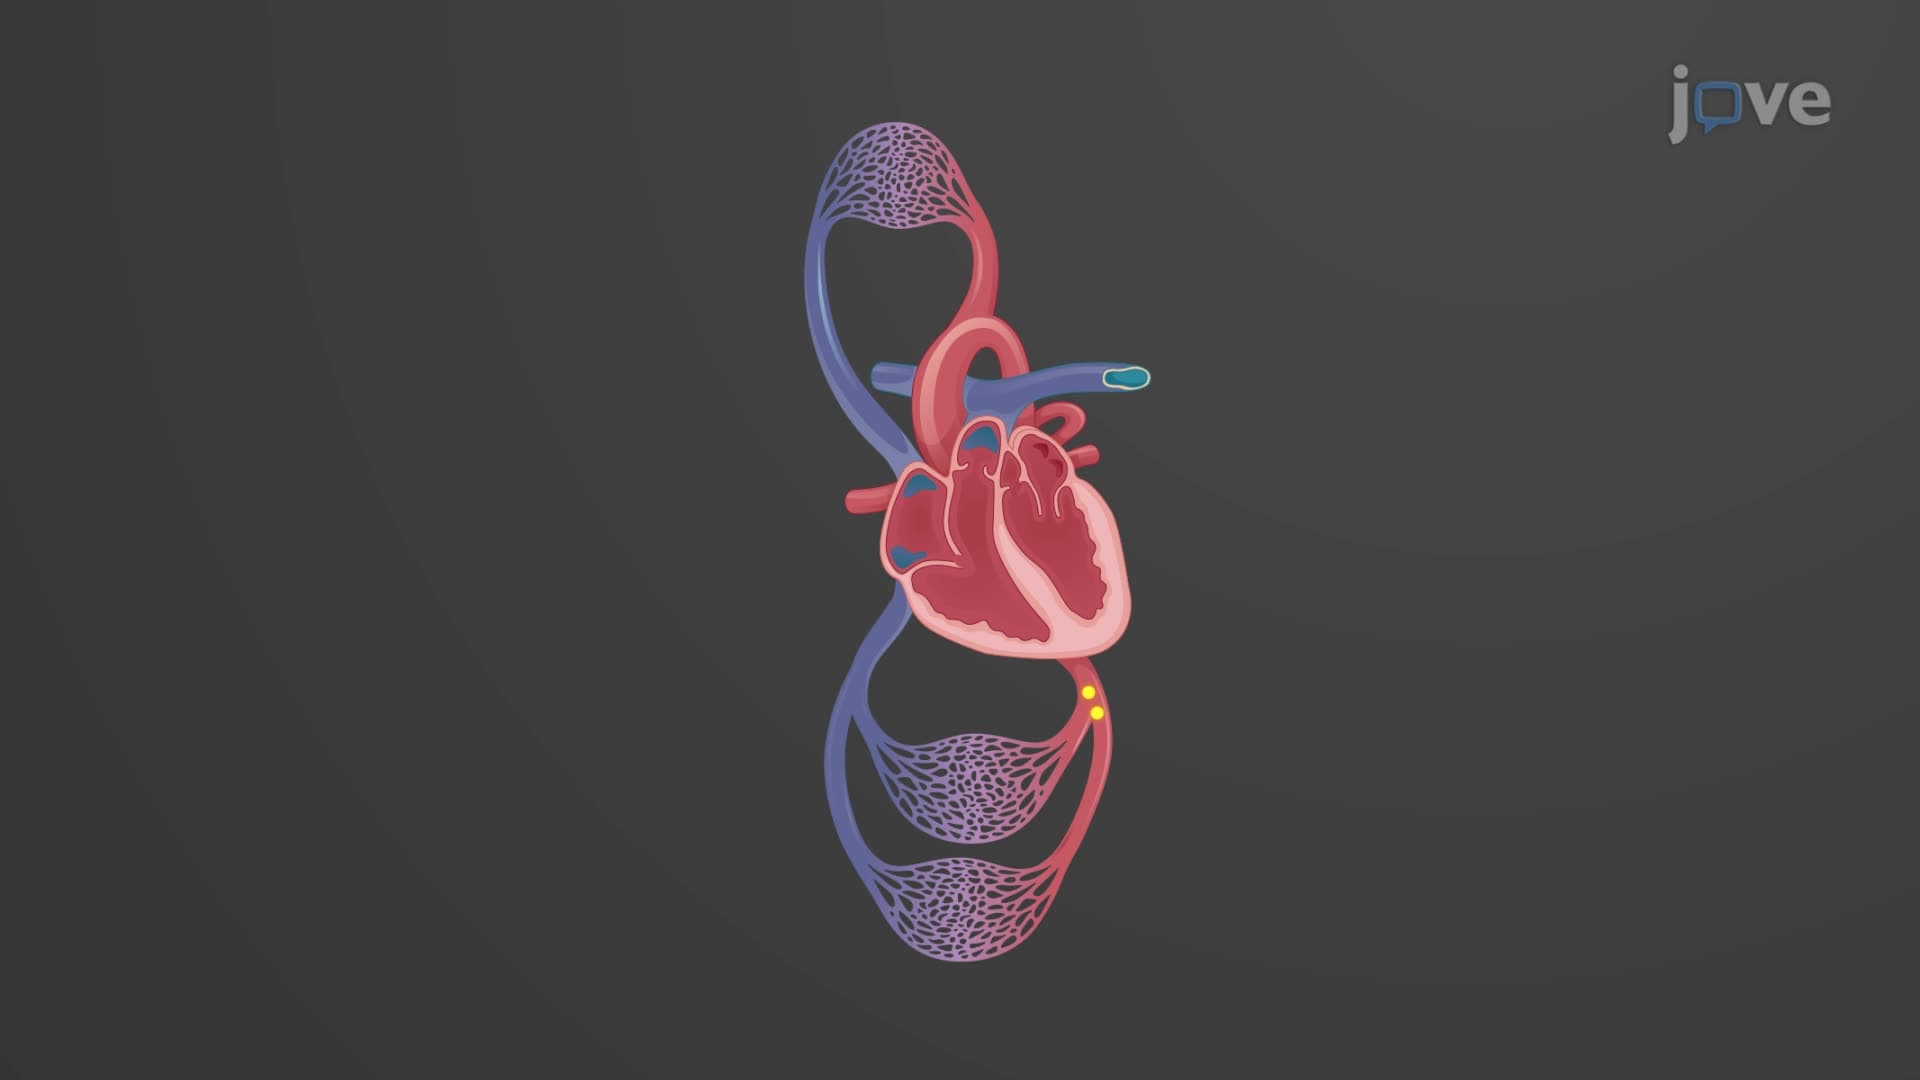
Overview of Systemic and Pulmonary Circulation
The oxygenated blood is sent...
 01:22
Mitral Stenosis I: Introduction
 01:15
Aortic Regurgitation I: Introduction
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...