Related Experiment Video
Updated: Aug 21, 2026

System for Efficacy and Cytotoxicity Screening of Inhibitors Targeting Intracellular Mycobacterium tuberculosis
Published on: April 5, 2017
Pharmacokinetic factors in the modern drug treatment of tuberculosis
1Department of Respiratory Medicine, Aberdeen Royal Infirmary, Scotland. j.g.douglas@arh.grampian.scot.nhs.uk

Abstract:
Tuberculosis is increasing in prevalence throughout the world, particularly in sub-Saharan Africa, Asia and Latin America. This resurgence can partly be attributed to increasing poverty, particularly in developing countries, and the human immunodeficiency virus (HIV) pandemic. However, there is also increasing concern at the development of multidrug-resistant tuberculosis caused by the misuse of the agents available. The modern treatment of patients with tuberculosis should start, in most cases, with 4 first-line agents in order to minimise the risk of drug resistance developing. A6-month drug regimen is usually satisfactory for pulmonary and nonpulmonary tuberculosis, although not for patients with tuberculous meningitis, in whom a longer course of treatment is required. Coinfection with HIV may produce an atypical clinical and radiological presentation, but the treatment regimen is essentially similar to other situations. Several of the first-line agents, in particular rifampicin (rifampin) and isoniazid, are likely to cause clinically significant drug interactions and/or toxicity, particularly in patients with HIV infection. Consideration of the pharmacodynamic and pharmacokinetic interactions between the host, the mycobacterium and the drug may contribute to the development of pharmacokinetically optimised regimens that make best use of the existing range of antituberculosis drugs. However, such idealised regimens need to be tested in prospective clinical trials. The use of therapeutic drug monitoring in selected groups of patients may improve outcomes, avoid drug toxicity and reduce the development of multidrug-resistant tuberculosis. The management of multidrug-resistant tuberculosis requires a high level of clinical expertise and such patients should start on at least 5 drugs to which the organism is thought to be susceptible. Up to 50% of patients with tuberculosis may not adhere to their drug regimen, resulting in persisting infectiousness, relapse or the development of drug resistance. Directly observed treatment with antituberculosis drugs, combined with a serious commitment to tuberculosis control, is required if we are to combat this increasing epidemic.
More Related Videos
 10:29
A High-throughput Compatible Assay to Evaluate Drug Efficacy against Macrophage Passaged Mycobacterium tuberculosis
Published on: March 24, 2017
 10:24
Identification of Potential Anti-TB Candidates: A Step-by-Step Guide to Synthesis, MIC Determination, and Cytotoxicity Assessment in Mammalian Cells
Published on: May 22, 2026
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:29
Therapeutic Drug Monitoring: Affecting Factors
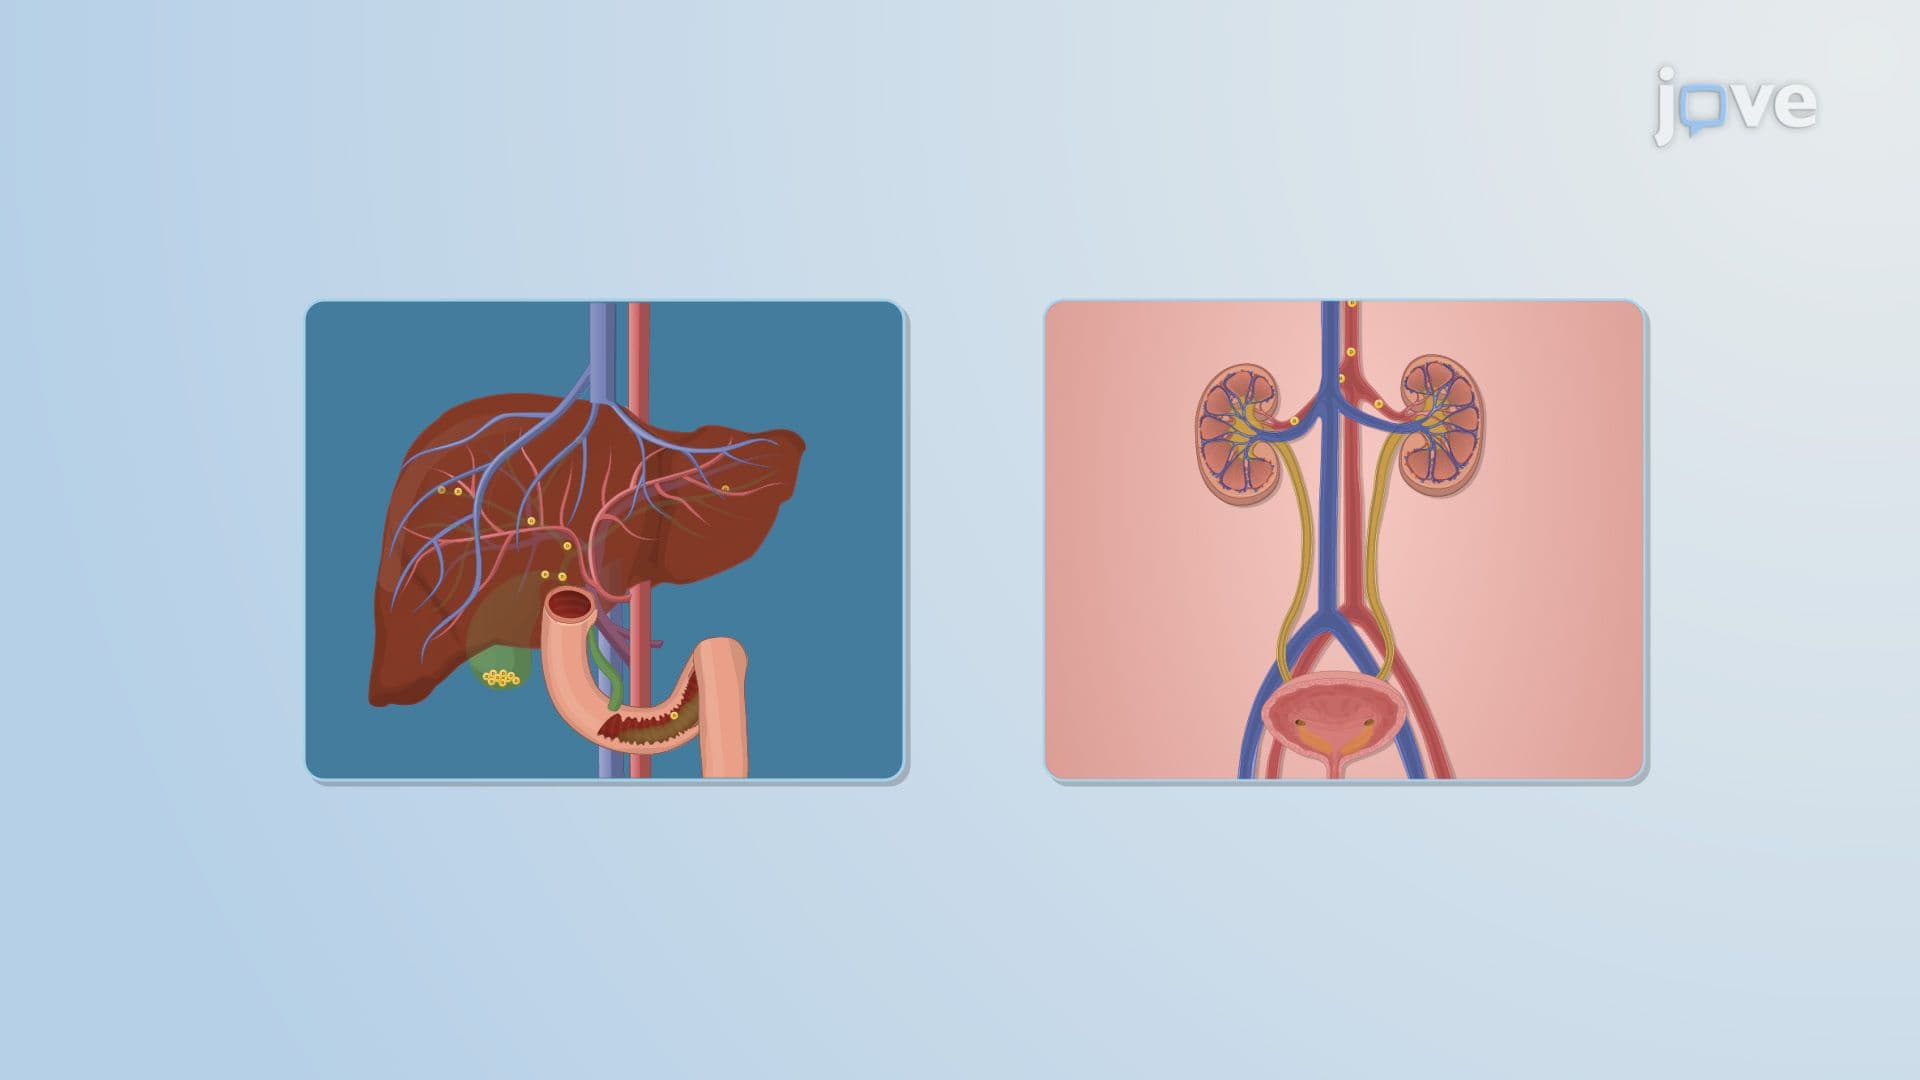 01:23
Pharmacokinetic–Pharmacodynamic Relationship: Influence of Elimination Half-Life on Effect Duration
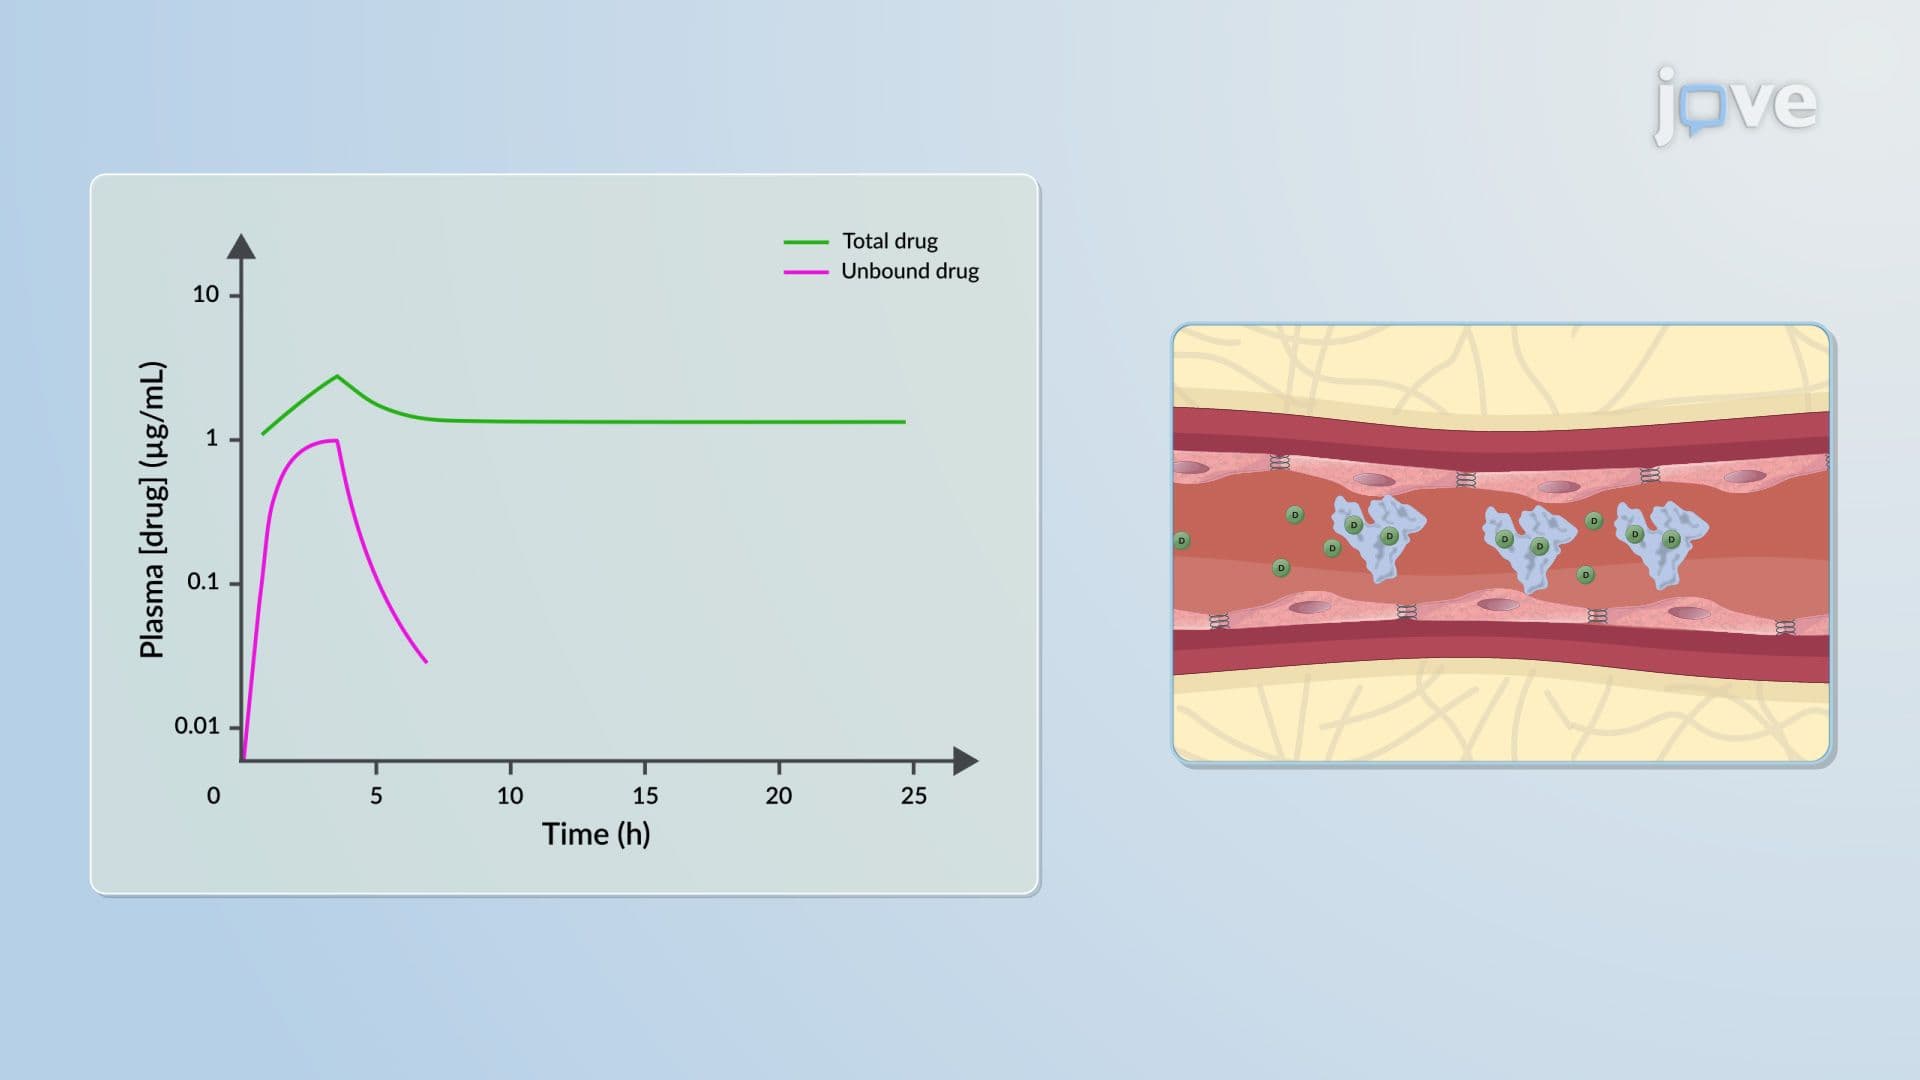 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems