Related Experiment Video
Updated: Oct 19, 2026

Transuterine Fetal Tracheal Occlusion Model in Mice
Published on: February 5, 2021
[Congenital oesophageal stenosis due to tracheobronchial remnants]
W Pumberger1, W Geissler, E Horcher
1Klinische Abteilung für Kinderchirurgie der Universität Wien.

Insights
Congenital esophageal stenosis (CES) caused by tracheobronchial remnants can be successfully treated with surgical resection and anastomosis. Early diagnosis is key when other esophageal conditions are ruled out.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Thoracic Surgery
Context:
- Congenital esophageal stenosis (CES) is a rare condition.
- Tracheobronchial remnants are an uncommon cause of CES.
- Feeding difficulties in infants can indicate esophageal issues.
Purpose:
- To present the authors' experience with CES due to tracheobronchial remnants.
- To highlight the diagnostic criteria and successful surgical management of CES.
- To emphasize the importance of considering CES in infants with feeding problems.
Summary:
- Three pediatric patients with CES caused by tracheobronchial remnants underwent limited resection and primary anastomosis.
- Surgical intervention yielded good clinical outcomes for all patients.
- Diagnostic workup included contrast studies, endoscopy, pH monitoring, and manometry.
Impact:
- This study contributes to understanding CES management.
- Successful surgical outcomes suggest this approach is effective.
- Highlights the importance of early diagnosis and intervention for CES.
Abstract:
This paper presents the authors' experience with congenital oesophageal stenosis (= CES) in three patients who had CES due to tracheobronchial remnants. Difficulties with feeding started at 6-9 months of age, which corresponded with the introduction of solids. Contrast studies showed stenosis at the junction of the mid and distal thirds of the oesophagus. Limited resection of the oesophageal stenosis and primary anastomosis was performed in all three patients with good results. CES should be suspected if all other causes of oesophageal stenosis have been excluded by upper gastrointestinal examinations, endoscopy, oesophageal pH monitoring and oesophageal manometry.

Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
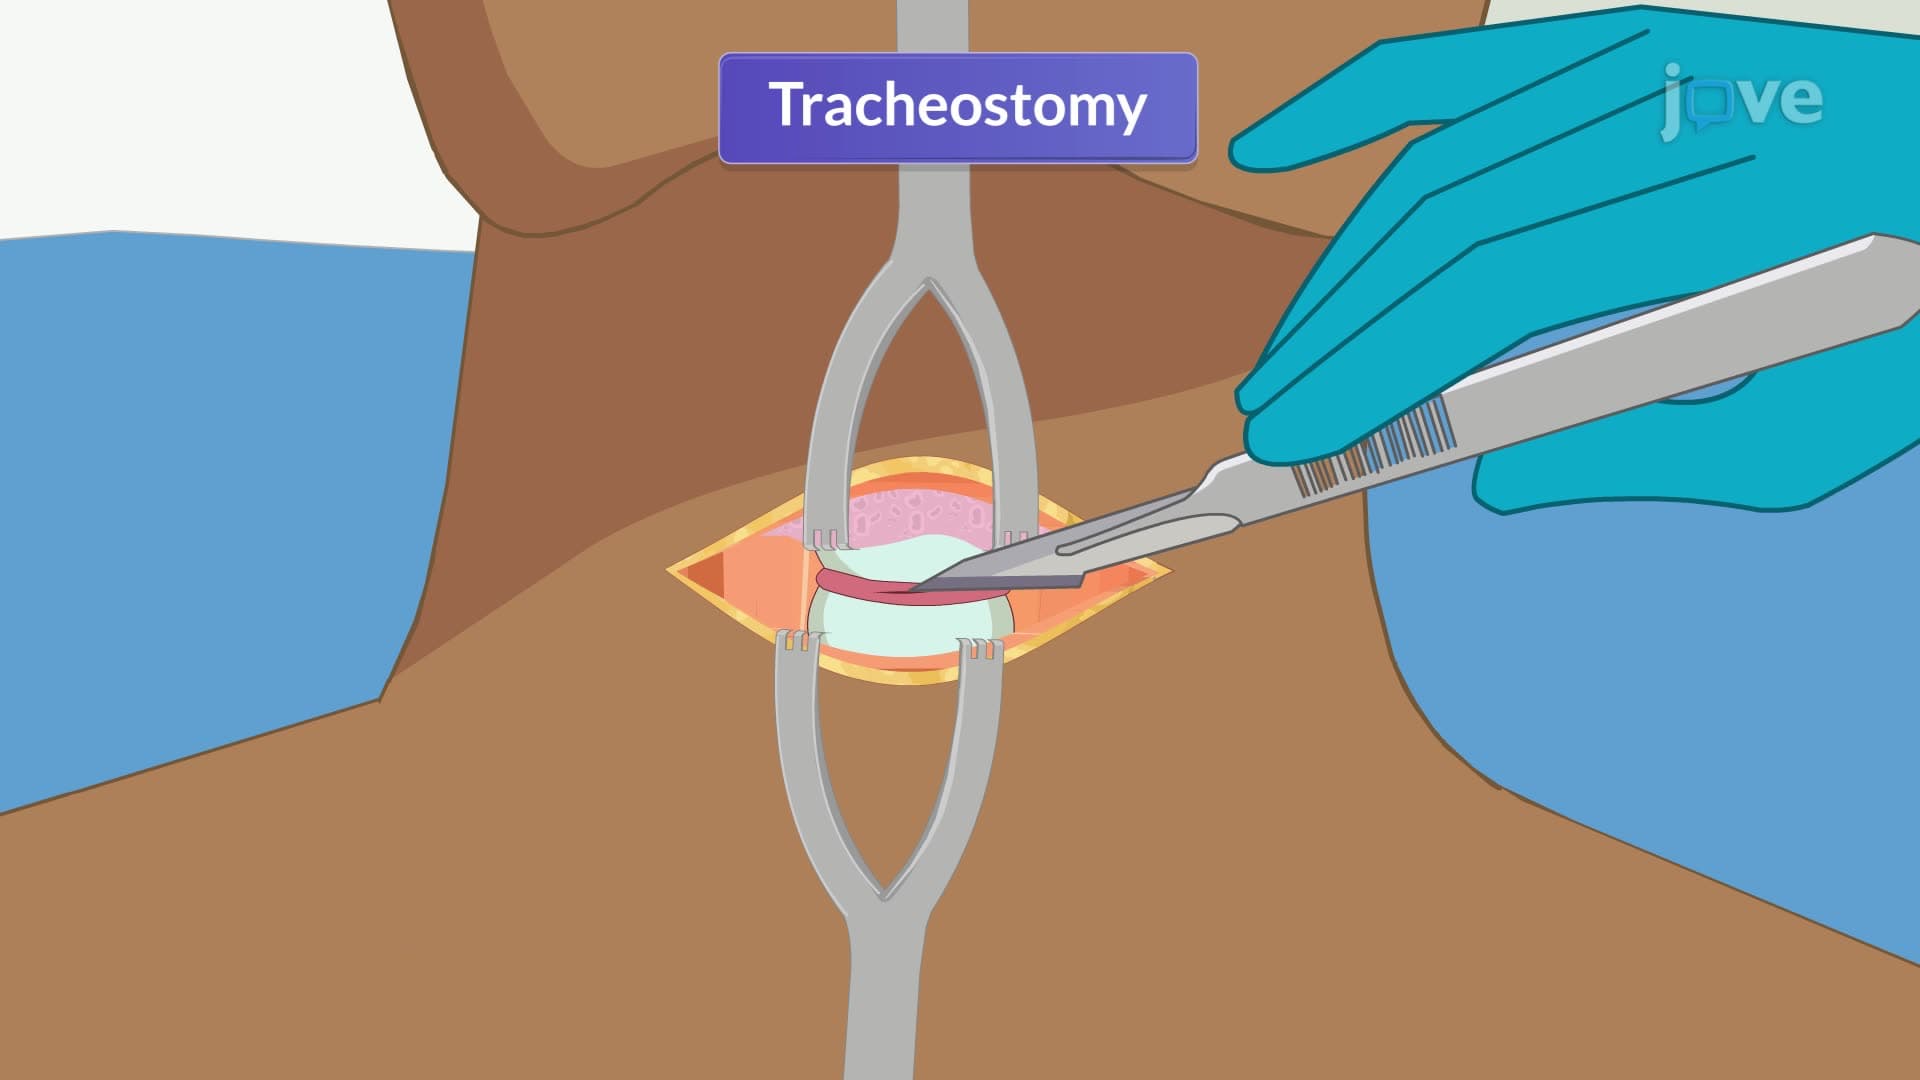
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...