Atypical phenotype of charcot-marie-tooth disease type 1A

T Murakami1, H Oomori, A Hara

  • 1Department of Neurology, Kumamoto University School of Medicine, Honjo 1-1-1, Kumamoto 860-0811, Japan. tmurakami@mail.kuh.kumamoto-u.ac.jp

Muscle & Nerve
|October 8, 1999
PubMed

Related Concept Videos

Myasthenia Gravis ll: Pathophysiology01:22

Myasthenia Gravis ll: Pathophysiology

The disease process of myasthenia gravis begins at the neuromuscular junction, where antibodies attack key proteins needed for muscle activation. This immune reaction weakens signal transmission, leading to the characteristic muscle fatigue and weakness that define the condition.Immune-Mediated DamageIn most individuals, antibodies target acetylcholine receptors (AChRs) on the postsynaptic membrane of muscle cells. By blocking acetylcholine binding, these antibodies prevent the nerve signal...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Huntington Disease l: Introduction01:21

Huntington Disease l: Introduction

Huntington disease or HD is a progressive, fatal neurodegenerative disorder inherited in an autosomal dominant pattern.PathophysiologyIt is caused by expansion of the CAG trinucleotide repeat in the HTT gene on chromosome 4 (4p16.3), producing an abnormal huntingtin protein with an expanded polyglutamine tract. This misfolded protein disrupts cellular function, leading to neuronal death. Normal alleles have ≤26 repeats, 27–35 are intermediate (risk of expansion), 36–39 show reduced penetrance,...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Alzheimer Disease ll: Pathophysiology01:23

Alzheimer Disease ll: Pathophysiology
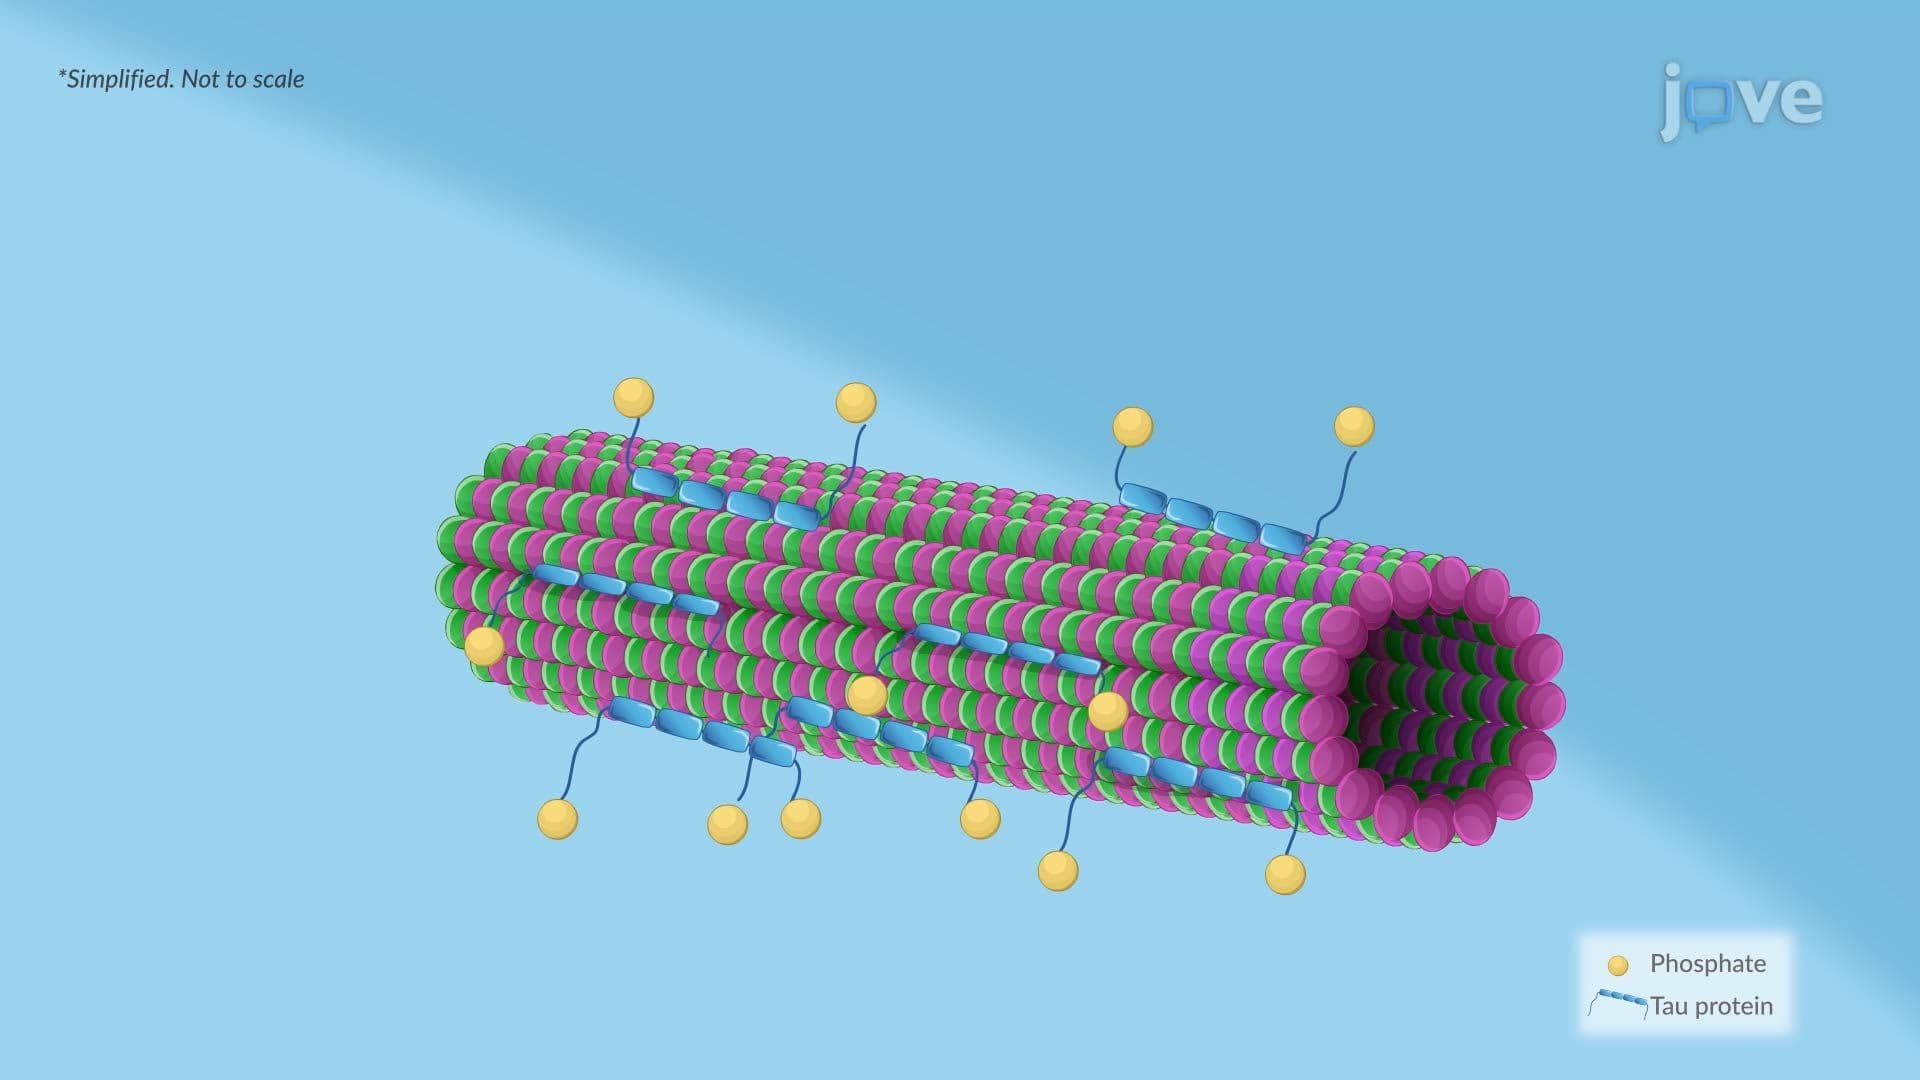
Alzheimer disease involves structural changes in the brain that begin long before symptoms appear. The most distinctive features are extracellular neuritic plaques and intracellular neurofibrillary tangles.Neuritic plaques form in the cerebral cortex and around blood vessels. These plaques contain a dense core of beta-amyloid (Aβ)—a toxic protein fragment that clumps outside neurons. The core is surrounded by damaged neuronal extensions, as well as reactive astrocytes and microglia. Abnormal...
Parkinson Disease ll: Pathophysiology01:24

Parkinson Disease ll: Pathophysiology

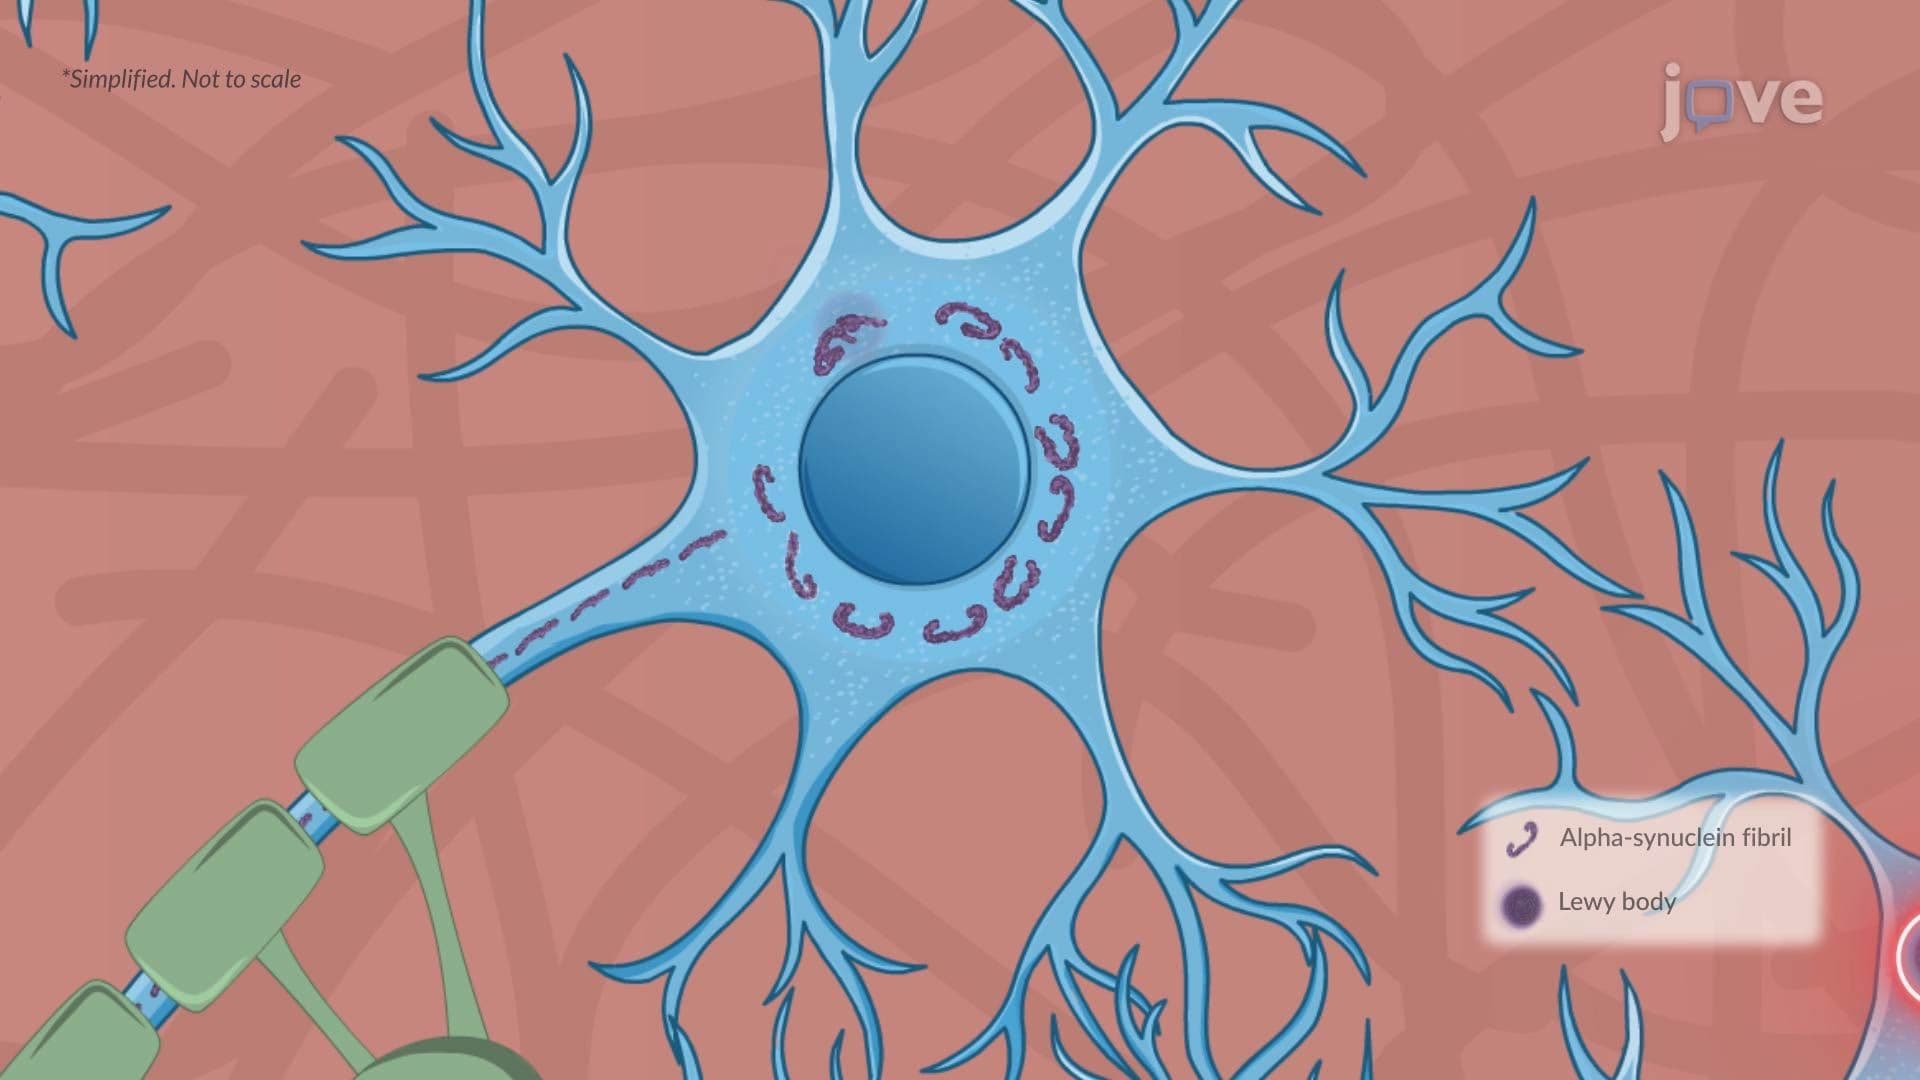
Parkinson disease (PD) is a progressive neurodegenerative disorder primarily affecting movement, with additional non-motor features. Its pathophysiology involves complex interactions among genetic susceptibility, environmental exposures, and cellular dysfunction, including dopaminergic neuron loss, protein aggregation, and mitochondrial impairment.Selective NeurodegenerationA key feature is the degeneration of dopaminergic neurons in the substantia nigra pars compacta, leading to reduced...