Efficiency of inhaled nitric oxide as rescue therapy during severe ARDS: survival and factors associated with the first response
Related Experiment Video
Updated: Oct 18, 2026
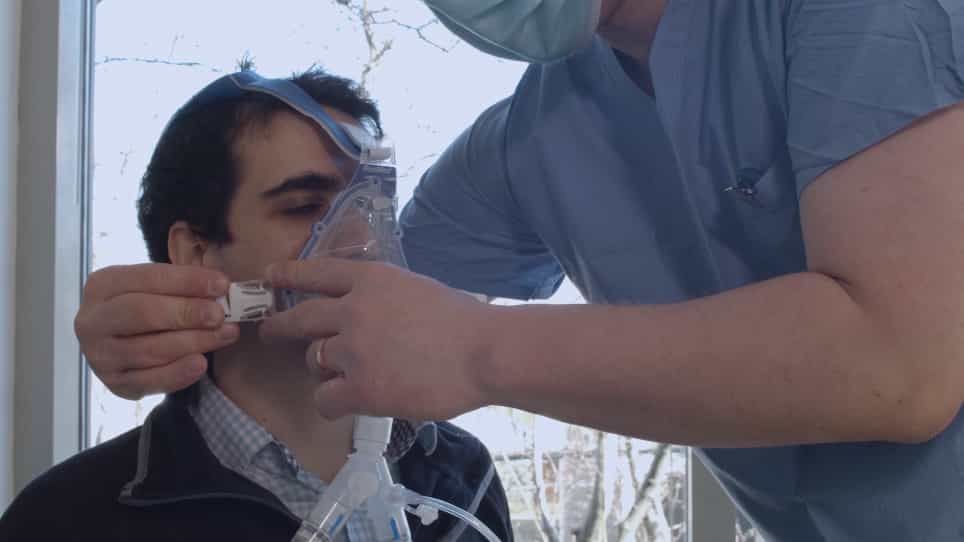
A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
H Dupont1, F Le Corre, L Fierobe
1Clinique de Réanimation des Maladies Infectieuses, and Service de Réanimation Chirurgicale, Hôpital Bichat Claude-Bernard, Paris, France.

Purpose:
The purpose of this study was to determine if the response to inhaled nitric oxide (NO) as salvage therapy is an independent factor for survival in adult respiratory distress syndrome (ARDS) patients and to identify the factors that predict the response to inhaled NO during ARDS.
Materials And Methods:
This was a multicenter, 2-year retrospective, clinical study in five university surgical or medical intensive care units, including all consecutive patients with ARDS in whom inhaled NO was tried. Clinical data (medical history, diagnoses), general severity scores (SAPS II, OSF), biological data, radiological and hemodynamic data at admission, at the beginning of the ARDS, and under treatment with inhaled NO were recorded. The NO response was defined as the variation of PaO2/Fio2 ratio before initiation and after 30 minutes of NO inhalation (VarPaO2/FiO2).
Results:
Ninety-three patients aged 49 +/- 18 years were studied. Mean SAPS II was 45 +/- 16. Before the beginning of inhaled NO, PaO2/Fio2 ratio was 95 +/- 53 mm Hg and lung injury score 2.7 + 0.3. VarPao2/Fio2 when NO was started (11 +/- 4 ppm) was 26 +/- 44.5 mm Hg (median 17 mm Hg). Intensive care unit mortality was 74%. None of the parameters studied were predictors of response to inhaled NO, although there was a tendency for the youngest patients with the more severe hypoxemia to have a better response. Response to first inhaled NO test (VarPaO2/FiO2) was univariately associated with survival (Survivors: 45 +/- 44 mm Hg vs. Nonsurvivors: 20 +/- 43 mm Hg, P = .01), but this difference disappeared after adjusting for other prognostic factors (P = .16) selected by multivariate analysis. Finally, inhaled NO was continued for more than 1 day for 75 patients, and definitively stopped for 18 patients. Intensive care unit mortality (73% vs. 78%) was not different between these groups (P = .25, Log-rank test).
Conclusions:
We conclude that (1) efficacy of inhaled NO in improving oxygenation was moderate and difficult to predict, (2) response to first NO inhalation was not associated with prognosis, and (3) treatment of the most severe ARDS patients with inhaled NO did not influenced their intensive care unit survival.
Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III