Related Experiment Video
Updated: Aug 17, 2026
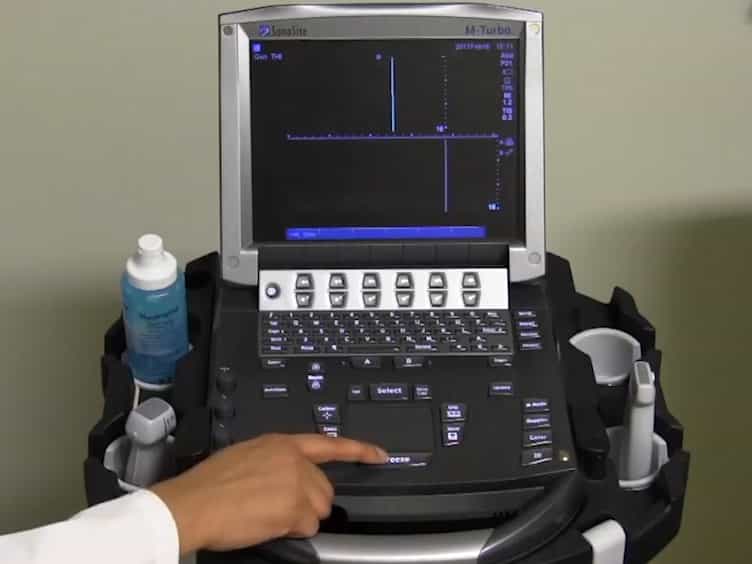

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Effect of ED management on ICU use in acute pulmonary edema
A Sacchetti1, E Ramoska, M E Moakes
1Our Lady of Lourdes Medical Center Department of Emergency Medicine, Camden, NJ 08103, USA.

Abstract:
Acute pulmonary edema (APE) is a common Emergency Department (ED) presentation requiring admission to an intensive care unit (ICU). This study was undertaken to examine the effect of ED management on the need for ICU admission in patients with APE. ED records of APE patients were abstracted for patient age, prehospital and ED pharmacological treatment, diagnoses, airway interventions, and ICU length of stay (LOS). Statistical analysis was through multiple regression, logistic regression, chi-square, and ANOVA. One hundred eighty-one patients composed the study group. Pharmacological treatment included nitroglycerin (NTG), 147 patients (81%); morphine sulfate (MS), 88 (49%); loop diuretics (LD), 133 (73%); and captopril sublingual (CSL), 47 (26%). Use of CSL and MS were associated with opposing needs for ICU admission. MS use was associated with increased ICU admissions (odds ratio, 3.08; P = .002), whereas CSL use was associated with decreased ICU admissions (odds ratio, 0.29; P = .002). Morphine sulfate use also demonstrated an increased need for endotracheal intubation (ETI) (odds ratio, 5.04; P = .001), whereas CSL demonstrated a decreased need for ETI (odds ratio, 0.16; P = .008). Ninety-three patients required some form of respiratory support. Forty received noninvasive pressure support ventilation (NPSV) from a bilevel positive airway pressure system (BiPAP), and 60 received endotracheal intubation. Some patients received more than 1 form of respiratory support; all other patients received supplemental oxygen only. The ICU-LOS associated with different airway interventions were supplemental oxygen, 0.72 days; BiPAP, 1.48 days; and ETI, 3.70 days (P < .001). Specific ED pharmacological interventions are associated with a decreased need for ICU admission and endotracheal intubation in acute pulmonary edema patients, whereas use of noninvasive pressure support ventilation correlates with a reduction in the ICU length of stay for patients who do require critical care admission.
More Related Videos


Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:18
Pulmonary Edema II: Pathophysiology