Related Experiment Video
Updated: Sep 14, 2026
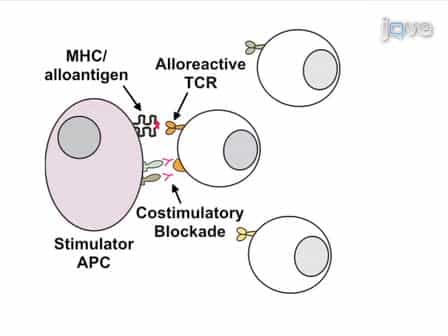
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
High-dose chemo/radiotherapy and autologous bone marrow or stem cell transplantation for poor-risk advanced-stage
A Nademanee1, A Molina, H Fung
1Department of Hematology and Bone Marrow Transplantation, City of Hope National Medical Center, Duarte, California 91010, USA.

Abstract:
Complete remission rates of 70-90% can be achieved following combination chemotherapy for patients with advanced-stage Hodgkin's disease (HD). Patients who present with unfavorable poor prognostic factors, however, have a 5-year disease-free survival of only 40-50%. In an attempt to improve the prognosis of 20 patients with poor-risk advanced-stage HD, we evaluated the role of early high-dose therapy (HDT) and autologous bone marrow/stem cell transplantation (ASCT) during the first complete or partial remission (CR/PR). Patients were eligible for ASCT if they either achieved a PR (defined as > 50% regression) (six patients), or achieved a CR (14 patients) but had presented with three or more of the following unfavorable features: stage IV disease with bone marrow involvement or > or = 2 extranodal sites of involvement; bulky mass > 10 cm or bulky mediastinal mass > 1/3 of mediastina/thoracic ratio; B symptoms; and elevated serum lactate dehydrogenase (LDH) level. The study included 11 men (55%) and 9 women (45%). The median age was 37 years (range 20-57). Seventeen patients (85%) had stage IV disease; 14 (70%) had B symptoms; 13 (65%) had bulky mass > 10 cm; 14 (70%) had > or = 2 extra nodal sites involvement; and eight patients (40%) had elevated LDH levels. All patients were treated with standard four or 7-8 drug combination chemotherapy regimens until they achieved maximal response prior to ASCT with a median of six cycles (range 4-11). Six patients also received involved field radiotherapy to residual bulky mass > 5 cm or bony lesions before ASCT. The median time from diagnosis to ASCT was 8.6 months (range 5.5-18.9). Preparative regimens consisted of fractionated total body irradiation (FTBI) 1200 cGy in combination with etoposide 60 mg/kg and cyclophosphamide 100 mg/kg in all patients except one who had borderline pulmonary function and received lomustine 15 mg/kg instead of FTBI. All patients engrafted and there was no transplant-related mortality. One patient developed congestive cardiomyopathy at 4 years post-ASCT. All patients remain alive and in remission at a median follow-up of 42.8 months (range, 13.2-149.2). These preliminary results suggest that HDT and ASCT can be performed safely during first CR/PR in selected patients with advanced-stage HD who have an unfavorable prognosis. Further randomized studies comparing HDT and ASCT during first CR with conventional chemotherapy and ASCT at relapse in poor-risk advanced-stage HD should be conducted. The prognostic factors and risk groups described recently by an international prognostic study can be used to identify high-risk patients who may be candidates for more intensive therapy.


Related Concept Videos
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:21
Stem Cell Therapy for Tissue Regeneration
Types of Stem Cells used in Stem Cell Therapy
The two main cell types that...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...