Related Experiment Video
Updated: Oct 18, 2026
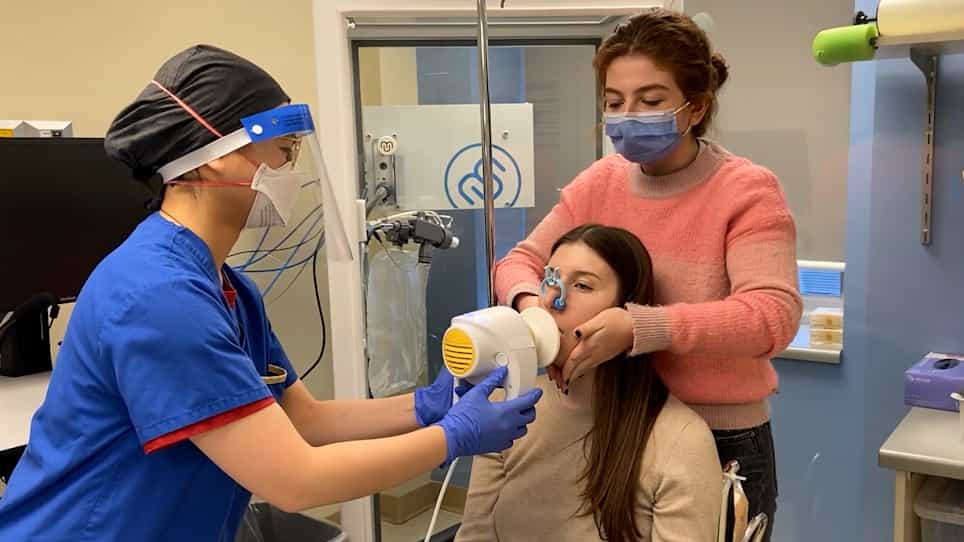
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Serial measurements of exhaled nitric oxide during exacerbations of chronic obstructive pulmonary disease
A G Agustí1, J M Villaverde, B Togores
1Servei de Pneumologia and Unitat d'investigació, Hospital Universitari son Dureta, Palma de Mallorca, Spain.

Abstract:
Excessive inflammation seems important in chronic obstructive pulmonary disease (COPD), particularly during exacerbations of the disease. Exhaled nitric oxide concentration ([NOexh]) is a sensitive marker of bronchial inflammation in asthma; it is unclear if this is also the case in COPD. This study: 1) quantifies [NOexh] in patients with COPD (during an exacerbation and while clinically stable); 2) investigates the response of [NOexh] to i.v. steroid therapy, and its potential relationship with other relevant physiological variables; and 3) assesses the relative contributions of the central and peripheral airways to [NOexh] by collecting exhaled air in two different bags connected in series. Seventeen COPD patients (forced expiratory volume in one second (FEV1) 37.6+/-3.4% of the predicted value (+/-SEM)) hospitalized because of an exacerbation of the disease (arterial oxygen tension (Pa,O2) (7.46+/-0.72 kPa 56.1+/-5.4 mmHg), arterial carbon dioxide tension (Pa,CO2) 5.63+/-0.37 kPa 42.3+/-2.8 mmHg), pH 7.41+/-0.02) and 10 healthy subjects that served as controls were studied. On admission, [NOexh] in COPD was higher than normal (41.0+/-5.1 versus 13.3+/-0.8 parts per billion (ppb), respectively, p<0.001). Despite i.v. steroid therapy, [NOexh] remained elevated throughout recovery (37.9+/-4.8 ppb, p<0.001) until discharge (40.9+/-4.3 ppb, p<0.001). In contrast, when the patients were clinically stable (several months later), [NOexh] was significantly reduced (15.8+/-3.8 ppb, p<0.001), and no longer different from control values. [NOexh] was not related to any of the physiological variables measured during recovery (pulmonary gas exchange) or at discharge (forced spirometry, lung volumes, diffusing capacity). Finally, the contribution of the central and peripheral airways to [NOexh] was not different at any point in time. These results indicate that during exacerbations of chronic obstructive pulmonary disease, the exhaled nitric oxide concentration: 1) is higher than normal; 2) is not reduced acutely by i.v. steroids but is normalized several months after discharge; 3) is unrelated to several physiological indices of disease severity; and 4) appears to be produced homogeneously in central and peripheral airways. Overall, these results are different from those reported in asthma, suggesting that different inflammatory mechanisms are operating in both diseases.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...