[Hypersplenism: current status and perspectives]
Related Experiment Video
Updated: Oct 18, 2026
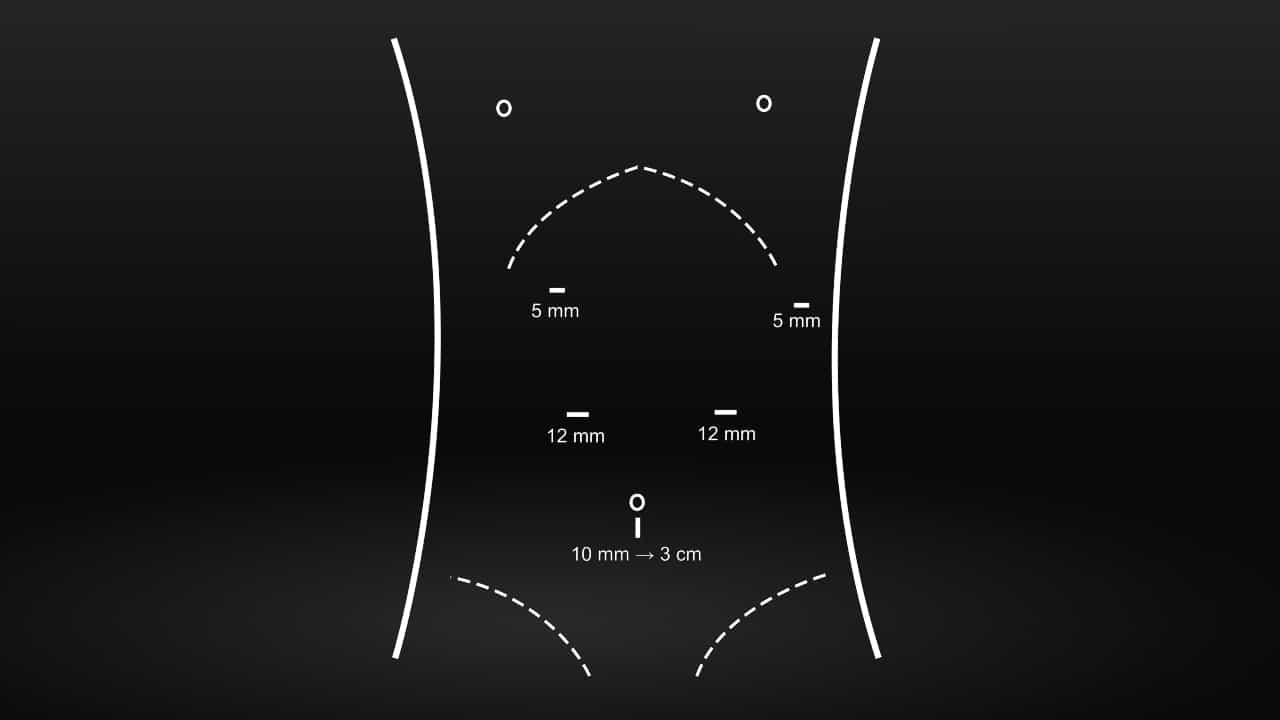
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
C Musolino1, L Calabrò, A Alonci
1Dipartimento di Medicina Interna, Università, Messina.

Abstract:
The hypersplenism is a syndrome characterized by cytopenia (involving one or several cellular lines of peripheral blood), increased or normal medullar cellularity, elevated turnover of the involved cellular line. Several studies have emphasized the important role of the spleen as an immunocompetent organ, with a microcirculation and typical functional characteristics. The authors attempt to assess relations between the hypersplenism and splenomegaly, as well as indications, risks and complications of splenectomy in pathological conditions. Finally, the alternative procedures to splenectomy are described.
More Related Videos
Related Concept Videos
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:24
Cirrhosis II: Pathophysiology
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:26
Gastritis II: Pathophysiology
 01:19
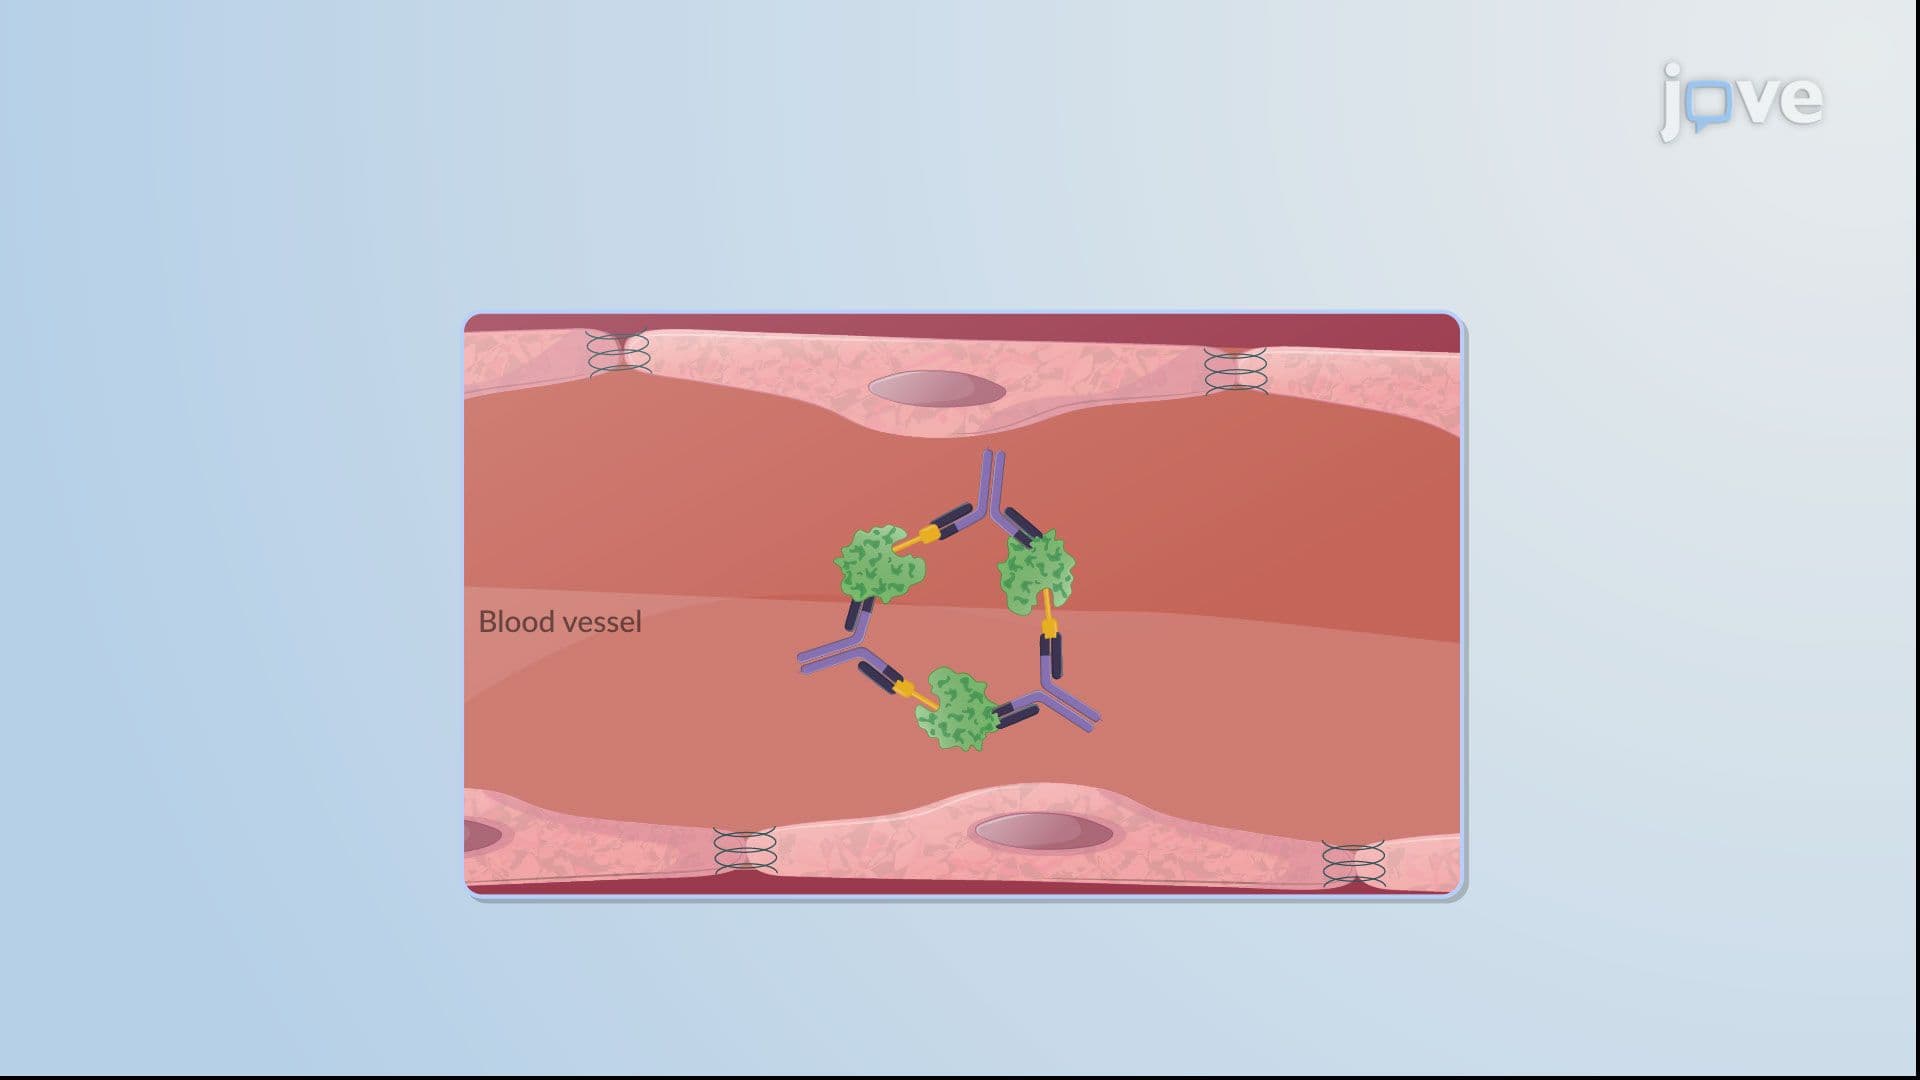
Hypersensitivity Reactions: Immune-Complex Reactions
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...