Baroreflex sensitivity is depressed in microalbuminuric Type I diabetic patients at rest and during sympathetic manoeuvres
Related Experiment Video
Updated: Oct 18, 2026

Implantation of Combined Telemetric ECG and Blood Pressure Transmitters to Determine Spontaneous Baroreflex Sensitivity in Conscious Mice
Published on: February 14, 2021
J D Lefrandt1, K Hoogenberg, A M van Roon
1Department of Internal Medicine, Division of Angiology and General Medicine, State University Hospital, Groningen, The Netherlands.

Aims/Hypothesis:
To evaluate baroreflex sensitivity (BRS) in microalbuminuric and normoalbuminuric Type I (insulin-dependent) diabetic patients without autonomic neuropathy and in healthy control subjects.
Methods:
Microalbuminuric Type I diabetic patients (n = 15) were matched for age, sex, body mass index (BMI) and smoking habits with 15 normoalbuminuric patients and with 15 healthy control subjects. All subjects had a blood pressure less than 160/95 mmHg, a BMI less than 30 kg/m(2) and normal autonomic function on standard tests. Blood pressure and heart rate were measured non-invasively (Finapres) at rest and during sympathetic activation (handgrip, mental stress, standing). The baroreflex sensitivity was defined as the mean gain between blood pressure variability and heart rate variability in the 0.07-0.15 Hz frequency band.
Results:
Resting baroreflex sensitivity was decreased in the microalbuminuric patients (3.5 +/- 0.4 ms/mmHg) compared with the normoalbuminuric patients and the healthy subjects (7.6 +/- 1.6 and 9.5 +/- 1.1 ms/mmHg, respectively, p < 0.001). The sympathetic tests reduced baroreflex sensitivity similarly in the groups without changing the between group differences.
Conclusion/Interpretation:
Baroreflex sensitivity is reduced in Type I diabetic patients with microalbuminuria but without autonomic neuropathy. A prospective study should indicate whether this early abnormality in cardiovascular reflex function is a risk factor of cardiovascular mortality in these patients. [Diabetologia (1999) 42: 1345-1349]

Related Concept Videos
 01:28
Diabetic Nephropathy
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:22
Diabetic Neuropathy
 01:26
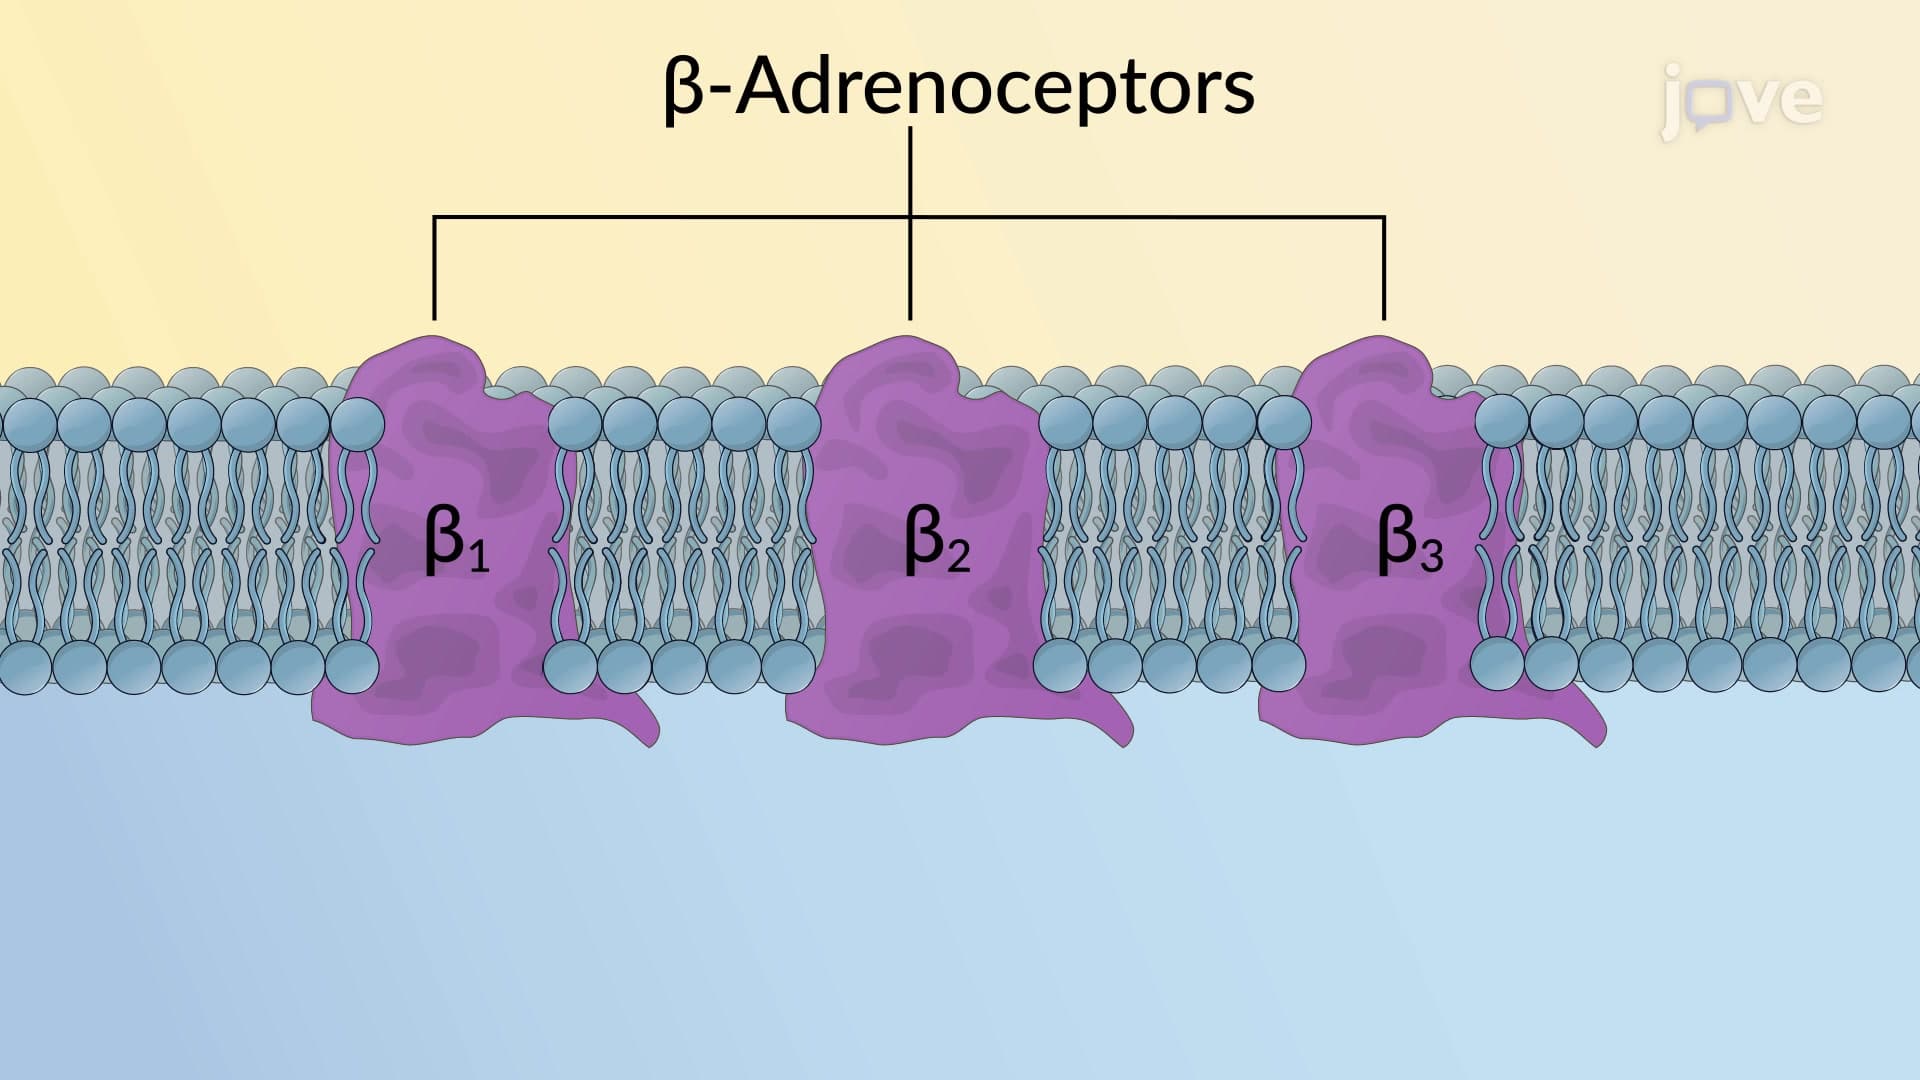
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:18
Hypertension and Regulation of Blood Pressure