Related Experiment Video
Updated: Oct 18, 2026
Isolation of Human Atrial Myocytes for Simultaneous Measurements of Ca2+ Transients and Membrane Currents
Published on: July 3, 2013
Beta4-adrenoceptors are more effective than beta1-adrenoceptors in mediating arrhythmic Ca2+ transients in mouse
N S Freestone1, J F Heubach, E Wettwer
1Laboratory of Molecular Signalling, The Babraham Institute, Cambridge, UK.

Abstract:
Putative beta4-adrenoceptors mediate cardiostimulation and arrhythmias in mammalian heart. Both beta1- and putative beta4-adrenoceptors mediate arrhythmias but through different mechanisms. To elucidate further the mechanisms of cardiostimulation and arrhythmias we measured Ca2+ transients and L-type Ca2+ currents in mouse ventricular myocytes. We used (-)-CGP 12177, an antagonist of beta1- and beta2-adrenoceptors with agonist properties at the putative beta4-adrenoceptor, and (-)-isoprenaline as an agonist for beta1- and beta2-adrenoceptors. (-)-CGP 12177 increased Ca2+ transients in electrically stimulated cells loaded with Indo-1. The maximum increase of Ca2+ transients caused by (-)-CGP 12177 amounted to approximately one-third of that caused by maximally effective (-)-isoprenaline concentrations. Both (-)-CGP 12177 and (-)-isoprenaline caused concentration-dependent arrhythmic Ca2+ transients. The arrhythmias appeared at paced Ca2+ transients and between paced Ca2+ transients. The arrhythmic potency of (-)-CGP 12177 (-logEC50=9.4) was approximately 40 times greater than that of (-)-isoprenaline (-logEC50=7.8). L-type Ca2+ current was measured in the whole cell configuration of the patch clamp technique. In the presence of both 3-isobutyl 1-methylxanthine (6 micromol/l) and (-)-propranolol (500 nmol/l), (-)-CGP 12177 (100 nmol/l) increased significantly L-type Ca2+ current by 19% of the effect of (-)-isoprenaline. The (-)-CGP 12177-evoked increase of Ca2+ transients contrasts with the smaller effects on L-type Ca2+ current, suggesting that activation of the putative beta4-adrenoceptor causes a more efficient Ca2+-induced Ca2+ release than activation of the beta1-adrenoceptor. Beta4-Adrenoceptors mediate arrhythmias with smaller Ca2+ transients and smaller increases of L-type Ca2+ current than beta1-adrenoceptors, in line with different but still unknown mechanisms as previously suggested for the intact heart.
Insights
The study reveals that beta4-adrenoceptors mediate cardiac arrhythmias and calcium transients more potently than beta1-adrenoceptors. This suggests distinct mechanisms for beta4-adrenoceptor-induced arrhythmias, involving more efficient calcium release.
Area of Science:
- Cardiology
- Pharmacology
- Molecular Biology
Background:
- Beta-adrenoceptors play crucial roles in cardiac function, with beta1 and beta2 subtypes being well-characterized.
- The existence and function of putative beta4-adrenoceptors in the mammalian heart are less understood but implicated in cardiostimulation and arrhythmias.
Purpose of the Study:
- To investigate the specific roles of beta4-adrenoceptors in mediating cardiac calcium (Ca2+) transients and L-type Ca2+ currents.
- To compare the arrhythmogenic potency and underlying mechanisms of beta4-adrenoceptor activation versus beta1-adrenoceptor activation.
Main Methods:
- Utilized mouse ventricular myocytes to measure Ca2+ transients using Indo-1 fluorescence and L-type Ca2+ currents via patch-clamp electrophysiology.
- Employed specific pharmacological agents: (-)-CGP 12177 (a beta4-adrenoceptor agonist) and (-)-isoprenaline (a beta1/beta2-adrenoceptor agonist).
- Conducted experiments in the presence of beta1/beta2 antagonists ((-)-propranolol) and a phosphodiesterase inhibitor (3-isobutyl 1-methylxanthine) to isolate beta4-adrenoceptor effects.
Main Results:
- (-)-CGP 12177 significantly increased Ca2+ transients and induced concentration-dependent arrhythmias, with approximately 40 times greater arrhythmogenic potency than (-)-isoprenaline.
- Activation of beta4-adrenoceptors by (-)-CGP 12177 resulted in a smaller increase in L-type Ca2+ current compared to its effect on Ca2+ transients.
- The data suggest that beta4-adrenoceptor activation leads to more efficient Ca2+-induced Ca2+ release than beta1-adrenoceptor activation.
Conclusions:
- Putative beta4-adrenoceptors are potent mediators of cardiac arrhythmias, acting through mechanisms that enhance Ca2+ release more efficiently than beta1-adrenoceptors.
- Beta4-adrenoceptor-mediated arrhythmias involve smaller increases in Ca2+ transients and L-type Ca2+ current compared to beta1-adrenoceptors, indicating distinct signaling pathways.
- Further research is warranted to fully elucidate the unique mechanisms underlying beta4-adrenoceptor function in the intact heart.

Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
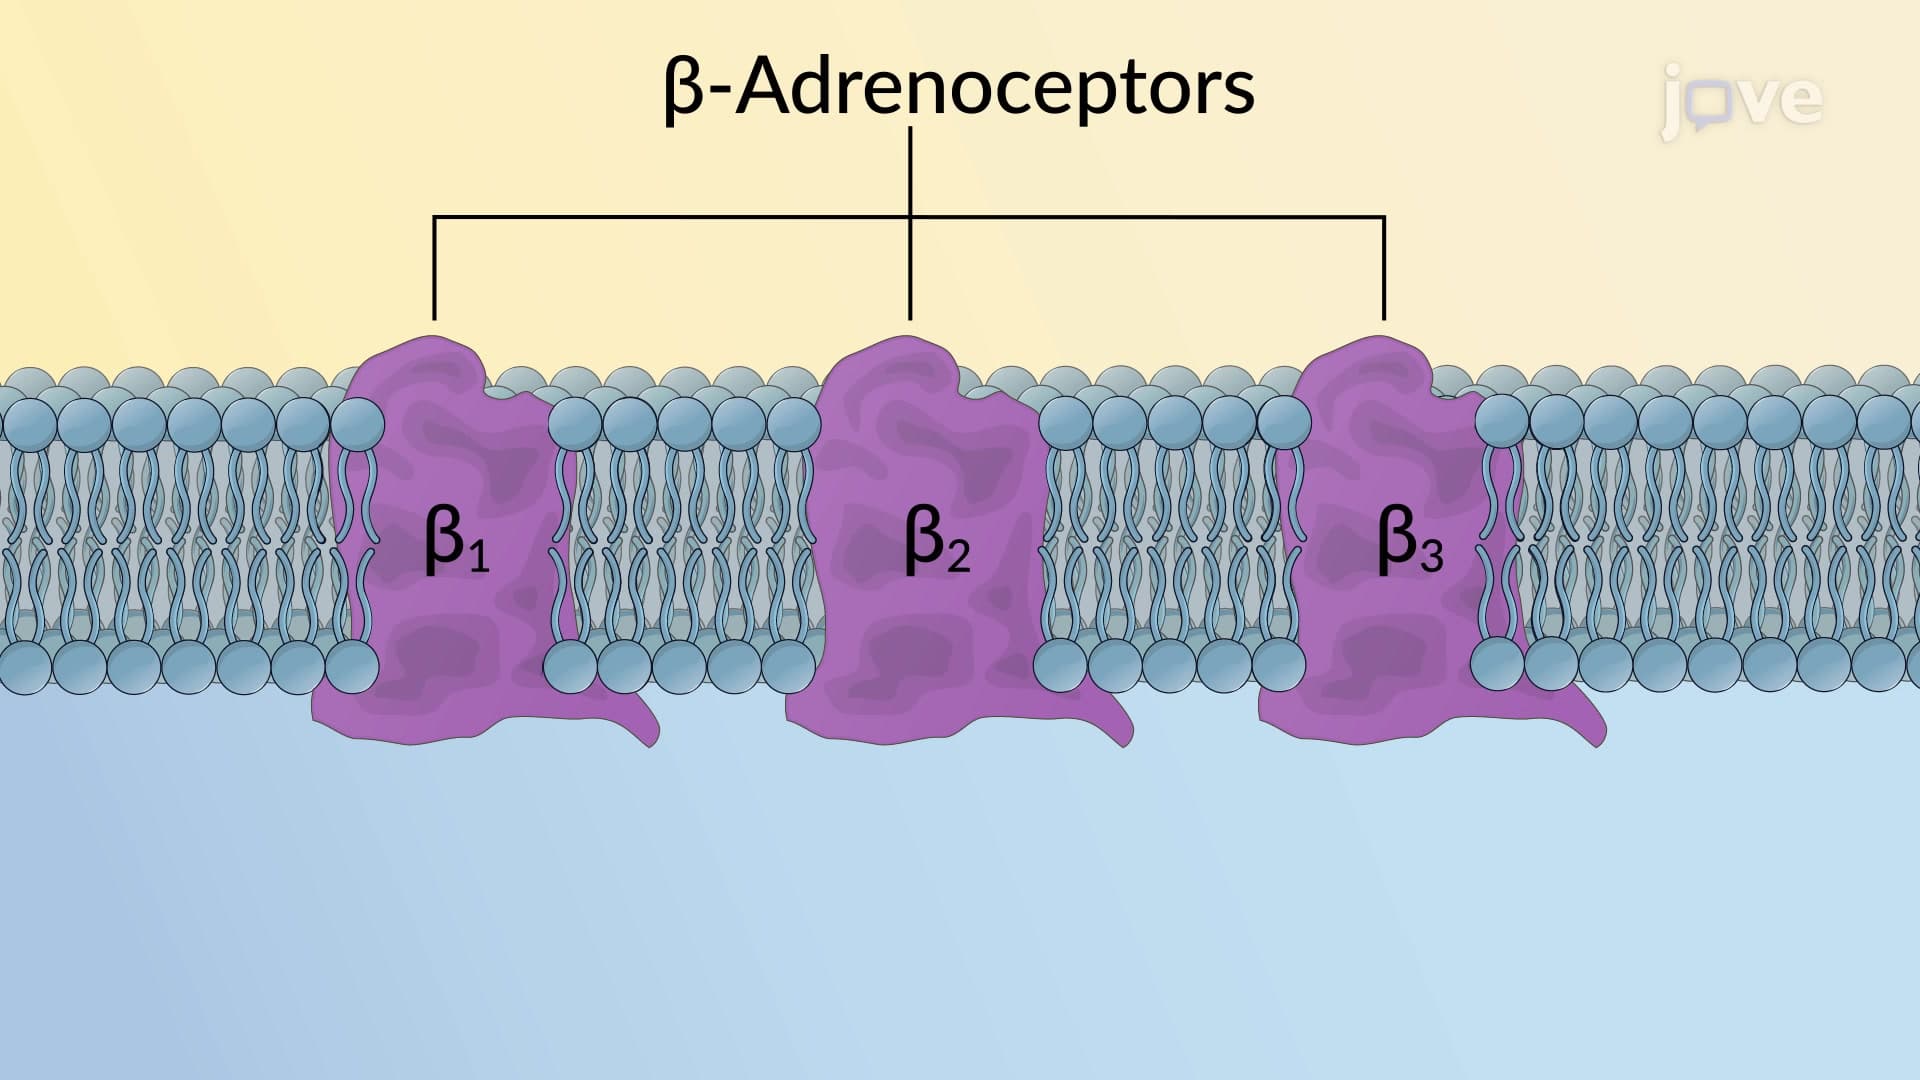
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
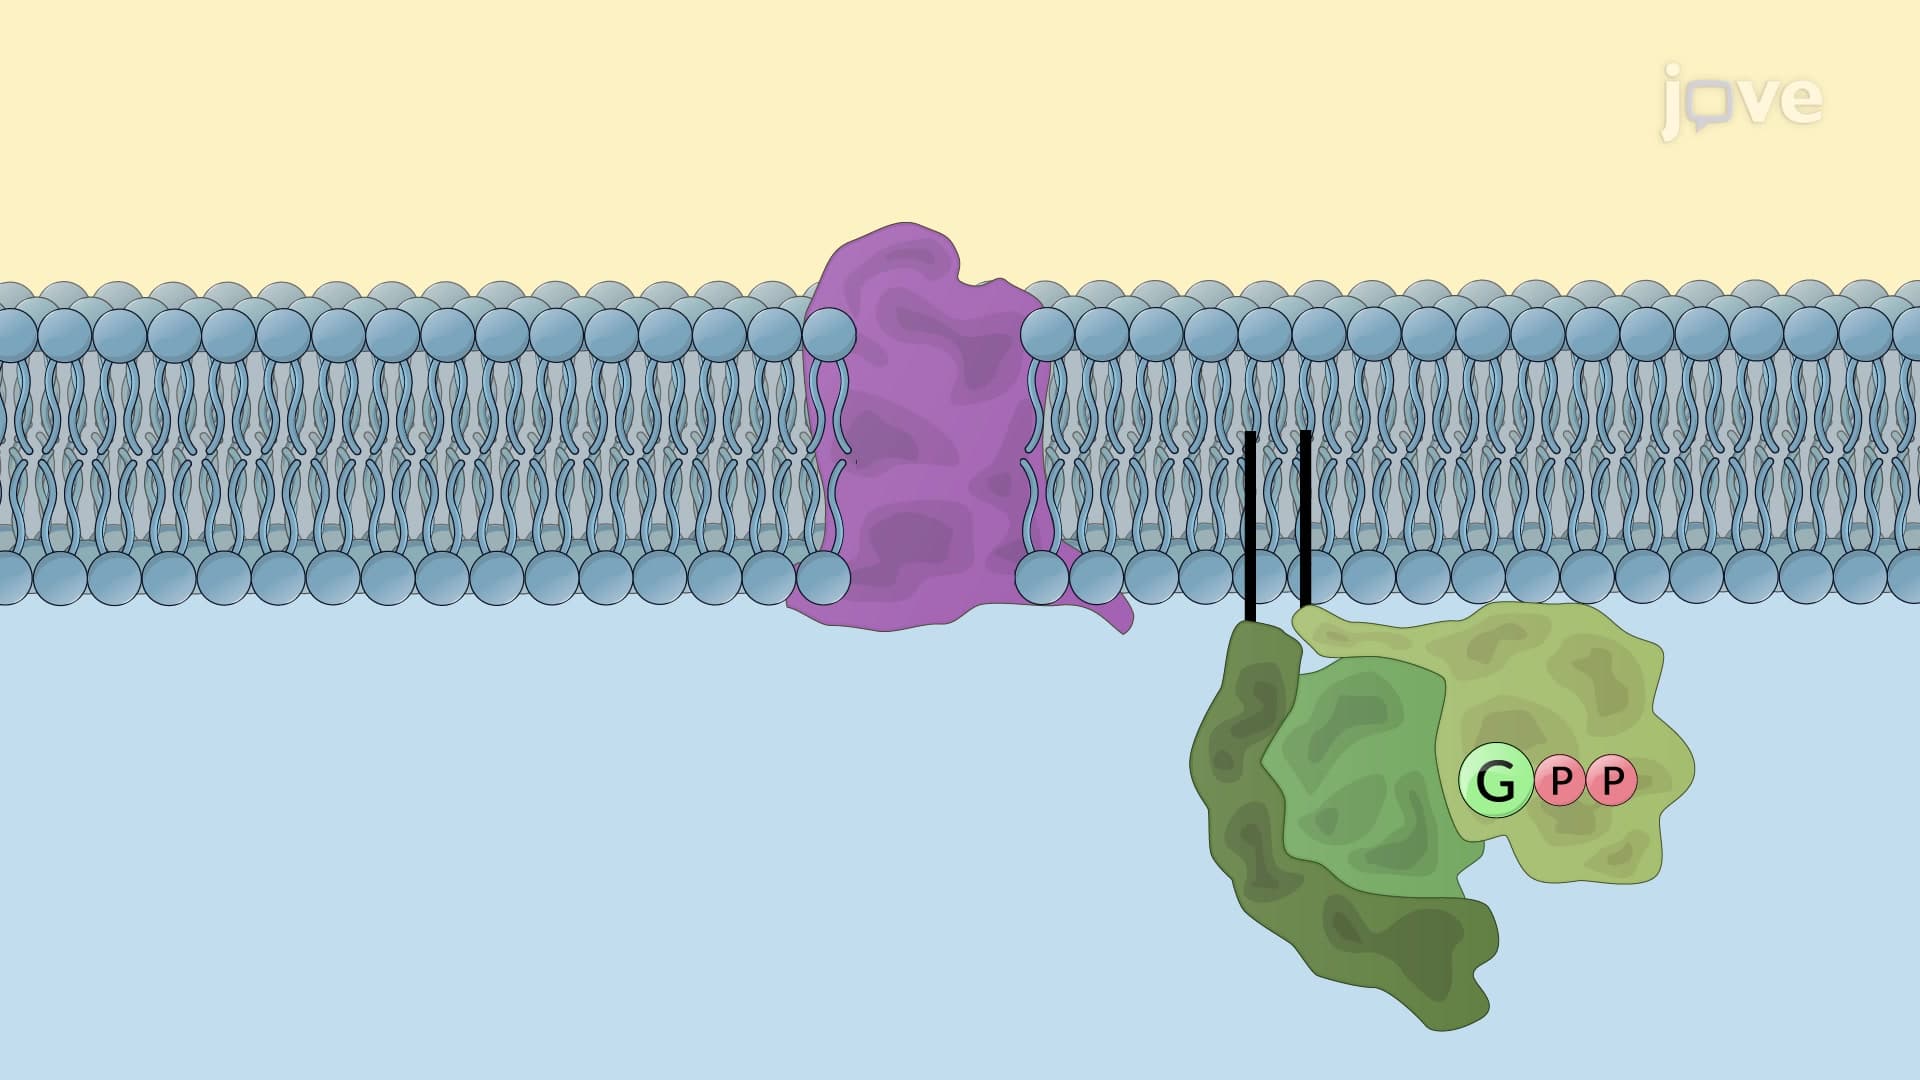
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
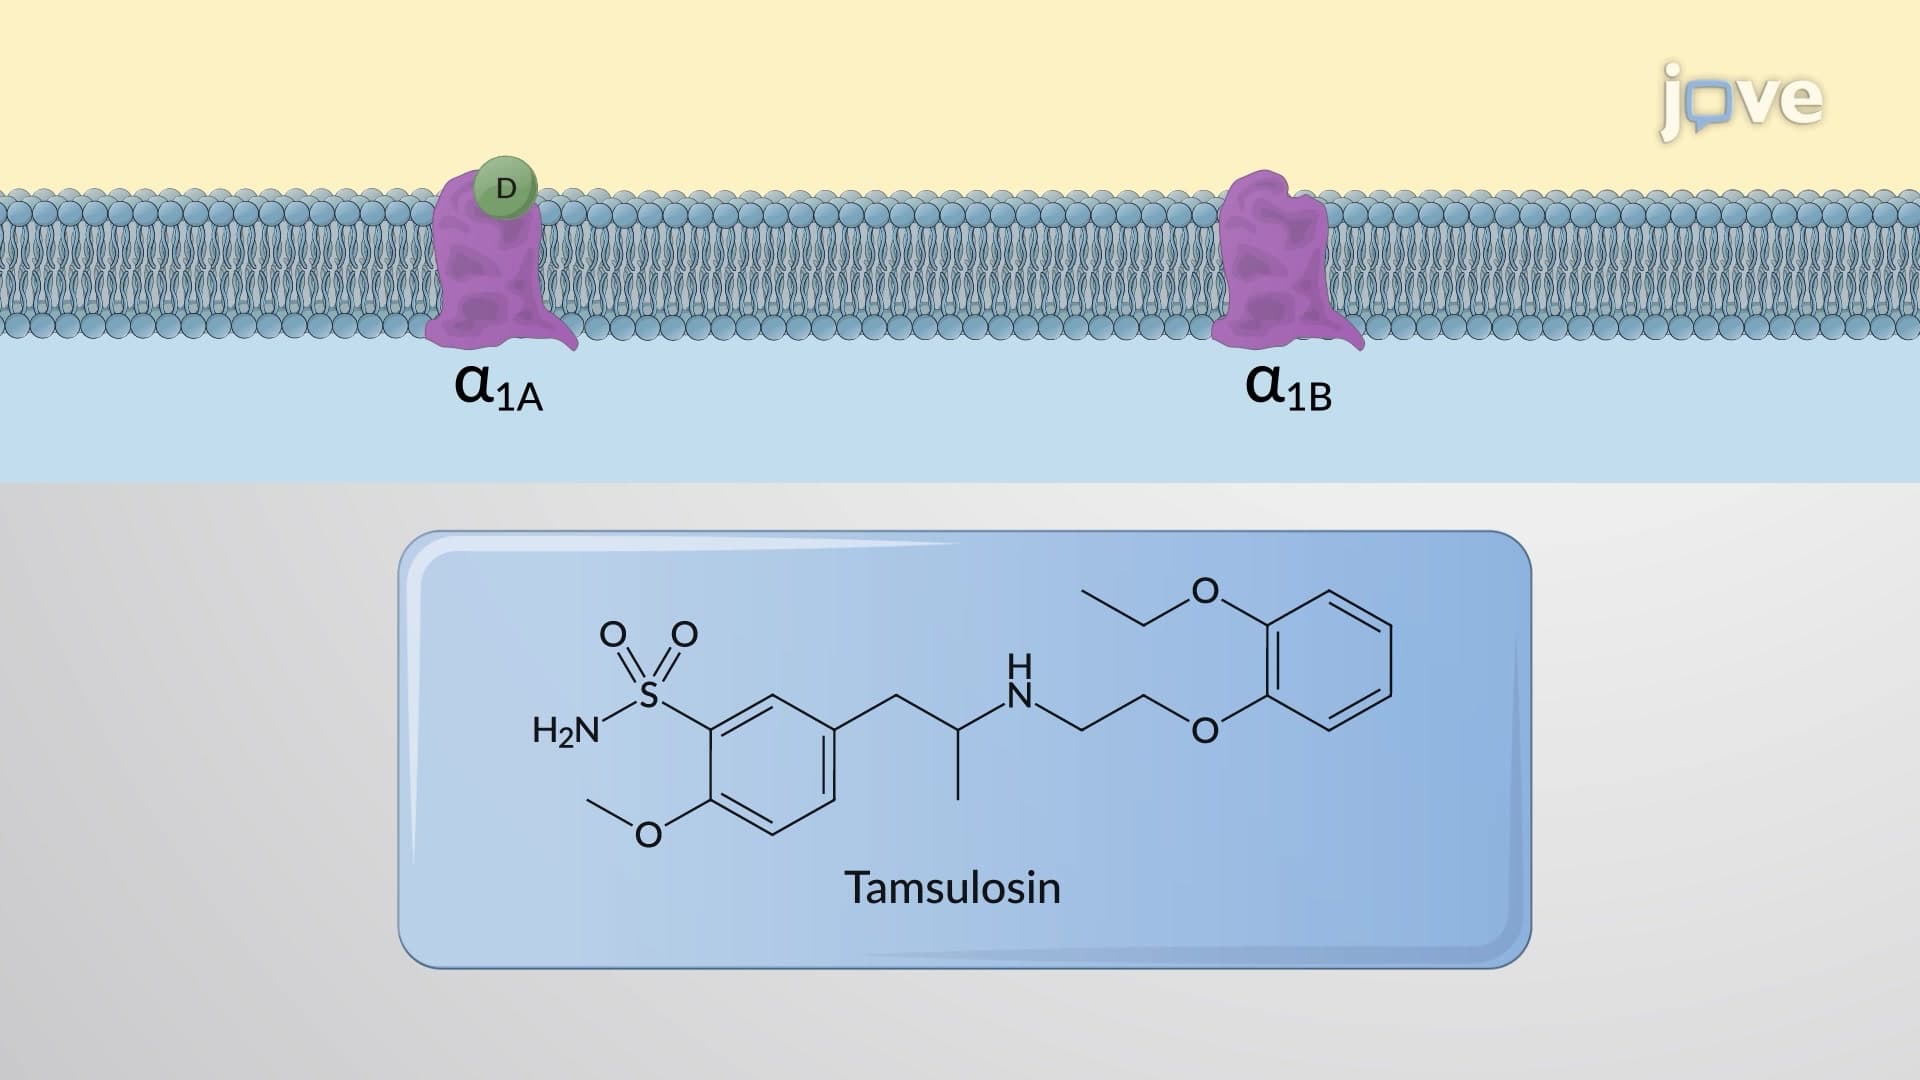 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...