Related Experiment Video
Updated: Jul 22, 2026


Bronchial Thermoplasty: A Novel Therapeutic Approach to Severe Asthma
Published on: November 4, 2010
Comparison of two regimens of beta-adrenergics in acute asthma
M F McDermott1, I Nasr, R J Rydman
1Department of Emergency Medicine, Cook County Hospital, Rush University, Chicago, Illinois 60612, USA.

Background And Methods:
Inhaled adrenergics and steroids are the main agents used in acute asthma. Dosing recommendations for adrenergics, while generally becoming more aggressive, lack prospective validation. A double blind, randomized trial of two regimens of nebulized metaproterenol was conducted in patients presenting to an Emergency Department with an acute asthma exacerbation. Asthmatics age 16-55, with no other cardio-pulmonary disease, presenting with peak expiratory flow rate (PEFR) < 30% of predicted and greater than 80 L/m were enrolled. All patients received 125 mg of methylprednisolone and theophylline, if needed, to reach therapeutic levels. The experimental group received 0.3 cc metaproterenol in 2.5 cc of saline at times 0, 20", 40", 1', 2', 3', 4', 5', 6', and 7'. The control group received metaproterenol at times 0, 1 hr, and hours 3, 5, and 7. Placebo was given to control group patients at 20", 40", 2', 4', and 6'. PEFR and vital signs were measured 10 min after each treatment. Study end points included discharge upon reaching set criteria or admission if patients were not discharged following the hour 7 treatment.
Results:
Seventy one patients were enrolled, 40 in experimental group and 31 in the control group. The group characteristics did not differ at entry in any significant way, and the groups began with mean expected PEFR of 23.4% and 24.5%, respectively. There were no significant differences at any point in PEFR outcomes, time to discharge, or admission rate. The experimental group showed a greater increase in pulse rate and a reduced diastolic blood pressure at 20, 40 and 60 min. The experimental group had a 12- and 8-fold increase in the risk of a pulse rate > 140 at 40 and 60 min, respectively. This group also had two moderate complications, both near the 60-minute mark. These were an induction of atrial fibrillation in one patient and ischemic electrocardiographic changes in another.
Conclusion:
Three treatments in the first hour, and hourly thereafter showed no benefit over treatments initially, at one hour, and every other hour in acute, moderate, or severe exacerbation of asthma. Side effects were markedly increased in the control group. Such dosing should not be recommended as routine therapy.
Related Concept Videos
 01:26
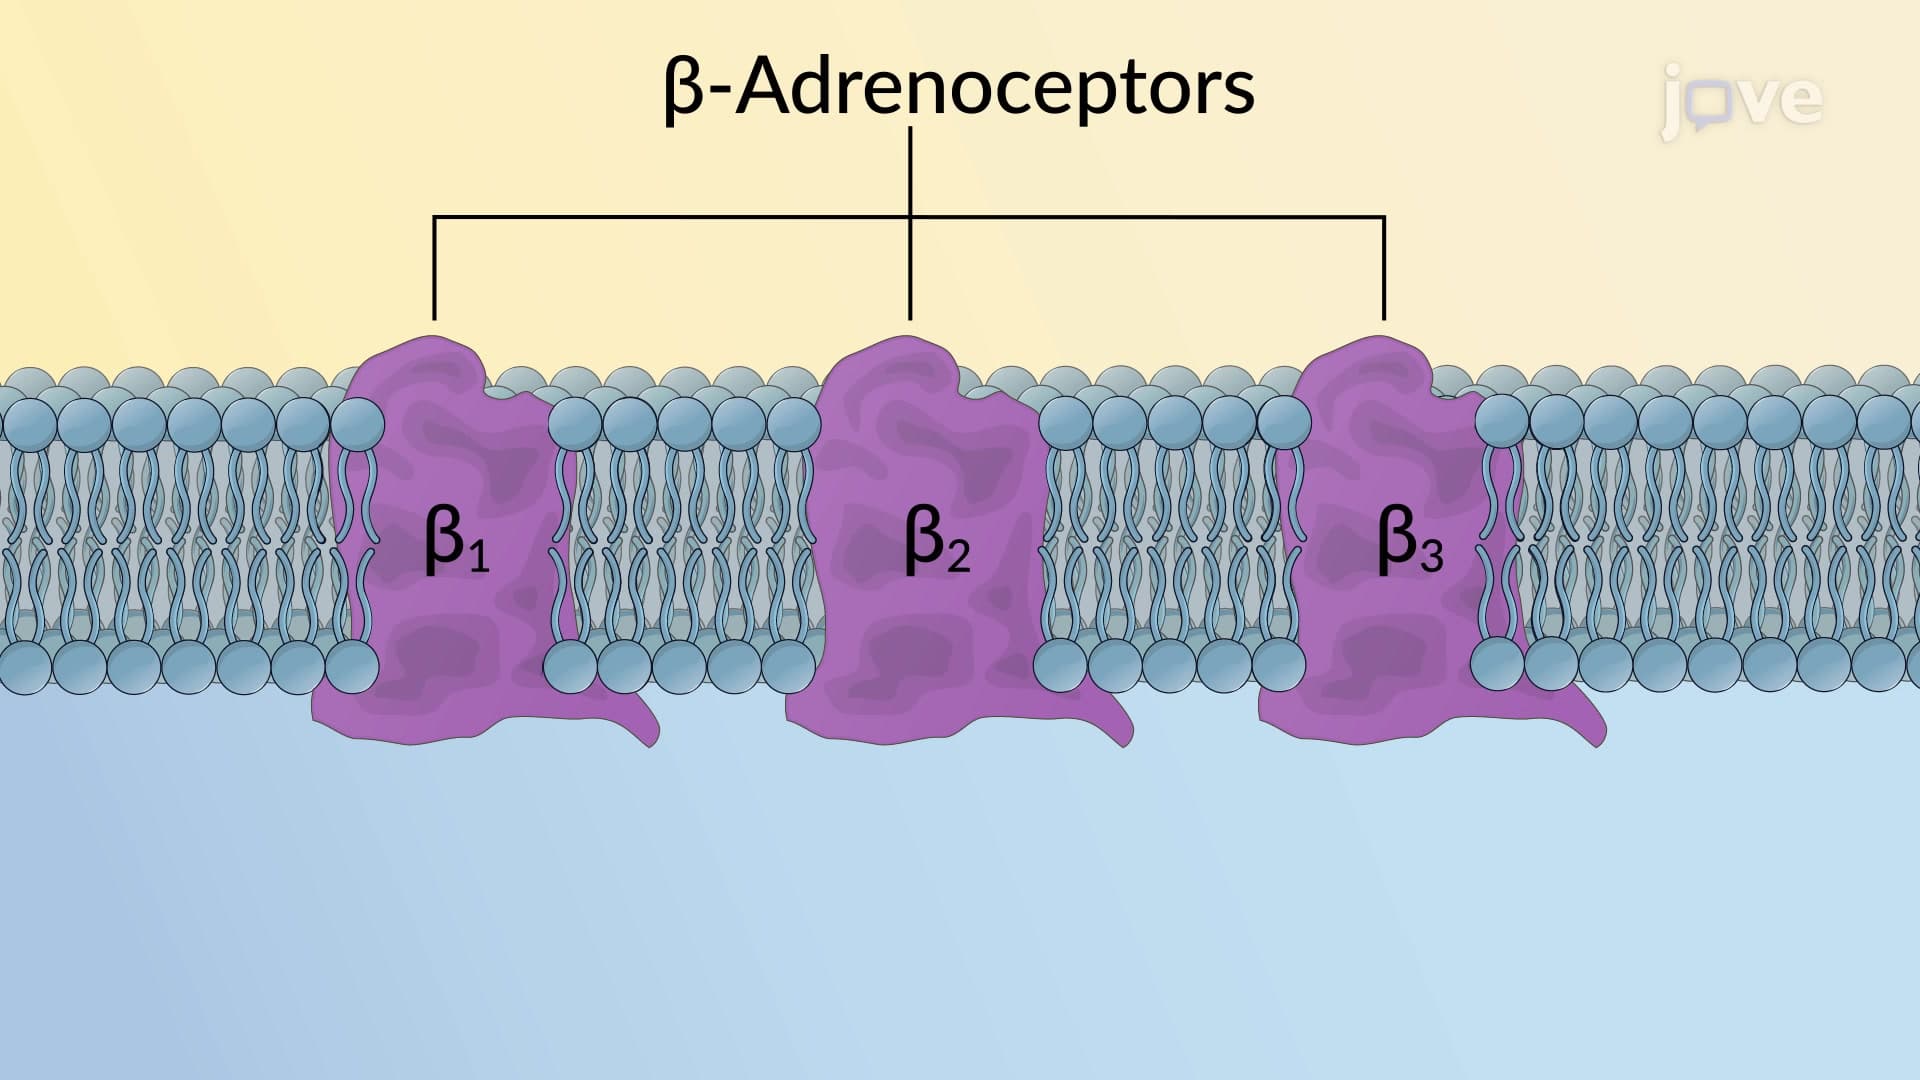
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:25
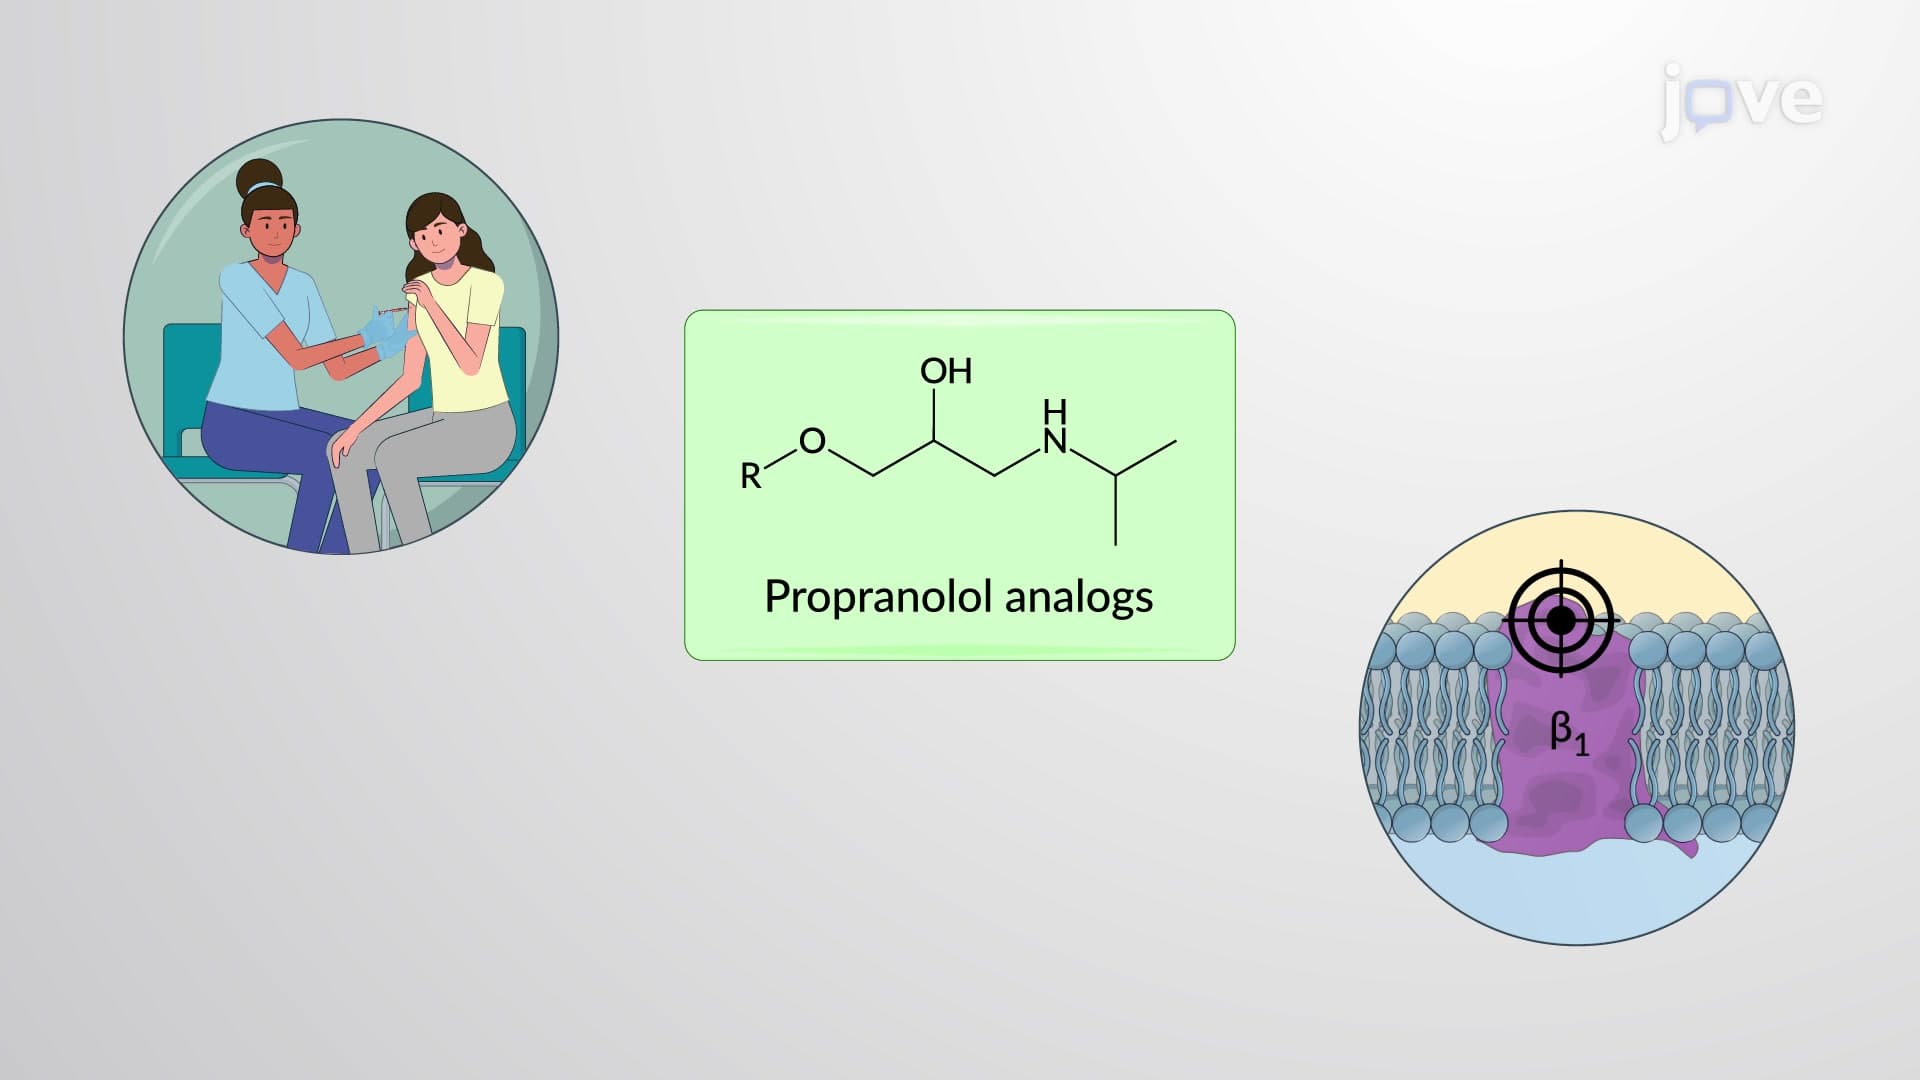
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...