Related Experiment Video
Updated: Aug 20, 2026


Diagnosis of Neoplasia in Barrett’s Esophagus using Vital-dye Enhanced Fluorescence Imaging
Published on: May 11, 2014
Histological findings after routine biopsy at the gastro-oesophageal junction
M Peck-Radosavljevic1, A Püspök, R Pötzi
1Department of Gastroenterology and Hepatology, University of Vienna Medical School, Austria.

Objective:
Endoscopy with biopsy is an important diagnostic procedure in patients with gastro-oesophageal reflux disease. However, it is still unclear whether histological findings such as intestinal metaplasia, squamous epithelial hyperplasia, and carditis should have an impact on patient management, and whether routine biopsies at the gastro-oesophageal junction should be taken.
Design:
Patients undergoing routine gastroscopy for various indications were biopsied twice just below, directly at, and right above the gastro-oesophageal junction.
Methods:
Clinical symptoms, endoscopic oesophagitis, and histopathologies such as carditis, reflux disease, and intestinal metaplasia were determined and graded.
Results:
Epithelial hyperplasia suggestive of reflux disease (63%), chronic carditis (94%), active carditis (40%), foveolar hyperplasia (75%), and intestinal metaplasia (14%) were frequently observed. For patients with a normal appearing Z-line, there was a weak correlation of intestinal metaplasia at the cardia with intestinal metaplasia in the stomach (Spearman's R = 0.2, P = 0.008), but no correlation with either chronic or active carditis, or with epithelial hyperplasia in the oesophagus. There was no correlation between H. pylori status or symptoms of reflux disease with epithelial hyperplasia. The severity of chronic and active carditis was closely correlated with H. pylori status (R = 0.37, P < 0.00001). The median time for gastroscopy in 30 control patients was 4.6 min, while endoscopy with additional biopsies at the gastro-oesophageal junction took a median of 8 min (U-test, P < 0.00001).
Conclusions:
Intestinal metaplasia at the gastro-oesophageal junction was encountered too frequently to warrant regular follow-up in a surveillance programme. Correlation of epithelial hyperplasia with symptoms of reflux disease is poor. We propose that routine biopsy at the gastro-oesophageal junction is not warranted until an impact on patient management can be demonstrated.
More Related Videos
 03:05
Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
 04:08
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Related Concept Videos
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...
 01:27
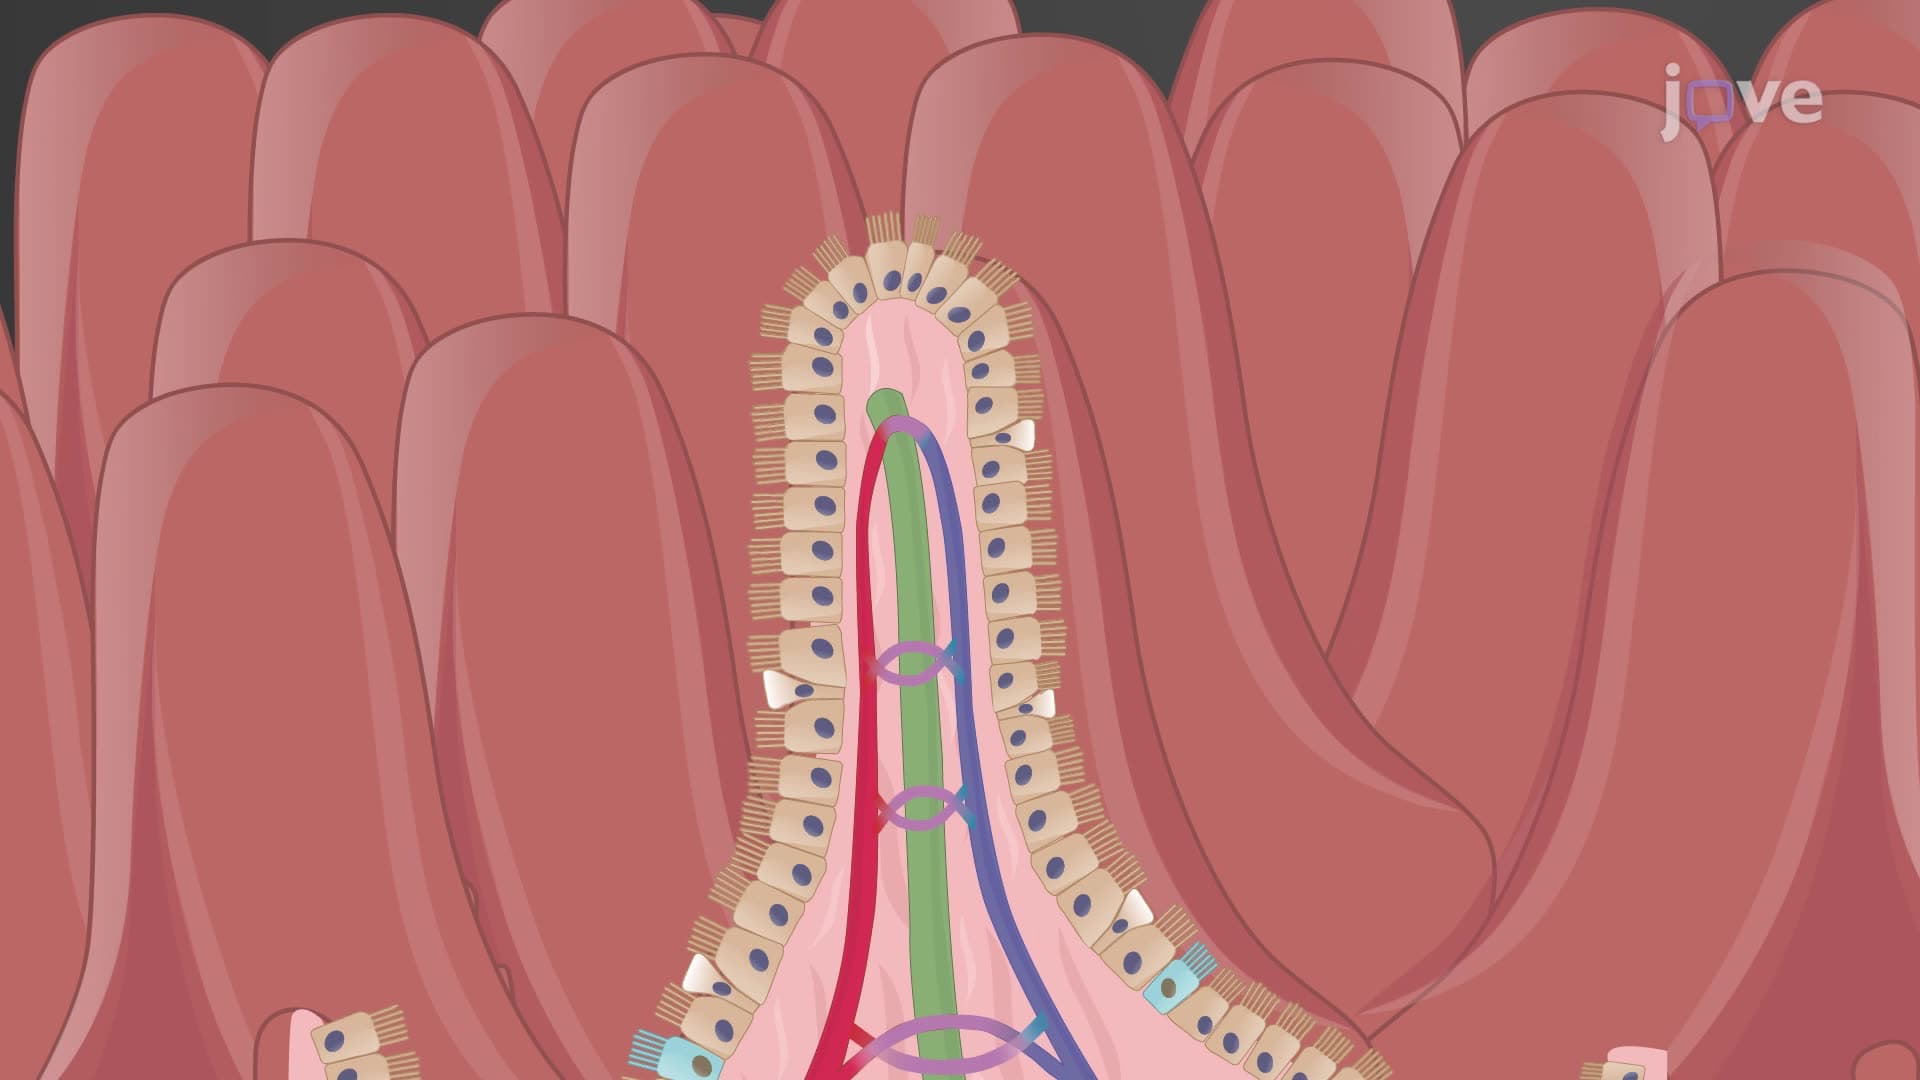
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.