Related Experiment Video
Updated: Oct 13, 2026

A Standardized Method for Measuring Internal Lung Surface Area via Mouse Pneumonectomy and Prosthesis Implantation
Published on: July 26, 2017
Lung function after bilateral lower lobe lung volume reduction surgery for alpha1-antitrypsin emphysema
A F Gelb1, R J McKenna, M Brenner
1Dept of Medicine, Lakewood Regional Medical Center, School of Medicine, University of California, Los Angeles, USA.

Abstract:
This study explores the mechanism(s) of airflow limitation following lung volume reduction surgery (LVRS) in patients with emphysema due to homozygous alpha1-antitrypsin (AT) deficiency. Bilateral targeted lower lobe stapled LVRS using video thoracoscopy was performed in six patients (five males) aged 61+/-9 yrs (mean+/-SD) with alpha1-AT emphysema. Two patients received only a 6-month follow-up. However, four patients, at 22, 24, 27 and 36 months post-LVRS, noted relief from dyspnoea and increased walk tolerance. At 27+/-6 months (mean+/-SD) post-LVRS, their forced expiratory volume in one second improved only from 30+/-2% of the predicted value (mean+/-SEM) before surgery to 33+/-1% pred after surgery. Yet, total lung capacity (TLC) decreased from 151+/-13 to 127+/-10% pred; diffusing capacity increased from 35+/-9 to 59+/-9% pred; and vital capacity increased from 68+/-10 to 88+/-5% pred. In three patients, static lung elastic recoil at TLC increased from 1.1+/-0.15 to 1.2+/-0.10 kPa. Using flow/pressure curves, the mechanism for expiratory airflow limitation pre-LVRS and the improvement noted post-LVRS could be primarily accounted for by the initial loss and subsequent increase in lung elastic recoil. Bilateral lung volume reduction surgery provides modest physiologic improvement for 2-3 yrs in patients with alpha1-antitrypsin emphysema due to increases in lung elastic recoil.
Related Concept Videos
 01:15
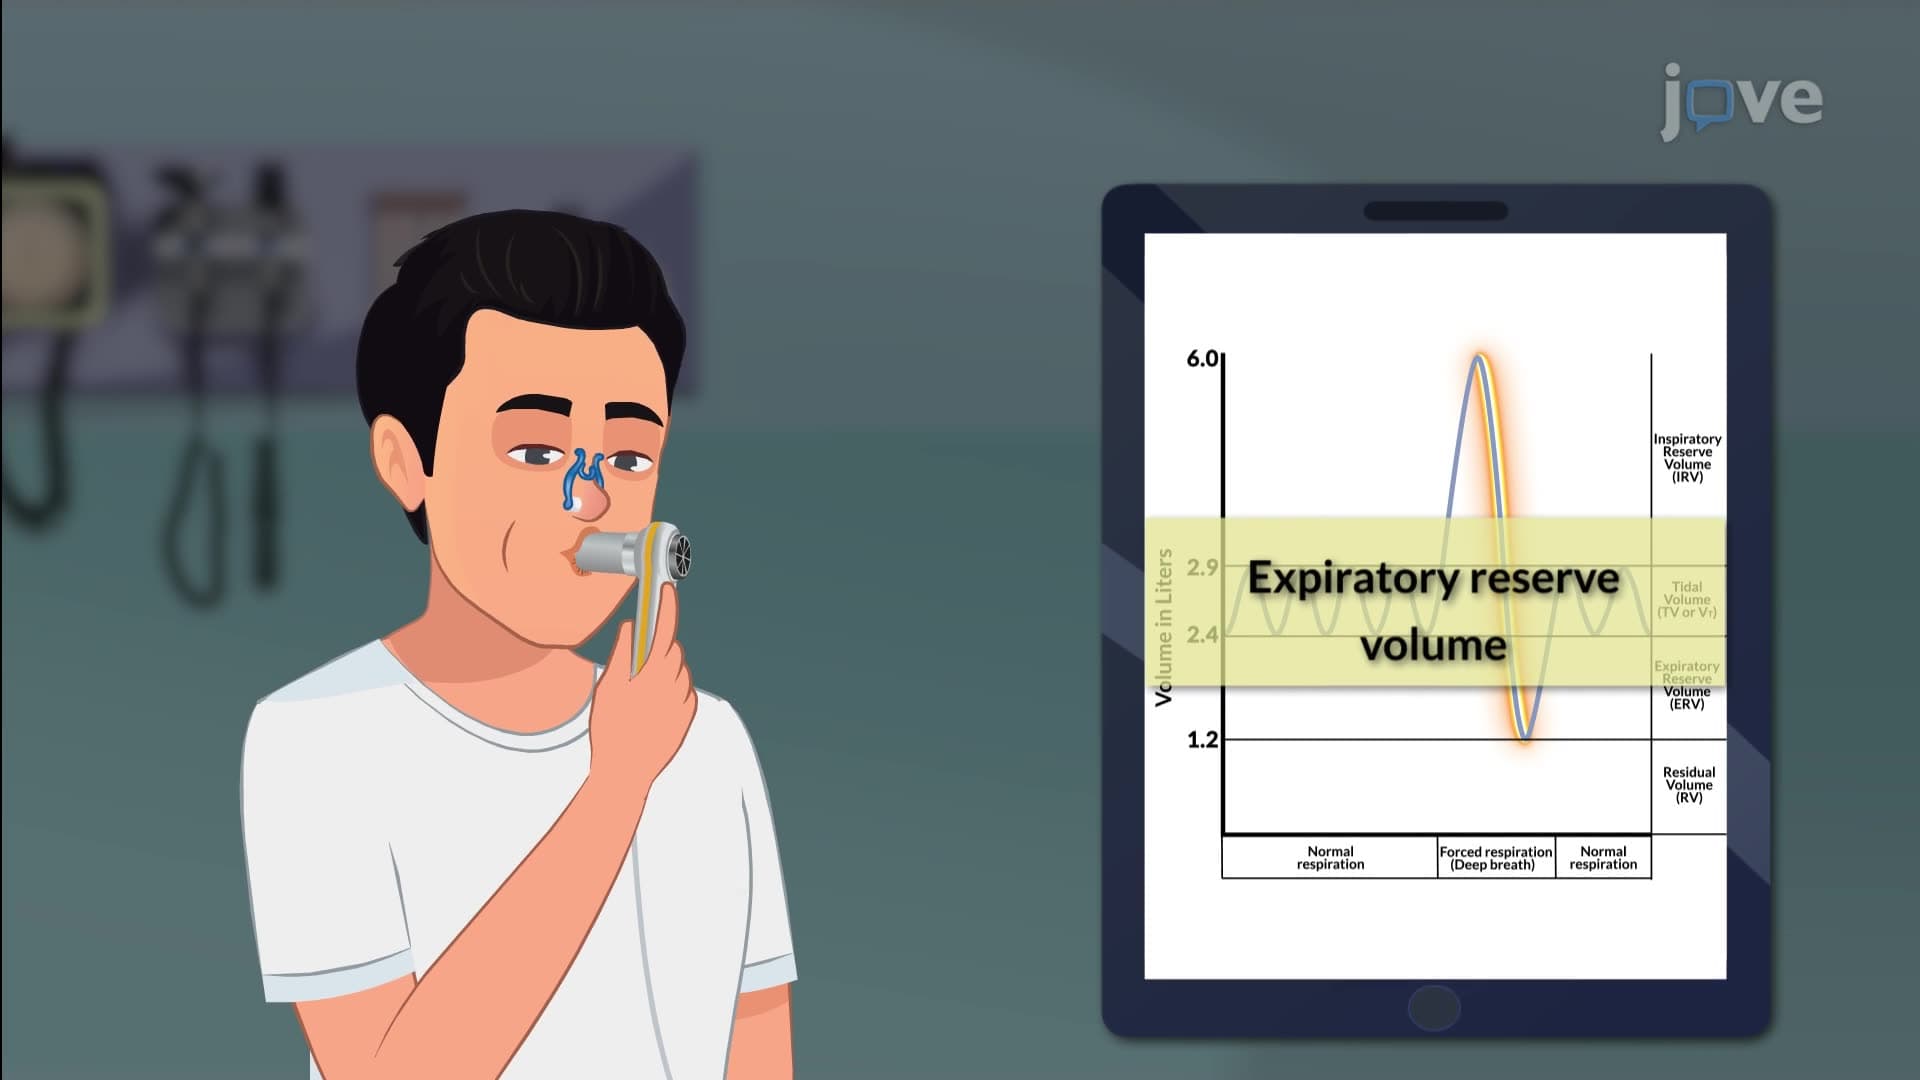
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:10
Atelectasis II: Pathophysiology
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features