Reversible total IgA deficiency associated with phenytoin treatment

J H Braconier1

  • 1Department of Infectious Diseases, Lund University Hospital, Sweden.

Related Concept Videos

Transcytosis of IgG01:15

Transcytosis of IgG

Transcytosis is the process in which molecules are internalized by endocytosis, transported across the cell, and released through exocytosis from the opposite end of the cell. Molecules such as insulin, immunoglobulins, and certain nutrients are transferred through the recycling endosomes by recycling and transcytosis.
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
Gastritis-II: Pathophysiology01:17

Gastritis-II: Pathophysiology

Gastritis is marked by disruption of the mucosal barrier that usually protects the stomach tissue from digestive juices and manifests in acute and chronic forms.
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
Drug Toxicity: Allergic Reactions01:30

Drug Toxicity: Allergic Reactions

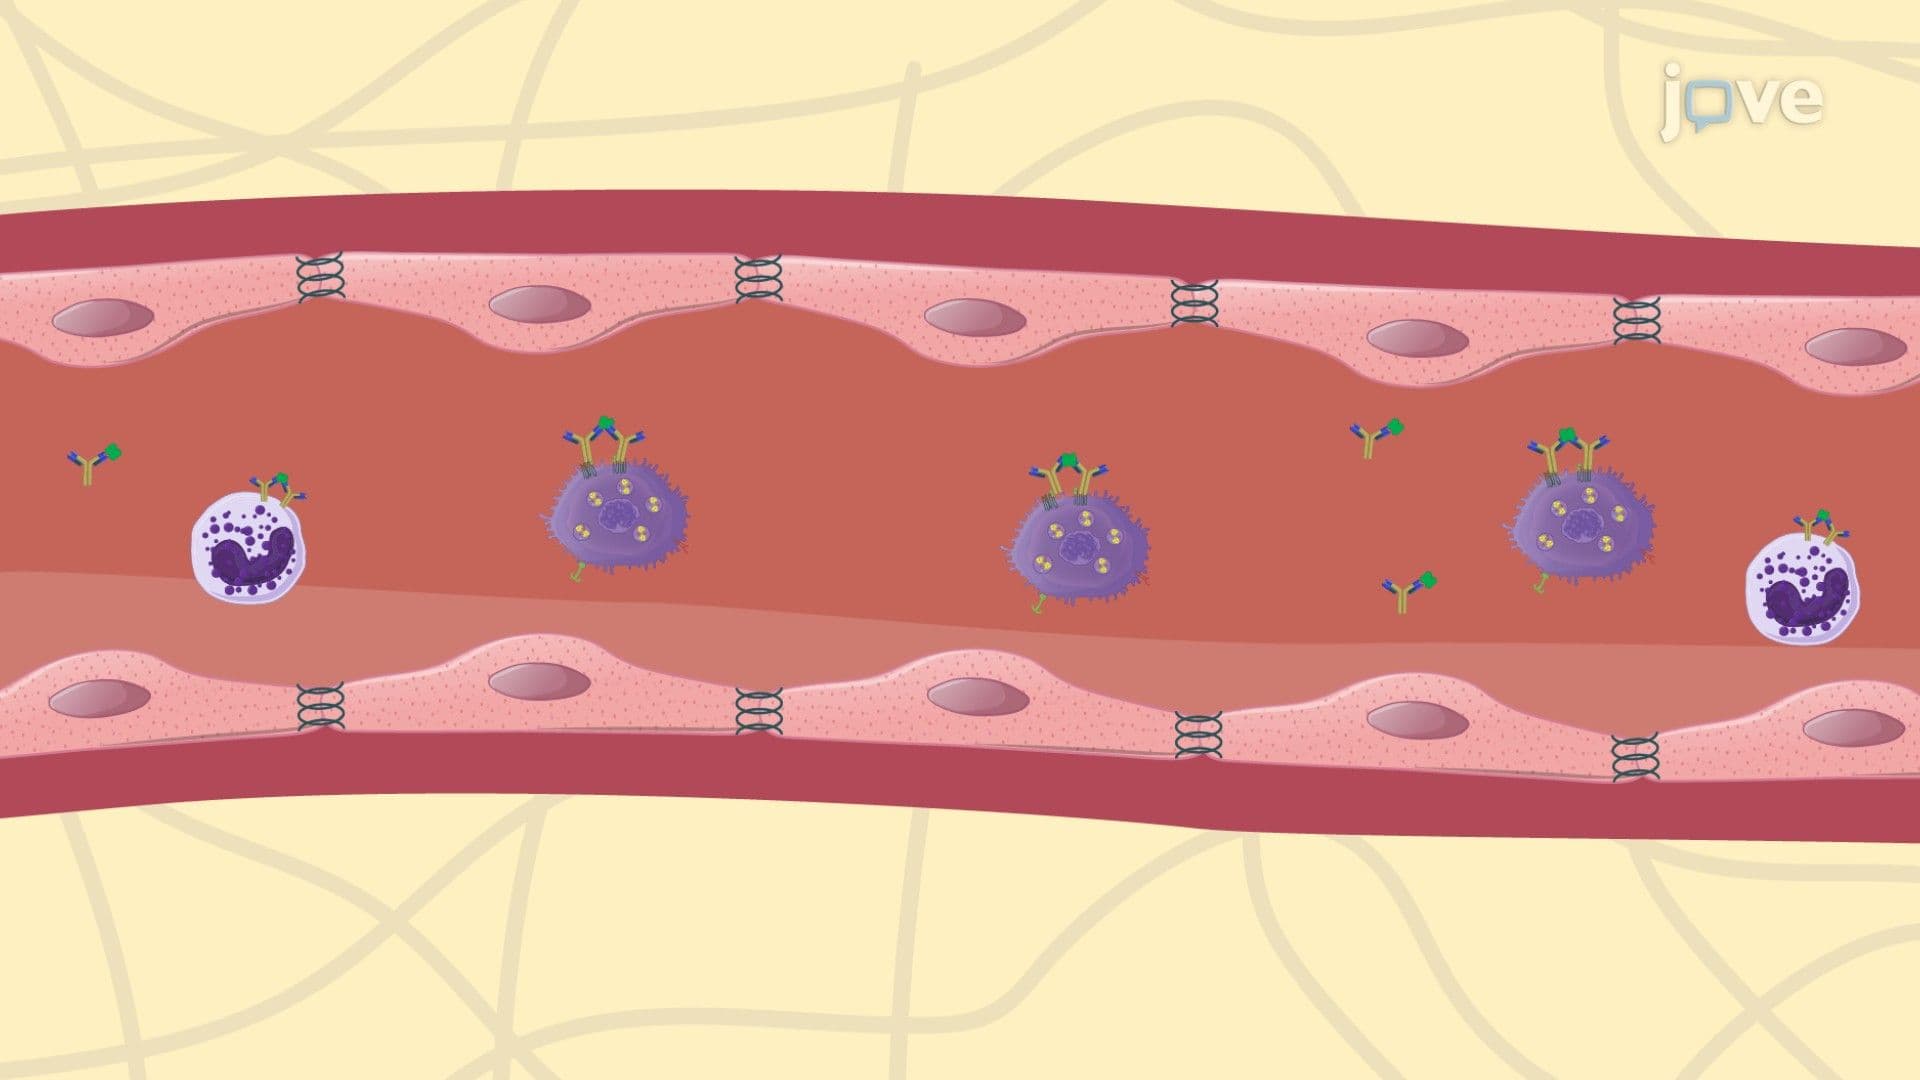
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
Drug toxicity: Idiosyncratic Reactions01:16

Drug toxicity: Idiosyncratic Reactions

Idiosyncratic drug reactions represent abnormal chemical responses that vary significantly among individuals, ranging from extreme sensitivity to low doses to insensitivity to high doses. These reactions often occur due to the drug's covalent binding with serum proteins, forming a foreign hapten that triggers an immunotoxicological response. The variability in drug reactions has a strong pharmacogenetic foundation, with genetic differences crucial in how individuals metabolize drugs. For...
Type I Diabetes I: Introduction01:12

Type I Diabetes I: Introduction

Type 1 diabetes mellitus is a chronic metabolic disorder characterized by an absolute deficiency of insulin resulting from the autoimmune destruction of pancreatic β-cells. Although it can occur at any age, it is most commonly diagnosed in childhood, adolescence, or early adulthood. The loss of insulin production impairs cellular glucose uptake, resulting in persistent hyperglycemia and necessitating lifelong insulin therapy.Autoimmune Destruction of β-CellsThe hallmark of type 1 diabetes is an...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...